


Too Breathless or Exhausted to Cook? Eating Well with Aspergillosis
Last reviewed: 21 October 2026
Audience: People living with aspergillosis, families and carers
Series: The Questions We Don't Always Ask

"I know I should eat properly, but by the time I've prepared something, I'm too exhausted to eat it." For people living with aspergillosis, preparing a meal can sometimes feel like an enormous task. Breathlessness, fatigue, pain, poor appetite and limited money can all make eating well more difficult. Fortunately, nutritious food doesn't have to mean complicated recipes, expensive ingredients or hours in the kitchen.
Key points
- Preparing food can be physically demanding when you have chronic lung disease.
- Simple meals, frozen ingredients and suitable ready meals can all contribute to good nutrition.
- You do not need expensive equipment, specialist ingredients or cookbooks.
- Eating enough protein and maintaining muscle strength may be particularly important when living with chronic illness.
- Some patients need help losing weight, while others need additional nutrition to prevent unintended weight loss.
- Small changes to how you shop, prepare and eat meals can conserve valuable energy.
- Free recipes, NHS resources and practical support are available.
Why can cooking become so difficult?
Cooking involves considerably more activity than simply preparing food.
You may need to plan meals, shop, carry groceries, unpack them, stand while preparing ingredients, lift pans, cook, serve food and wash everything afterwards.
For someone with breathlessness or severe fatigue, these tasks can use much of the energy available for the day.
Other difficulties may include:
- Feeling breathless when standing or moving around the kitchen.
- Weakness, pain or stiffness affecting chopping and lifting.
- Poor appetite, nausea or changes in taste.
- Difficulty concentrating or remembering cooking instructions.
- Feeling too tired to eat after preparing a meal.
- Living alone without anyone to share cooking tasks.
- Limited money for food, heating or electricity.
These are genuine practical barriers. They are not evidence of laziness or a lack of motivation.
Does aspergillosis affect nutrition?
Aspergillosis does not affect everyone's nutritional needs in the same way.
Some people with chronic pulmonary aspergillosis (CPA) experience poor appetite, unintended weight loss or loss of muscle mass. Others may gain weight because of reduced activity, corticosteroid treatment or associated health conditions.
People with allergic bronchopulmonary aspergillosis (ABPA), severe asthma or bronchiectasis may also find that breathlessness and fatigue interfere with everyday eating habits.
There is no single diet proven to treat aspergillosis itself. Good nutrition supports general health, but it does not replace antifungal treatment or other prescribed care.
If you are losing weight without trying, struggling to eat or becoming noticeably weaker, tell your clinical team. You may benefit from assessment by a dietitian.
Choose meals according to how much energy you have
One useful approach is to have different meal options for different days.
Rather than expecting yourself to cook properly every evening, think about what you can manage today.
Very difficult days: almost no preparation
On days when you are exhausted or breathless, a simple meal is better than going without food.
- Yoghurt with fruit and cereal.
- Wholegrain toast with peanut butter, cheese or another suitable topping.
- Hummus with bread or crackers.
- Tinned fish with bread or a ready-made salad.
- Ready-to-eat soup with bread and cheese.
- A suitable chilled or frozen ready meal.
- Beans on toast, if you can manage a few minutes of heating.
These foods do not need to be expensive or elaborate. Supermarket own-brand products can be perfectly reasonable choices.
If your appetite is poor, smaller meals and snacks throughout the day may be easier than three large meals.
Days when you have a little energy
When you can manage some preparation, consider meals with only a few ingredients and minimal washing up.
- Microwave rice with tinned beans and frozen vegetables.
- Scrambled eggs with toast.
- A jacket potato with beans, cheese or tuna.
- Pasta with tomato sauce and tinned lentils.
- An omelette with frozen or pre-prepared vegetables.
- A simple sandwich with soup or fruit.
Prepared vegetables, frozen chopped onions and other convenient ingredients can reduce the effort needed.
Better days: prepare something for later
If you have a day when you feel stronger, preparing an extra portion may help you on a more difficult day.
Meals such as vegetable soup, lentil dishes, chilli and pasta sauces can often be prepared in larger quantities and frozen in individual portions.
However, batch cooking is only useful if it is manageable. You do not need to spend a good day exhausting yourself in the kitchen.
Cool cooked food promptly, refrigerate or freeze it safely, and follow NHS guidance on storage and reheating. Do not repeatedly reheat the same portion.
Make the kitchen work for you
Sometimes changing how you prepare food is as helpful as changing what you eat.
Occupational therapists and respiratory physiotherapists often recommend energy-conservation techniques for people living with long-term conditions.
Practical ways to save energy
- Sit when possible: Prepare ingredients at a table rather than standing for long periods.
- Keep things close: Store frequently used foods and utensils where they are easy to reach.
- Use lightweight equipment: Avoid unnecessarily heavy pans and dishes.
- Divide tasks: Prepare ingredients earlier and rest before cooking.
- Reduce washing up: Choose one-pan meals or use the microwave where appropriate.
- Accept convenient ingredients: Frozen, tinned and pre-prepared foods can save time and effort.
- Ask for help: Shopping, carrying groceries or washing up may be tasks someone else can manage for you.
If breathlessness or limited mobility is making kitchen activities unsafe, ask your healthcare team about occupational therapy assessment or respiratory physiotherapy support.
Safety matters: If you use oxygen at home, follow your oxygen provider's fire-safety instructions. Oxygen equipment must be kept away from naked flames, gas hobs and other ignition sources as directed.
Eating well when money is tight
Chronic illness can reduce income while increasing household expenses. Some people also face higher heating costs, transport costs or difficulty shopping regularly.
Advice that assumes everyone can afford fresh fish, specialist foods or expensive kitchen equipment is not particularly helpful.
Fortunately, nutritious meals can be built around relatively inexpensive ingredients.
Affordable foods worth considering
- Beans and lentils: Useful sources of protein and fibre, available dried or tinned.
- Eggs: Versatile and relatively quick to prepare.
- Frozen vegetables: Often economical, nutritious and less likely to be wasted.
- Oats: Useful for porridge and other simple meals.
- Potatoes, rice and pasta: Affordable foundations for meals.
- Tinned fish: A convenient source of protein, where suitable for your diet.
- Milk and yoghurt: Sources of protein and calcium, with fortified alternatives available.
- Supermarket own-brand products: Often less expensive than branded equivalents.
Frozen and tinned foods are not automatically less healthy than fresh ingredients. Choose lower-salt or lower-sugar options where practical, but do not let the search for a perfect product prevent you from eating.
A ready meal may sometimes be cheaper and more manageable than buying numerous ingredients for a single serving.
If you are struggling to afford food, you can ask your GP practice, local council or Citizens Advice about available support, including local food assistance and benefits advice.
There is no shame in needing help with food costs.
What if I need to lose weight?
Some people with aspergillosis are overweight and may benefit from gradual weight loss.
However, trying to lose weight while managing fatigue and breathlessness can be particularly difficult.
It may help to focus on manageable changes rather than restrictive diets.
- Consider portion sizes and how often you eat high-calorie snacks.
- Choose filling meals containing protein and fibre.
- Use frozen vegetables and other convenient ingredients to make meals easier.
- Reduce sugary drinks if you consume them regularly.
- Seek advice about appropriate activity from your respiratory team.
Preserving muscle strength is important, particularly for older adults and people with chronic lung disease.
For more information, see our article Weight and Aspergillosis: What If I'm Overweight and Struggling to Lose Weight?.
What if I am underweight or losing weight?
For other people, the challenge is getting enough food.
Chronic pulmonary aspergillosis can be associated with poor appetite, unintended weight loss and reduced muscle mass.
In this situation, advice to choose low-calorie foods or reduce portions may be inappropriate.
A dietitian may recommend more frequent meals, additional protein, energy-enriched foods or nutritional supplements, depending on your needs.
Possible approaches include:
- Eating smaller meals more frequently.
- Including protein-containing foods at meals and snacks.
- Keeping convenient foods available for difficult days.
- Choosing foods you enjoy and can manage to eat.
- Discussing nausea, swallowing problems or persistent poor appetite with your healthcare team.
Unintended weight loss should not simply be accepted as a normal part of aspergillosis. It deserves assessment, particularly if it is new or progressing.
What if eating itself makes me breathless?
Some people find that large meals make breathing uncomfortable, particularly if they have significant respiratory disease.
Smaller, more frequent meals may be easier to manage.
Eating slowly, sitting upright and resting before meals may also help.
If you become breathless while eating, discuss this with your respiratory team. New or worsening breathlessness should not automatically be attributed to eating or weight.
Tell your clinician if you cough or choke when swallowing, experience food sticking, develop a wet-sounding voice after meals or have recurrent chest infections associated with eating. These symptoms may require a swallowing assessment.
Food hygiene and aspergillosis
Aspergillus is widespread in the environment, including soil, dust and decaying plant material.
However, pulmonary aspergillosis is generally associated with inhalation of airborne spores rather than eating ordinary food.
Most people with aspergillosis do not need to follow a special mould-free diet.
Standard food hygiene remains important:
- Follow use-by dates and storage instructions.
- Keep chilled foods refrigerated.
- Cook foods thoroughly where required.
- Wash hands and food preparation surfaces.
- Discard visibly mouldy perishable foods rather than simply removing the mouldy area.
- Store leftovers safely and reheat according to NHS food-safety guidance.
People who are severely immunocompromised, such as some transplant recipients or patients receiving intensive cancer treatment, may need additional food-safety precautions. Their specialist team should provide individual advice.
There is no need to impose restrictive food rules on everyone with aspergillosis.
Useful free cooking and nutrition resources
You do not need to purchase a cookbook to find practical ideas. Several organisations provide free advice and accessible recipes.
NHS: Eating Well with Fatigue
The Northern Care Alliance NHS provides practical advice about maintaining nutrition when fatigue makes shopping, preparing and eating meals difficult.
This is particularly relevant for people who find that ordinary kitchen tasks use too much energy.
Read Eating Well with Fatigue – Northern Care Alliance NHS
NHS Healthier Families recipes
The NHS offers free recipes for everyday meals, including relatively simple family dishes.
These may be useful when you have enough energy to cook and want ideas using familiar ingredients.
Explore NHS Healthier Families recipes
Care to Cook
Care to Cook offers accessible recipes and cooking resources designed to make food preparation easier to understand and manage.
The straightforward instructions may be particularly helpful for people who find complicated recipes tiring or difficult to follow.
Explore Care to Cook accessible recipes
The Sad Bastard Cookbook
This freely available cookbook by Rachel A. Rosen and Zilla Novikov takes an unusually practical approach to cooking when energy, motivation or concentration are very limited.
It includes ideas requiring little preparation and commonly available ingredients.
The language and humour are deliberately irreverent, so it may not suit everyone. However, its central message is valuable: eating something manageable is better than feeling defeated by the expectation of preparing a perfect meal.
Find The Sad Bastard Cookbook (free download; check the provider's current terms).
Optional further reading: Cookfulness
Cookfulness, developed by Ian Taverner, explores cooking while living with pain, fatigue, disability and other long-term health difficulties.
Its approach recognises that cooking can be physically and mentally demanding and that recipes may need adapting to the person preparing them.
Some Cookfulness resources and publications are commercial. They are entirely optional; there is no need to purchase anything to follow the advice in this article.
What if I cannot manage cooking at all?
There may be times when cooking is simply not possible.
If this happens regularly, it is worth discussing with your GP, specialist nurse or another member of your healthcare team.
Depending on your circumstances, support might include:
- Dietetic assessment.
- Occupational therapy advice about kitchen adaptations.
- Social care assessment for help with daily living.
- Support with shopping or meal preparation.
- Community meal services, where available.
- Advice about benefits or financial assistance.
If you are unable to obtain or prepare enough food, this is a health and wellbeing concern, not simply a lifestyle preference.
Ask for help before the situation leads to significant weight loss, dehydration or worsening weakness.
The question worth asking
Instead of asking, "Why can't I manage to cook properly?", perhaps the more useful question is:
"What is the simplest way I can eat well with the energy, money and support I have available?"
For some people, that will mean cooking from scratch. For others, it may mean a microwave meal, beans on toast, a prepared sandwich or help from someone else.
Good nutrition is not a competition, and there is no prize for making everything yourself.
Eating well should support your health, not leave you exhausted.
Further information
- NHS: Eat Well – general advice on balanced nutrition.
- NHS: Food guidelines and labels – understanding food choices.
- Food Standards Agency – food hygiene, storage and safety.
- Citizens Advice – financial and practical support.
- Weight and Aspergillosis – managing weight with chronic lung disease.
Medical information: This article provides general educational information. Nutritional needs vary according to your health, medicines and circumstances. If you are losing weight unintentionally, struggling to eat or have specific dietary restrictions, seek individual advice from your healthcare team or a registered dietitian.
More from The Questions We Don't Always Ask
Living with aspergillosis affects more than your lungs. Explore other everyday health questions in our patient information series.


Weight and Aspergillosis: What If I'm Overweight and Struggling to Lose Weight?
Last reviewed: 21 October 2026
Audience: People living with aspergillosis, families and carers
Series: The Questions We Don't Always Ask

"I know I need to lose weight, but I can barely manage the stairs. How am I supposed to exercise?" For people living with aspergillosis, weight can be a particularly difficult subject. Breathlessness, fatigue, steroid treatment and reduced activity may all make managing weight harder. This article looks at what can help, without blame, unrealistic expectations or one-size-fits-all advice.
Key points
- Weight is influenced by many factors, including biology, medicines, sleep, health conditions and circumstances. It is not simply a question of willpower.
- Excess body weight can increase the effort needed to breathe and may worsen breathlessness, but it does not explain every respiratory symptom.
- Steroid treatment, reduced mobility and disrupted sleep can make weight management more difficult.
- Preserving muscle, strength and adequate nutrition is particularly important for people with chronic lung disease.
- Even modest, sustained weight loss may improve some aspects of health, but the right goal varies between individuals.
- Dietetic advice, respiratory physiotherapy, pulmonary rehabilitation and specialist weight management support may help.
- Some people with aspergillosis need nutritional support to prevent weight loss rather than advice to lose weight.
Why is weight such a difficult subject?
Many people who are overweight already know the standard advice: eat less and move more.
What they may not have been given is a realistic explanation of how to do that while living with a chronic illness.
Someone with aspergillosis may experience breathlessness when walking, exhaustion after ordinary activities, disturbed sleep, repeated infections or prolonged courses of treatment.
Preparing meals, shopping and exercising may all require more effort than they once did.
Some people also feel embarrassed about their weight or worry that healthcare professionals will attribute every symptom to it.
These concerns matter. People should be able to discuss weight without feeling blamed or having their lung disease overlooked.
Does being overweight make aspergillosis worse?
There is limited direct research showing how obesity affects the progression of different forms of aspergillosis, such as chronic pulmonary aspergillosis (CPA) or allergic bronchopulmonary aspergillosis (ABPA).
However, excess body weight can affect breathing and general health in several ways.
- Breathing effort: Extra weight around the chest and abdomen can make breathing more physically demanding.
- Exercise tolerance: Walking and climbing stairs may require more energy, particularly when lung function is already reduced.
- Sleep: Obesity increases the risk of obstructive sleep apnoea, which can cause poor sleep and daytime tiredness.
- Other conditions: Obesity is associated with increased risks of type 2 diabetes, cardiovascular disease and high blood pressure.
- Asthma: Obesity can contribute to poorer asthma control in some people, potentially adding to respiratory symptoms in patients with ABPA or severe asthma.
But an important distinction is needed: being overweight does not mean that breathlessness, coughing, fatigue or worsening lung function should automatically be blamed on weight.
New or worsening symptoms may require investigation for infection, changes in aspergillosis, asthma, bronchiectasis or other medical problems.
Why can aspergillosis make weight management harder?
Breathlessness and reduced activity
When ordinary activity causes breathlessness, people naturally begin to avoid unnecessary exertion.
Over time, reduced activity can lead to loss of muscle strength and physical conditioning. Everyday tasks then require more effort, which can make breathlessness feel worse.
This creates a difficult cycle: breathing problems reduce activity, reduced activity lowers fitness, and lower fitness makes activity harder.
Breaking that cycle may require supervised rehabilitation rather than simply being told to exercise more.
Fatigue and poor sleep
Chronic fatigue can affect motivation, meal preparation and daily routines. Poor sleep may also influence appetite and eating behaviour.
People who are exhausted may rely more heavily on convenient foods, not because they lack knowledge, but because they have limited energy.
If you snore heavily, wake gasping, have morning headaches or experience marked daytime sleepiness, ask your GP whether assessment for sleep apnoea is appropriate.
Steroid treatment
Some people with ABPA or severe asthma require oral corticosteroids such as prednisolone or methylprednisolone.
These medicines can increase appetite, alter fat distribution and contribute to fluid retention. Longer-term treatment can also affect blood glucose and muscle strength.
Weight changes during steroid treatment are therefore not always explained by changes in eating habits alone.
Do not stop or reduce prescribed corticosteroids to control weight without medical advice. Steroid doses may need careful adjustment, and abrupt withdrawal can be dangerous, particularly after prolonged treatment.
If weight gain is becoming a significant problem, ask whether your treatment and steroid exposure can be reviewed safely.
What about people with CPA who are losing weight?
This is an especially important distinction.
Some people with chronic pulmonary aspergillosis experience unintended weight loss, reduced appetite, poor nutrition or loss of muscle mass.
For these patients, trying to lose more weight may be inappropriate or harmful, even if their body mass index appears to be above the conventional healthy range.
Muscle strength and nutritional status can matter as much as the number on the scales.
If you have been losing weight without trying, have a poor appetite or notice increasing weakness, tell your clinical team. A dietitian may be able to help you maintain weight, improve protein intake and preserve muscle.
The aim is not to make everyone with aspergillosis thinner. It is to support better health, strength and daily functioning.
How do I know whether my weight is affecting my health?
Body mass index (BMI) is a commonly used measure based on height and weight.
For many adults, a BMI of 25 to 29.9 is classified as overweight, while 30 or above is classified as obesity. Different risk thresholds apply to some ethnic groups.
However, BMI is only one part of a health assessment. It does not directly measure muscle mass, fat distribution, fitness or nutritional health.
Waist measurement, blood pressure, blood glucose, cholesterol, muscle strength and other medical conditions may provide additional information.
For older adults, particularly those with chronic illness, weight goals should also take account of muscle preservation and functional ability.
Ask your GP or dietitian what a sensible target would be for you, rather than relying entirely on a BMI chart.
What if I cannot exercise because I am breathless?
This is one of the most understandable frustrations for people with chronic lung disease.
Exercise does not have to mean running, going to a gym or pushing yourself until you are exhausted.
For some people, carefully supervised walking, chair-based exercises or light resistance work may be a more appropriate starting point.
But the right activity depends on the stability and severity of your lung disease.
Respiratory physiotherapy and pulmonary rehabilitation
Pulmonary rehabilitation combines individually assessed exercise with education and support for people living with chronic respiratory conditions.
A respiratory physiotherapist can help identify appropriate activities, assess breathlessness and develop a programme that takes account of your lung disease, fitness and other medical problems.
This is particularly important if you have severe asthma, significant oxygen desaturation, haemoptysis (coughing up blood), advanced lung disease or a history of complications during exertion.
Do not begin a strenuous exercise programme without specialist advice if you have significant respiratory symptoms or a history of haemoptysis. Active bleeding or sudden worsening of breathlessness requires medical assessment rather than exercise.
For some people, the first goal may be to maintain mobility or regain confidence rather than lose weight.
Can I lose weight without doing much exercise?
Yes. Changes in food intake can contribute to weight loss even when physical activity is limited.
However, reducing food intake too aggressively can also lead to muscle loss, weakness and nutritional deficiencies.
For someone with chronic lung disease, the aim should generally be gradual, sustainable change while maintaining adequate protein and other essential nutrients.
Possible starting points include:
- Reviewing portion sizes without skipping nutritious meals.
- Reducing sugary drinks or frequently consumed high-calorie snacks.
- Including protein-containing foods as part of regular meals.
- Choosing foods that are convenient to prepare when fatigue is a problem.
- Planning meals around your energy levels rather than expecting complicated cooking every day.
- Asking for dietetic support if you have several medical conditions or are unsure how to balance weight loss with adequate nutrition.
Very restrictive diets, prolonged fasting and rapid weight-loss plans may be unsuitable for some people with chronic illness.
If you have diabetes, kidney disease, poor nutritional status or take medicines affected by food intake, seek individual advice before making substantial dietary changes.
What if I am too exhausted or breathless to cook?
Eating well can be particularly difficult when you have chronic lung disease. Shopping, preparing ingredients, standing at the cooker and washing up may use more energy than you have available.
It is not necessary to prepare every meal from scratch. Frozen vegetables, tinned beans, prepared ingredients, microwave rice and suitable ready meals can all be part of a nutritious diet.
Some practical approaches include:
- On difficult days: Choose simple meals that require little preparation, such as eggs on toast, soup with bread and cheese, or yoghurt with fruit.
- When you have some energy: Try one-pan meals, microwave cooking or prepared ingredients that reduce chopping and washing up.
- On better days: Consider preparing extra portions and freezing them for later, if you can do so safely.
- Make cooking easier: Sit while preparing food, keep frequently used items within reach and take breaks when needed.
If you are trying to lose weight, portion sizes and nutritional balance still matter. If you are losing weight unintentionally or struggling to maintain muscle, you may need more energy and protein instead. A dietitian can help you identify what is appropriate.
Two useful resources are:
- Northern Care Alliance NHS: Eating Well with Fatigue – practical advice for maintaining nutrition when energy is limited.
- Cookfulness – cooking approaches developed around challenges such as fatigue, pain and disability.
Remember: A simple, manageable meal is often more useful than an elaborate healthy recipe that leaves you exhausted.
Would losing a small amount of weight make a difference?
For some people living with obesity, modest weight loss can improve blood pressure, blood glucose control, mobility or other aspects of health.
Whether it improves breathlessness depends on what is causing that breathlessness. Weight loss cannot reverse lung damage caused by aspergillosis.
It is reasonable to set goals based on things that matter to you, such as:
- Being able to walk a little further.
- Finding everyday activities less exhausting.
- Improving blood glucose or blood pressure.
- Sleeping better.
- Maintaining muscle strength.
- Feeling more comfortable and confident.
Progress may be slow, and there may be periods when maintaining your weight is a worthwhile achievement.
What about weight-loss injections such as Wegovy or Mounjaro?
Medicines used to treat obesity, including semaglutide (Wegovy) and tirzepatide (Mounjaro), can help eligible people lose weight by affecting appetite and feelings of fullness.
They are not suitable for everyone and are not treatments for aspergillosis itself.
Access through the NHS depends on clinical eligibility, local services and the phased introduction of some treatments.
These medicines may cause side effects such as nausea, vomiting, diarrhoea or constipation. For someone already struggling with appetite, hydration, nutrition or maintaining muscle, these effects deserve particular attention.
People taking antifungal medicines or several other treatments should have their complete medication list reviewed before starting weight-management medication.
Some medicines affect stomach emptying, and gastrointestinal side effects can make it harder to take or tolerate other prescribed treatments. The clinical significance depends on the medicines involved.
Do not assume that weight-loss injections are appropriate simply because your BMI is above a particular threshold. A clinician should assess your overall health, nutrition, treatment and eligibility.
For current NHS guidance, see NHS England: Weight management injections.
What if I have tried to lose weight many times?
Repeated attempts at weight loss can be discouraging, especially when weight returns after an initial improvement.
Obesity is a complex, long-term health condition. Appetite regulation, metabolism, medicines, environment and personal circumstances can all influence weight.
Regaining weight does not mean that someone has failed or that previous efforts were pointless.
If you have repeatedly struggled, structured support may be more useful than another short-term diet.
Your GP may be able to discuss community weight-management programmes, dietetic support, specialist services or medical treatments where appropriate.
What if I feel judged about my weight?
People living with obesity sometimes report that their symptoms are dismissed or attributed to their weight before other causes are properly investigated.
This can be particularly concerning when someone already has a diagnosed respiratory condition.
It is entirely reasonable to ask for both issues to be considered.
"I understand my weight may contribute to my breathlessness, but I also have aspergillosis. Can we check whether my lung condition is stable and discuss what support might help me manage my weight?"
You deserve appropriate investigation and treatment for your respiratory symptoms regardless of your weight.
Where should I start?
Rather than beginning with an ambitious target, consider asking three questions:
- Is weight loss appropriate for me? Or should I prioritise maintaining weight, improving nutrition or rebuilding muscle?
- What is making weight management difficult? Steroids, fatigue, poor sleep, breathlessness, emotional stress or something else?
- What support would make a realistic difference? A dietitian, respiratory physiotherapist, pulmonary rehabilitation, weight-management service or medication review?
These questions can turn a difficult subject into a practical conversation with your healthcare team.
The question worth asking
Instead of asking, "Why can't I just lose weight?", try asking:
"What would help me become healthier and stronger, given the limitations of my lung disease?"
For some people, the answer will include gradual weight loss. For others, it may be improved nutrition, greater muscle strength, better sleep or more effective management of their respiratory condition.
All of these are legitimate health goals.
Where to find reliable information
- NHS: Obesity – causes, health effects and treatment options.
- NICE: Overweight and obesity management – UK evidence-based guidance.
- NHS England: Weight management injections – eligibility and treatment information.
- British Thoracic Society: Pulmonary rehabilitation – specialist respiratory rehabilitation information.
Medical information: Weight-management advice should be adapted to your medical history, nutritional status and prescribed treatments. This article provides general educational information and does not replace individual advice from your GP, respiratory specialist, dietitian or physiotherapist.
Struggling to prepare meals? Read our guide Too Breathless or Exhausted to Cook? Eating Well with Aspergillosis for affordable meal ideas, energy-saving cooking tips and free resources.

Alcohol and Aspergillosis: What If I Drink More Than I Should?
Last reviewed: 21 October 2026
Audience: People living with aspergillosis, families and carers
Series: The Questions We Don't Always Ask

Alcohol and Aspergillosis: What If I Drink More Than I Should?
Most people know that drinking too much alcohol can affect their health. But knowing something and changing it are very different things. For someone living with aspergillosis, alcohol may raise additional questions about antifungal medicines, liver health, fatigue and recovery. These are questions worth discussing openly, without embarrassment or judgement.
Key points
- Alcohol does not automatically make aspergillosis worse, but heavy drinking can affect general health, immune function and recovery.
- Some medicines used to treat aspergillosis can affect the liver. Heavy drinking may add to concerns about liver health.
- There is no single alcohol rule that applies to every antifungal, steroid or biologic treatment.
- Always check the Patient Information Leaflet (PIL) supplied with your medicine, or find it through the electronic Medicines Compendium (eMC).
- Being open about how much you drink helps your clinical team give safer, more individualised advice.
- Reducing alcohol can improve health, even if stopping completely feels unrealistic.
- If you are physically dependent on alcohol, stopping suddenly can be dangerous. Seek medical advice before making a major reduction.
Why can alcohol be difficult to talk about?
Alcohol is part of everyday life for many people. It may be associated with relaxing after work, social occasions, celebrations or simply enjoying a familiar routine.
For someone living with a long-term illness, it may also become a way of coping with anxiety, loneliness, pain, frustration or uncertainty about the future.
People sometimes avoid mentioning how much they drink because they worry about being judged, criticised or told to stop altogether.
But your healthcare team needs accurate information, not an idealised version of your lifestyle. The purpose of asking about alcohol should be to understand your health and help you make informed decisions.
You do not have to wait until drinking has become a serious problem before raising the subject.
Does alcohol make aspergillosis worse?
There is limited direct research into how different levels of alcohol consumption affect chronic pulmonary aspergillosis (CPA), allergic bronchopulmonary aspergillosis (ABPA) or other forms of aspergillosis.
However, heavy or prolonged drinking can affect several aspects of health that matter when living with chronic lung disease.
- Immune function: Heavy alcohol consumption can impair immune responses and increase susceptibility to some infections.
- Nutrition: Drinking heavily may contribute to poor dietary intake and nutritional deficiencies.
- Sleep: Alcohol may initially make someone feel sleepy, but it can disrupt sleep quality later in the night.
- Fatigue: Hangovers, dehydration, disturbed sleep and poor nutrition can make existing tiredness more difficult to manage.
- Other medical conditions: Alcohol can worsen some liver, cardiovascular, metabolic and mental health problems.
These effects do not mean that an occasional drink necessarily causes measurable harm to someone's aspergillosis. The amount consumed, frequency, other health conditions and prescribed medicines all matter.
Alcohol and medicines used to treat aspergillosis
People with aspergillosis may take antifungal medicines, corticosteroids, biologic treatments or other medicines for their lung disease and associated conditions.
Medicines differ. Some have specific precautions involving alcohol, while others have no established direct alcohol interaction. However, alcohol may still affect general health or make certain side effects more difficult to manage.
The best starting point is the Patient Information Leaflet (PIL) supplied with your medicine. This explains important precautions, interactions and side effects. You can also find UK patient leaflets through the electronic Medicines Compendium (eMC).
If the leaflet does not mention alcohol, that does not automatically mean drinking is safe for you. Your medical history, other medicines and blood test results may affect the advice you receive.
Antifungal medicines
Antifungal treatments include itraconazole, voriconazole, posaconazole, isavuconazole and, in some circumstances, other medicines such as amphotericin B or echinocandins. Newer antifungal treatments are also being developed and introduced.
Some antifungals can affect liver function. Heavy alcohol consumption can independently damage the liver, so it is particularly important to discuss drinking with your prescribing team if you are taking long-term antifungal treatment or have abnormal liver tests.
Different antifungals have different safety profiles. For example, amphotericin B treatment requires particular attention to kidney function and blood electrolytes. This is not the same as having a proven direct interaction with alcohol.
For newer or investigational antifungals, follow the specific advice provided by your specialist team or clinical trial. Alcohol restrictions may form part of a trial protocol even when a medicine has no established alcohol interaction.
Steroids and biologic treatments
Corticosteroids such as prednisolone, methylprednisolone and inhaled steroids are frequently used to manage allergic or inflammatory lung conditions, including ABPA.
Alcohol is not universally prohibited with corticosteroids. However, drinking may aggravate problems such as stomach irritation, poor sleep, changes in mood or difficulties controlling blood glucose.
Biologic treatments used for severe asthma and some patients with ABPA have different safety considerations. Do not assume that all biologics have the same advice about alcohol.
Check the leaflet for your particular treatment and ask your pharmacist or specialist team if you are uncertain.
Where can I check my medicine?
Always read the Patient Information Leaflet supplied with your medicine. You can also search for UK medicines and their leaflets using the electronic Medicines Compendium (eMC).
Examples of medicines used in aspergillosis care include:
- Itraconazole – product information
- Voriconazole – product information
- Posaconazole – product information
- Isavuconazole – product information
- Amphotericin B – product information
- Prednisolone – product information
- Methylprednisolone – product information
Important: Select the leaflet matching your actual medicine and formulation. Not all medicines, particularly investigational treatments, will have a UK PIL available through eMC. Your prescribing team can provide the appropriate information.
For a broader explanation of antifungal treatment, see our guide to antifungal medicines.
When is extra caution particularly important?
Discuss alcohol use with your healthcare team if:
- You have liver disease or abnormal liver function tests.
- You take medicines that can cause liver injury.
- You have kidney problems or are receiving treatment requiring careful fluid and electrolyte monitoring.
- You have diabetes or difficulty controlling your blood glucose.
- You take several medicines and are concerned about interactions.
- You have been specifically advised to avoid alcohol.
- You are participating in a clinical trial with alcohol restrictions.
Do not stop, skip or change prescribed treatment because you have consumed alcohol. If you are concerned about a possible interaction, contact your pharmacist or prescribing team for advice.
What if my liver tests are abnormal?
Abnormal liver function tests can have several causes, including medicines, alcohol, fatty liver disease, infections and other health conditions.
If your tests change during antifungal treatment, your team may need to investigate the cause and decide whether additional monitoring or treatment changes are necessary.
Tell them about your alcohol consumption, including any recent increase. This information may help them interpret the results.
Seek prompt medical advice if you develop yellowing of the skin or eyes, dark urine, pale stools, persistent vomiting or significant new abdominal pain, particularly while taking an antifungal medicine.
How much alcohol is too much?
UK Chief Medical Officers advise that, to keep health risks from alcohol low, adults who drink should not regularly exceed 14 UK units per week. If drinking this amount, it is better to spread it over three or more days rather than drink it all at once.
This is a low-risk guideline, not a guarantee of safety. Drinking less generally reduces risk, and there is no completely risk-free level of alcohol consumption.
People with liver disease, certain medical conditions or particular medication risks may be advised to avoid alcohol altogether.
What does 14 units look like?
- A 175 ml glass of wine at 12% alcohol contains approximately 2.1 units.
- A pint of beer at 4% contains approximately 2.3 units.
- A 25 ml measure of spirits at 40% contains 1 unit.
Alcohol strength and serving sizes vary considerably. Large wine glasses, stronger beers and generous home measures can contain more units than people expect.
You can calculate units using:
Units = volume in ml × alcohol strength (%) ÷ 1,000
For example, a 250 ml glass of 13% wine contains 3.25 units.
What if I regularly drink more than the recommended amount?
Many people do. It does not mean that you have failed or that your healthcare team cannot help.
It is worth thinking about what role alcohol plays in your life.
Do you drink mainly socially? Is it a habit at the end of the day? Does it help you manage anxiety or sleep problems? Do you sometimes drink more than you intended?
Understanding the reasons can be more useful than simply setting a target without a plan.
Small changes can make a difference
If you are not physically dependent on alcohol, possible ways to reduce consumption include:
- Keeping a record of what you drink for a week, including quantities and strengths.
- Choosing smaller servings or lower-alcohol alternatives.
- Replacing some alcoholic drinks with alcohol-free options.
- Setting a realistic weekly target and reviewing it.
- Identifying situations where you tend to drink more than intended.
- Finding alternative ways to relax or manage stress.
- Asking a GP, pharmacist or alcohol support service for help.
You do not need to make every change at once. For many people, gradual and sustained progress is more manageable than an ambitious target that is difficult to maintain.
What if I find it difficult to cut down?
Some people develop alcohol dependence. This means that their body has adapted to regular alcohol consumption and they may experience withdrawal symptoms when alcohol is reduced or stopped.
Possible symptoms include shaking, sweating, anxiety, nausea, disturbed sleep or feeling unwell until they have another drink.
Important: stopping suddenly can be dangerous
If you think you may be physically dependent on alcohol, do not abruptly stop drinking without medical advice. Alcohol withdrawal can cause seizures, hallucinations and other potentially life-threatening complications.
Contact your GP or a specialist alcohol service for help planning a safe reduction or medically supported withdrawal. Severe withdrawal symptoms, seizures or significant confusion require emergency medical care.
Effective support is available, including structured psychological support, community alcohol services and, where appropriate, prescribed medication or supervised withdrawal.
What if I drink because living with aspergillosis is difficult?
Chronic illness can affect much more than the lungs.
Breathlessness, fatigue, uncertainty about the future, repeated appointments and limitations on everyday activities can all contribute to stress and low mood.
Some people use alcohol to switch off from these worries. The relief may feel real in the short term, even when drinking makes sleep, anxiety or fatigue worse afterwards.
If this sounds familiar, it may be helpful to talk about the problem behind the drinking, rather than focusing only on alcohol itself.
Support with anxiety, sleep, pain, social isolation or adjustment to chronic illness may make reducing alcohol easier.
What should I tell my respiratory or antifungal team?
You do not need to wait until alcohol has become a serious problem before discussing it.
You could simply say:
"I probably drink more than is recommended, and I'm worried it might affect my antifungal treatment. Can we talk about what is safe for me?"
Useful information to share includes:
- How often you drink and roughly how much.
- Whether your drinking has increased recently.
- Whether you have previously had abnormal liver tests or liver disease.
- Any difficulties you have experienced when trying to reduce drinking.
- Whether alcohol is affecting sleep, appetite, mood or taking your medicines.
Your healthcare team can then consider your circumstances when advising about medicines, monitoring and additional support.
Does everyone with aspergillosis need to stop drinking?
Not necessarily. There is no universal rule requiring every person with aspergillosis to avoid all alcohol.
However, abstinence may be the safest advice for some people, particularly those with significant liver disease, alcohol dependence, a history of alcohol-related harm or other important medical risks.
People taking antifungal medicines should obtain advice specific to their treatment and medical history rather than assuming that moderate drinking is always safe.
The aim is to make informed decisions based on your health, not to impose the same rule on everyone.
The question worth asking
Perhaps the most useful question is not simply, "Am I allowed to drink?"
It is:
"Given my lung condition, medicines and general health, what would reducing alcohol realistically achieve for me?"
That opens the door to a more useful conversation about risk, treatment and the changes that matter most.
Living with aspergillosis can already involve considerable restrictions. Good advice should help people understand their choices, not add unnecessary guilt or shame.
Where to find help
- NHS: Alcohol advice – UK drinking guidelines, units and ways to reduce drinking.
- NHS: Alcohol misuse – recognising problems, treatment and support.
- Drinkaware – alcohol information, unit calculators and practical resources.
- WithYou – support for alcohol and drug problems.
- Electronic Medicines Compendium – UK Patient Information Leaflets and medicine safety information.
Medicine safety: Information about medicines can change. Always check the Patient Information Leaflet supplied with your medicine and seek advice from your pharmacist or prescribing team. This article provides general educational information and does not replace individual medical advice.
More from The Questions We Don't Always Ask

Building Fitness with Aspergillosis

Last updated: 19 October 2026
Audience: Patients, carers, families and non-specialists
Applies to: Allergic bronchopulmonary aspergillosis (ABPA), chronic pulmonary aspergillosis (CPA), Aspergillus bronchitis and severe asthma with fungal sensitisation (SAFS)
Exercise with Aspergillosis: Staying Active Safely
Living with aspergillosis can make physical activity surprisingly difficult. Walking upstairs, shopping, gardening or even getting dressed may leave you breathless or exhausted.
This can be frustrating, especially if you were previously active. However, difficulty exercising is not simply a sign of poor fitness. Lung inflammation, airway narrowing, structural lung damage, fatigue and the effects of treatment can all contribute.
Physical activity can help many people with aspergillosis maintain muscle strength, confidence and independence. However, exercise needs to be appropriate for your individual lung condition.
People with chronic pulmonary aspergillosis, lung cavities, previous haemoptysis (coughing up blood) or severe asthma may need particular precautions.
Before starting or substantially increasing exercise, discuss your plans with your respiratory team and ask whether an assessment by a respiratory physiotherapist would be appropriate. This is especially important if you have significant breathlessness, unstable symptoms or complications affecting your lungs.
Key points
- Breathlessness and fatigue are common in aspergillosis and have several possible causes.
- Appropriate physical activity can improve strength, stamina and quality of life.
- Exercise is not automatically safe at every intensity for everyone with aspergillosis.
- People with haemoptysis, lung cavities, aspergillomas or severe asthma need individual assessment and advice.
- A respiratory physiotherapist can help identify suitable activities, breathing techniques and precautions.
- Pacing and adequate recovery are important, particularly when symptoms fluctuate.
- People who experience prolonged or delayed worsening after exertion should not follow automatic increases in exercise.
Why exercise feels difficult
Aspergillosis affects people in different ways. Someone with well-controlled ABPA may have very different exercise limitations from someone with advanced CPA, bronchiectasis or severe asthma.
Several factors can make activity more demanding:
- Inflamed or narrowed airways: Airway inflammation and bronchospasm can make breathing more difficult during exertion.
- Excess mucus: Mucus can obstruct airways and contribute to coughing and breathlessness.
- Structural lung damage: Cavities, scarring and other changes may reduce respiratory function.
- Reduced oxygen levels: Some people experience a fall in blood oxygen during exercise.
- Increased work of breathing: Breathing itself may require more effort than usual.
Other causes of reduced stamina
Long-term respiratory illness can affect the whole body.
- Reduced activity can lead to muscle weakness and loss of fitness.
- Persistent coughing may disrupt sleep.
- Long-term oral corticosteroids can contribute to muscle weakness and other adverse effects.
- Repeated infections or exacerbations can interrupt recovery.
- Poor nutrition, anaemia, hormonal problems and other conditions may contribute to fatigue.
These factors can occur together, making it difficult to identify one cause of exhaustion.
Breathlessness and fatigue should not automatically be dismissed as a lack of fitness. New or worsening symptoms deserve medical assessment.
Understanding fatigue and recovery
Fatigue is common in people living with chronic respiratory disease. It can be more disabling than ordinary tiredness and may not improve completely after a night's sleep.
It is useful to distinguish between different patterns of fatigue.
Ordinary tiredness after activity
Some tiredness following exercise is expected, particularly after a period of illness or inactivity.
When medically appropriate, regular exercise with adequate recovery may gradually improve muscle strength and stamina.
Fatigue associated with chronic illness
Persistent inflammation, breathlessness, disturbed sleep and the demands of managing a long-term condition can contribute to ongoing fatigue.
Symptoms may vary considerably from day to day.
Post-exertional symptom exacerbation
Some people experience a substantial worsening of symptoms after physical or mental exertion. This is known as post-exertional symptom exacerbation (PESE), sometimes called post-exertional malaise (PEM).
Symptoms may be delayed until later that day or the following day and may take a prolonged period to settle.
PESE is not established as a typical feature of aspergillosis itself, but recognising this pattern is important.
If activity repeatedly causes a marked or prolonged deterioration, do not attempt to overcome it by continually increasing exercise.
Discuss these symptoms with your healthcare team. Your activity plan may need to focus on energy management rather than conventional exercise progression.
Why respiratory physiotherapy matters
One of the most useful steps for someone struggling with activity is to seek advice from a respiratory physiotherapist.
Respiratory physiotherapists are trained to assess and support people with lung disease. They can help patients understand their physical limitations, manage breathlessness and identify suitable forms of activity.
For people with complicated aspergillosis, physiotherapy advice should be coordinated with the respiratory specialist responsible for their care.
What can a respiratory physiotherapist assess?
Depending on your condition, an assessment may include:
- Your usual level of physical activity and exercise tolerance.
- Breathlessness during everyday tasks.
- Breathing patterns and techniques.
- Oxygen saturation at rest and, when appropriate, during exertion.
- Muscle strength, balance and mobility.
- Mucus production and airway clearance needs.
- Relevant medical precautions, including previous haemoptysis and severe asthma.
Some patients require medical assessment or stabilisation before exercise testing is appropriate.
How can physiotherapy help?
A respiratory physiotherapist can recommend activities suited to your current abilities and medical circumstances.
They may also help with:
- Breathing control during exertion.
- Safe and effective airway clearance.
- Managing breathlessness during everyday activities.
- Planning activity and recovery periods.
- Identifying suitable strengthening exercises.
- Referral to pulmonary rehabilitation.
- Recognising symptoms that mean exercise should be reduced or stopped.
If you have significant aspergillosis-related breathlessness, severe asthma, lung cavities or a history of haemoptysis, ask your respiratory team about an individual assessment by a respiratory physiotherapist before increasing exercise.
Pacing and managing your energy
Many people with chronic illness recognise a pattern of doing too much on a good day, becoming exhausted afterwards and then needing extra recovery time.
This is sometimes called the boom-and-bust cycle.
Pacing involves planning activities around your symptoms and available energy rather than repeatedly pushing yourself to exhaustion.
Practical ways to pace activity
- Know your baseline: Identify what you can usually manage without a substantial deterioration afterwards.
- Spread activities throughout the day: Avoid concentrating all demanding tasks into one period.
- Plan rest periods: Take breaks before becoming completely exhausted.
- Alternate activities: Combine more demanding tasks with less strenuous ones.
- Adjust for difficult days: Reduce activity during infections, exacerbations or periods of worsening symptoms.
- Keep a simple diary: Record activity, symptoms and recovery to identify useful patterns.
Pacing is not necessarily the same as avoiding exercise. For many people, it helps make regular activity more sustainable.
However, people with PESE may require more structured energy management and should avoid fixed exercise increases that provoke symptom deterioration.
Becoming more active safely
The following suggestions are general examples, not an individual exercise prescription.
They are intended for people whose respiratory condition is stable and for whom their healthcare team considers activity appropriate.
If you have severe asthma, recent haemoptysis, significant lung cavities, unstable symptoms or marked breathlessness, obtain individual advice before starting or increasing exercise.
Start at an appropriate level
Depending on your abilities, suitable activities might include:
- Short walks on level ground.
- Gentle movements while seated.
- Light everyday activities around the home.
- Supervised strengthening exercises.
- Other low-impact activities recommended by your physiotherapist.
For some people, only a few minutes of activity may initially be manageable. Others may already tolerate much longer periods.
The correct starting point depends on your symptoms, underlying lung disease and recovery.
Increase gradually when appropriate
When your condition is stable and you are recovering comfortably, your physiotherapist may recommend gradual increases in activity.
There is no requirement to increase exercise every week or to reach a predetermined target.
Any increase should be guided by your symptoms, response to activity and professional advice.
Breathing techniques
Some people find breathing control techniques helpful when managing breathlessness.
For example, pursed-lip breathing involves breathing in gently and breathing out slowly through lightly pursed lips.
However, breathing techniques are not equally helpful for everyone. A respiratory physiotherapist can demonstrate those most appropriate to your condition.
Muscle strengthening
Maintaining muscle strength can make daily activities easier.
Exercises such as standing from a chair or using light resistance may be suitable for some patients.
However, people with a history of haemoptysis, significant lung damage, osteoporosis or other medical complications should obtain individual guidance before undertaking resistance training, heavy lifting or strenuous exertion.
Exercise, lung cavities and haemoptysis
Some people with chronic pulmonary aspergillosis develop cavities within the lungs. An aspergilloma, sometimes called a fungal ball, may develop inside an existing cavity.
These conditions can be associated with haemoptysis — coughing up blood.
Why can bleeding occur?
In CPA, inflammation and structural lung damage can be associated with enlarged or abnormal blood vessels around affected areas.
These vessels may bleed, sometimes unpredictably.
Having a cavity or aspergilloma does not automatically mean that all exercise is unsafe. However, the risks vary between individuals, and there is insufficient evidence to define a universally safe exercise intensity for patients at risk of haemoptysis.
What precautions are needed?
If you have a history of haemoptysis, particularly recurrent or significant bleeding, discuss your exercise plans with your respiratory specialist before increasing activity.
Depending on your circumstances, your team may advise precautions concerning strenuous exercise, heavy lifting or activities involving substantial straining.
A respiratory physiotherapist can help identify appropriate activities once your specialist considers exercise safe.
If you are currently coughing up blood, stop exercising and seek urgent medical advice. Do not continue an exercise programme while active bleeding is being assessed.
Airway clearance also needs consideration
Some people with aspergillosis and bronchiectasis require regular airway clearance to manage mucus.
However, certain airway clearance techniques may need to be modified or temporarily withheld during episodes of haemoptysis.
Seek guidance from your respiratory team or respiratory physiotherapist rather than independently intensifying airway clearance when bleeding occurs.
Exercise and severe asthma
People with ABPA or severe asthma with fungal sensitisation (SAFS) may have asthma that is difficult to control.
Exercise can trigger temporary airway narrowing, known as exercise-induced bronchoconstriction.
This may cause:
- Wheezing.
- Chest tightness.
- Coughing during or after activity.
- Unusual breathlessness.
Physical activity can still be beneficial for people with asthma, but it is important that symptoms are adequately controlled.
Before increasing exercise
If you have severe or poorly controlled asthma, speak to your asthma specialist or respiratory team about:
- Whether your asthma is sufficiently controlled for the proposed activity.
- Whether your inhaler treatment needs reviewing.
- Your personalised asthma action plan.
- Whether medication is recommended before exercise under your prescribed treatment plan.
- How to recognise exercise-induced bronchoconstriction.
- Whether supervised physiotherapy or pulmonary rehabilitation would be appropriate.
A gradual warm-up may help some people, but it does not replace appropriate asthma treatment.
Do not attempt to push through significant wheezing, chest tightness or increasing breathlessness.
Stop activity and follow your prescribed asthma action plan. Seek emergency help if you have a severe attack or symptoms are not responding to reliever treatment as directed.
Pulmonary rehabilitation
Pulmonary rehabilitation is a structured programme combining individually adapted exercise, education and self-management support.
It is commonly offered to people whose chronic respiratory conditions cause breathlessness or limit everyday activities.
What are the potential benefits?
Depending on the underlying condition and individual circumstances, pulmonary rehabilitation may help:
- Improve exercise tolerance.
- Increase muscle strength.
- Improve confidence in managing breathlessness.
- Support everyday independence.
- Improve health-related quality of life.
Pulmonary rehabilitation has a strong evidence base in several chronic respiratory conditions, although research specifically involving aspergillosis remains more limited.
People with aspergillosis may also have bronchiectasis, asthma, COPD or other respiratory conditions for which rehabilitation may be beneficial.
Is pulmonary rehabilitation suitable for everyone?
Not necessarily.
Patients with active haemoptysis, unstable severe asthma, acute illness or other significant medical complications may need treatment or specialist assessment before participating.
Programmes should be adapted to individual needs, and some patients may require additional medical supervision.
If breathlessness or fatigue limits your daily life, ask your GP or respiratory team whether pulmonary rehabilitation is appropriate and whether you should first be assessed by a respiratory physiotherapist.
Recognising progress
Improvement does not always mean walking further or exercising for longer.
For someone living with aspergillosis, progress might mean:
- Climbing stairs with fewer stops.
- Being able to prepare a meal more comfortably.
- Walking around the garden without becoming excessively breathless.
- Recovering more comfortably after ordinary activities.
- Feeling more confident about leaving the house.
- Maintaining independence despite ongoing symptoms.
Progress is rarely completely consistent. Respiratory infections, seasonal changes, treatment effects and fluctuations in symptoms may all affect what you can manage.
Sometimes maintaining your existing abilities during a difficult period is itself an important achievement.
The goal is to improve or preserve the activities that matter to you, without exposing yourself to unnecessary risk.
When to seek medical help
Contact your healthcare team if you develop:
- New or worsening breathlessness.
- A significant reduction in exercise tolerance.
- Persistent or unexplained fatigue.
- Repeated prolonged deterioration after activity.
- Increasing wheezing or poorly controlled asthma symptoms.
- Changes in cough or sputum that suggest an exacerbation.
Haemoptysis: coughing up blood
Stop exercising if you cough up blood.
Even small amounts of new haemoptysis should be assessed promptly. Contact your respiratory team urgently, or seek advice through your GP or NHS 111 if your team is unavailable.
Call 999 if you cough up a significant amount of blood, particularly if accompanied by breathing difficulty, chest pain, dizziness or faintness.
Severe breathlessness or asthma symptoms
Stop activity if you develop marked breathlessness, wheezing or chest tightness.
Follow your prescribed asthma action plan if applicable.
Call 999 for severe breathing difficulty, a severe asthma attack that is not responding to treatment as directed, severe chest pain or collapse.
Final message: finding a safe way to stay active
Aspergillosis can make physical activity difficult, but remaining appropriately active may help preserve strength, confidence and independence.
The safest approach depends on your diagnosis, symptoms, lung function and any complications.
For people with severe asthma, lung cavities, aspergillomas, significant breathlessness or a history of haemoptysis, exercise should be planned with particular care.
A respiratory physiotherapist, working alongside your respiratory specialist, can help you understand your limitations and identify activities that are appropriate for you.
You do not need to push yourself to exhaustion to make progress. The aim is to find a level of activity that is useful, sustainable and safe for your individual condition.
In one sentence
Exercise can benefit people with aspergillosis, but anyone with significant respiratory symptoms or complications should seek individual advice from their respiratory team and a respiratory physiotherapist before increasing activity.
Further information and support
You may also find information on these topics helpful:
- Pulmonary rehabilitation and respiratory physiotherapy.
- Airway clearance and managing mucus.
- Fatigue and breathlessness in aspergillosis.
- Chronic pulmonary aspergillosis and lung cavities.
- Haemoptysis (coughing up blood).
- Managing asthma and ABPA.
Explore the information hubs at aspergillosis.org, or speak to your respiratory team about your individual circumstances.

Aspergillosis Research Update: Faster Diagnosis, Preventing Infection and Hospital Air Safety
Weekly Research Update | 12–19 October 2026
Research published this week highlights three important aspects of aspergillosis care: developing faster diagnostic tests, preventing fungal infections in vulnerable patients, and understanding how hospital ventilation may influence exposure to Aspergillus.
Although these studies focus mainly on invasive aspergillosis rather than chronic pulmonary aspergillosis (CPA) or allergic bronchopulmonary aspergillosis (ABPA), they provide useful insights into how fungal infections are detected and prevented.
1. Can a rapid blood test help detect Aspergillus infection?
Diagnosing invasive aspergillosis can be difficult, particularly in people whose immune systems are weakened by illness or medical treatment. Doctors often use several investigations, including CT scans, fungal cultures and blood tests.
One commonly used test detects galactomannan, a substance released by Aspergillus fungi.
Researchers in Pakistan investigated whether a rapid lateral-flow test could provide useful results compared with a conventional laboratory galactomannan test.
The study examined 155 blood samples using both methods.
What did the researchers find?
- The rapid test detected approximately 78% of samples that were positive using the laboratory test.
- It correctly identified approximately 83% of samples that were negative using the laboratory test.
- Some positive results from the rapid test were not confirmed by the conventional method.
The researchers concluded that the rapid test could be useful for screening, although positive results may need confirmation.
What does this mean for patients?
Faster testing could potentially help doctors investigate suspected fungal infections more promptly, especially where access to specialist laboratories is limited.
However, a negative rapid test cannot completely rule out aspergillosis, and a positive result does not necessarily mean that someone has an active fungal infection.
Doctors must interpret results alongside symptoms, scans, other laboratory findings and the patient's individual risk factors.
This was a relatively small study, currently available as a preprint, and it compared two tests rather than establishing how accurately the rapid test diagnoses confirmed invasive aspergillosis.
Research: Zaheer F et al. Diagnostic Accuracy of Aspergillus Lateral Flow Assay for Detection of Galactomannan Antigen in Serum. Access Microbiology, 2026.
2. Why do some patients develop fungal infections despite preventive treatment?
People undergoing organ transplantation often receive medicines that suppress their immune systems to prevent rejection of the transplanted organ.
Unfortunately, this also increases their vulnerability to certain infections, including invasive aspergillosis.
Doctors sometimes prescribe antifungal medicines as a precaution, particularly for patients considered at high risk.
A new Italian study examined fungal infections among 286 liver-transplant recipients.
Of these, 85 were classified as high risk and received planned preventive treatment with an echinocandin antifungal, usually caspofungin.
What did the researchers find?
- Eight of the 85 high-risk patients (9.4%) developed an invasive fungal infection within 30 days of transplantation.
- Four of the 201 other recipients (2.0%) developed an invasive fungal infection.
- Most infections in the high-risk group occurred despite preventive treatment and involved mould fungi.
The researchers also examined aspergillosis cases across a longer period. They found no clear evidence of a sustained outbreak associated with a common environmental source.
What does this mean for patients?
Preventive antifungal medicines can be an important part of protecting vulnerable patients, but they cannot eliminate every risk.
Different antifungal medicines work against different fungi, and some infections may develop despite appropriate precautions.
Importantly, the patients receiving preventive treatment were already considered at greater risk. The higher infection rate in this group does not mean that preventive treatment caused infections or was necessarily ineffective.
The findings reinforce the importance of continued monitoring and prompt investigation when symptoms suggest a possible fungal infection.
Research: Viero G et al. Early Invasive Fungal Infections in Liver Transplant Recipients Receiving Risk-Stratified Echinocandin Prophylaxis. Transplant Infectious Disease, 2026.
3. Could hospital ventilation affect the risk of aspergillosis?
Aspergillus spores are widespread in the environment, including in outdoor air, soil and decaying vegetation.
Most people inhale these spores without developing illness. However, people with severely weakened immune systems may be particularly vulnerable.
Hospitals therefore pay close attention to air filtration, ventilation and infection prevention in areas caring for high-risk patients.
A recent scientific commentary in Critical Care examined an important question: does the way intensive care rooms are ventilated influence the risk of pulmonary aspergillosis?
The authors discussed research involving negative-pressure rooms, which are designed to prevent potentially infectious air from escaping into surrounding areas.
They highlighted that findings from different studies have not always been consistent.
One possible explanation is that purpose-built negative-pressure rooms may behave differently from ordinary rooms converted to negative pressure, particularly if airflow and filtration are not carefully managed.
The authors also raised questions about differences in fungal testing between patient groups, which could influence reported infection rates.
What does this mean for patients?
Hospital ventilation is an important part of infection prevention, but simply describing a room as having negative or positive pressure does not tell us everything about its safety.
Airflow direction, filtration, maintenance and the needs of individual patients all matter.
For example, negative-pressure rooms are commonly used to contain airborne infections, while specialised positive-pressure environments with filtered air may be used to protect particularly vulnerable patients from environmental contamination.
This commentary does not establish that negative-pressure rooms cause aspergillosis. Instead, it highlights why careful ventilation design and appropriate infection-control measures are important.
Research: Ichai P et al. Negative-pressure ICU rooms and pulmonary aspergillosis: room conversion matters. Critical Care, 2026.
Other research published this week
Aspergillosis affecting Meckel's cave
Researchers described a rare infection involving Meckel's cave, a region near the base of the skull associated with the trigeminal nerve, which carries sensation from the face.
The case illustrates how aspergillosis can occasionally affect structures outside the lungs and may require specialised surgery alongside antifungal treatment.
Aspergillus and tuberculosis infection after kidney transplantation
Another report described the challenges of treating a patient with both Aspergillus infection and tuberculosis following kidney transplantation.
Such cases can be particularly complicated because immunosuppressive medicines, antifungal treatments and tuberculosis drugs may interact.
These are individual case reports, so their findings cannot necessarily be applied to other patients.
What can we take away from this week's research?
Three themes emerge from these publications.
Diagnosis is improving, but no single test provides every answer. Rapid tests may help clinicians investigate suspected aspergillosis, but results must be interpreted alongside other evidence.
Prevention remains essential for vulnerable patients. Antifungal prophylaxis can be valuable, but continued monitoring is important because breakthrough infections can occur.
The hospital environment matters. Ventilation, air filtration and infection-control practices are important considerations, particularly for people at high risk of invasive fungal infection.
For people living with CPA or ABPA, these studies do not suggest an immediate change to established treatment. Nevertheless, they contribute to a broader understanding of how Aspergillus infections are recognised, prevented and managed.
This article is part of the National Aspergillosis Centre's weekly research updates, explaining recent scientific publications in language accessible to patients and their families. Research findings should not be used to change treatment without advice from the healthcare team responsible for your care.
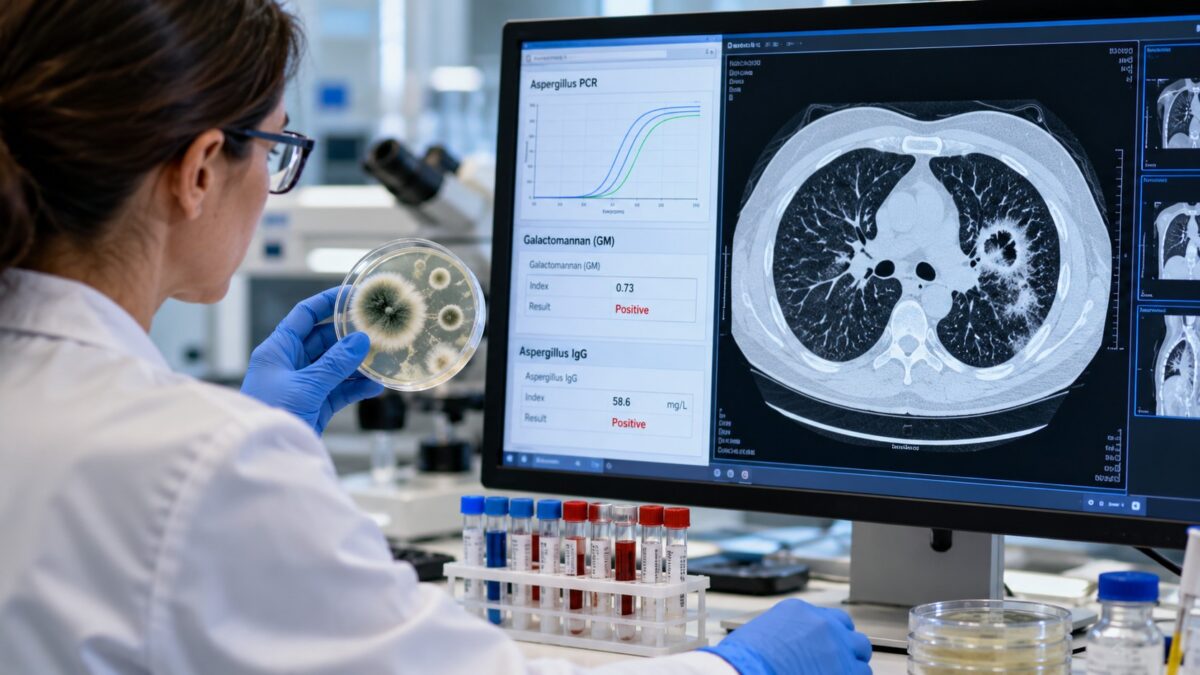
New Tests for Aspergillosis: How Emerging Technologies Could Improve Diagnosis
Last reviewed: 19 October 2026
Author: Graham Atherton
Next scheduled review: October 2028
Key points
- Diagnosing aspergillosis can be difficult because symptoms and scan findings may resemble other lung conditions.
- Doctors use a combination of imaging, blood tests and laboratory investigations. No single test is suitable for every form of aspergillosis.
- PCR, fungal antigen tests and some rapid tests are already used in specialist laboratories.
- Newer approaches, including breath analysis, advanced sequencing and AI-assisted CT interpretation, may improve diagnosis in the future.
- Finding Aspergillus in a sample does not always mean it is causing disease.
Why is aspergillosis sometimes difficult to diagnose?
Aspergillus is a common fungus found in the environment. Most people breathe in its spores regularly without becoming ill.
However, some people develop lung disease associated with Aspergillus, particularly those with existing lung damage or weakened immune defences.
Symptoms such as cough, breathlessness, tiredness and weight loss can have many causes. Even a positive fungal test may be difficult to interpret because Aspergillus can sometimes be present in the airways without causing infection.
Doctors therefore consider the patient's symptoms, medical history, CT scans and laboratory results together.
Different forms of aspergillosis need different tests
There is no single diagnostic pathway for every form of aspergillosis.
- Chronic pulmonary aspergillosis (CPA) develops over months or years, often in people with previously damaged lungs. Diagnosis commonly relies on characteristic CT changes, evidence implicating Aspergillus and the clinical history.
- Aspergilloma is a fungal ball, usually growing within an existing lung cavity.
- Aspergillus nodules may resemble other lung nodules, including cancer. Sometimes a tissue sample is needed to establish the diagnosis.
- Invasive aspergillosis generally occurs in people with significant immune impairment or other major risk factors and may progress rapidly.
- Allergic bronchopulmonary aspergillosis (ABPA) is primarily an allergic response to Aspergillus. Tests such as Aspergillus-specific IgE, total IgE, eosinophils and CT imaging are particularly important.
- Aspergillus bronchitis is an airway infection rather than simply an allergic condition. Sputum testing may be especially relevant.
This article focuses mainly on tests that detect fungal infection or fungal material, rather than tests used specifically to diagnose allergy.
Tests already used in clinical practice
CT scans
CT scans show changes in the structure of the lungs, including cavities, fungal balls, nodules, airway abnormalities and areas of inflammation.
They are central to diagnosing many forms of pulmonary aspergillosis.
Comparing scans taken months apart can be particularly helpful in chronic disease because it allows doctors to assess progression or improvement.
However, CT findings are not always specific to Aspergillus.
Aspergillus IgG antibody tests
Aspergillus-specific IgG is an important blood test when doctors suspect chronic pulmonary aspergillosis.
It detects antibodies produced by the immune system in response to the fungus.
A positive result supports the diagnosis in the right clinical circumstances, but does not prove active infection on its own. Some patients with CPA may also have negative results.
The interpretation depends on the assay used and the patient's wider clinical picture.
Fungal culture
A sputum sample or fluid collected during bronchoscopy can be cultured in a laboratory to look for fungal growth.
Culture can identify Aspergillus species and may allow testing of their susceptibility to antifungal medicines.
Its main limitation is that the fungus may not grow even when infection is present. Conversely, a positive culture does not always prove that Aspergillus is responsible for the patient's symptoms.
PCR: detecting fungal DNA
PCR stands for polymerase chain reaction. It is a laboratory technique that detects genetic material from an organism.
Aspergillus PCR may be performed on sputum, bronchoscopy fluid or tissue, depending on the clinical situation and laboratory.
PCR can be faster than culture and may detect fungal material when culture is negative.
However, detecting fungal DNA does not necessarily mean there is active infection. The test may also detect colonisation or fungal material that is not causing disease.
PCR results are therefore interpreted alongside imaging and other tests.
Fungal antigen tests
Antigens are substances associated with an organism that can be detected by laboratory tests.
Galactomannan
Galactomannan is a component of the Aspergillus fungal cell wall.
Testing for galactomannan is well established in the investigation of invasive aspergillosis, particularly in selected high-risk patients.
It may be measured in blood or bronchoalveolar lavage fluid obtained during bronchoscopy.
For chronic pulmonary aspergillosis, galactomannan testing of bronchoscopy fluid may sometimes be helpful, but blood testing is much less reliable.
A negative galactomannan result does not exclude every form of aspergillosis.
Beta-D-glucan
Beta-D-glucan is a component of the cell walls of several different fungi.
A positive blood test may provide supporting evidence for certain invasive fungal infections, but it is not specific to Aspergillus.
It cannot identify which fungus is responsible and is not routinely used to establish a diagnosis of chronic pulmonary aspergillosis.
Rapid fungal tests
Some fungal tests use a lateral-flow format, similar in appearance to a home pregnancy test.
These tests can detect particular fungal markers without requiring all the equipment used for conventional laboratory assays.
Certain lateral-flow tests are already commercially available and used in specialist diagnostic settings. Others remain under evaluation.
Their usefulness depends on the type of aspergillosis, the sample tested and the performance of the individual test.
Rapid testing is particularly attractive where access to specialist laboratories is limited, but a quick result is not automatically a definitive diagnosis.
Detecting resistance to antifungal medicines
Resistance to azole antifungal medicines is an important challenge, particularly in Aspergillus fumigatus.
Traditionally, laboratories investigate resistance by growing the fungus and testing its response to antifungal drugs.
Molecular tests can also identify certain genetic changes associated with resistance, including mutations involving the cyp51A gene.
Some specialist assays can detect these changes directly in clinical samples, potentially providing useful information when culture is negative.
However, not all resistance mechanisms are detectable by these tests. Conventional susceptibility testing remains important whenever a suitable isolate is available.
Earlier recognition of resistance may help clinicians choose more appropriate treatment.
Technologies being developed
Several promising approaches are being investigated, but they should not yet be regarded as routine diagnostic replacements.
Breath testing
Fungi and other microorganisms can produce volatile organic compounds (VOCs) — small chemical substances that may be detected in exhaled breath.
Researchers are investigating whether patterns of these compounds could help identify fungal lung infections.
Breath testing would be attractive because it is non-invasive and potentially quick.
However, the compounds detected may be influenced by other infections, medicines, diet and environmental exposures.
Further research is needed before breath testing can be relied upon to diagnose aspergillosis in routine care.
Advanced DNA sequencing
Traditional PCR usually looks for a particular organism or genetic target.
Advanced sequencing methods can examine a much wider range of genetic material within a sample.
These methods may help identify unusual fungi, mixed infections or organisms missed by more targeted tests.
Researchers are also studying the lung microbiome — the communities of microorganisms found in the respiratory system.
A major challenge is distinguishing organisms that are genuinely causing disease from those that are simply present.
Sequencing is also relatively expensive, and interpretation requires specialist expertise.
Artificial intelligence and CT imaging
Artificial intelligence (AI) systems can be trained to recognise patterns in medical images.
Researchers are exploring whether AI could help radiologists identify abnormalities, measure changes in lung cavities or monitor disease progression.
For chronic pulmonary aspergillosis, consistent measurement of changes over time could be particularly useful.
However, AI tools must be carefully validated across different patient groups and scanning systems.
They are not a substitute for specialist radiological and clinical assessment.
What might diagnosis look like in the future?
Rather than relying on one new test, future diagnosis may involve combining several types of information more effectively.
For example, a patient with suspected chronic pulmonary aspergillosis might have CT imaging, antibody testing and sputum investigations, with molecular or resistance testing added where appropriate.
Someone with suspected invasive aspergillosis may require a different combination of investigations, sometimes urgently.
The aim is not simply to perform more tests. It is to obtain the right information sooner, avoid unnecessary procedures and make treatment decisions with greater confidence.
Common questions
Why can aspergillosis take so long to diagnose?
Symptoms can resemble other respiratory illnesses, and no single test identifies every form of the disease.
Doctors may need to compare scans over time, repeat samples or exclude other explanations.
Does a positive Aspergillus PCR mean I have aspergillosis?
Not necessarily. PCR detects fungal DNA, which may be present without active infection.
The result needs to be considered alongside symptoms, scans and other investigations.
Can I have aspergillosis with a negative blood test?
Yes. The reliability of blood tests varies according to the form of aspergillosis and the patient's immune response.
A negative result does not always exclude disease.
Can a blood test tell whether my Aspergillus is resistant to treatment?
Some molecular tests can identify particular resistance-associated mutations, but these are not suitable for every situation.
Your specialist laboratory may use a combination of molecular methods and culture-based susceptibility testing.
Are AI scans and breath tests available now?
They are primarily research and development approaches for this purpose. Their availability and clinical usefulness remain limited compared with established investigations.
What this means for patients
Diagnostic technology is improving, but the most important principle remains unchanged: aspergillosis is diagnosed by combining evidence, not relying on one test result.
If you are undergoing investigation, it is reasonable to ask your clinical team which form of aspergillosis they are considering, what each test is intended to show, and whether further investigations are needed.
Further information
For established information about tests and investigations, visit the Aspergillosis Diagnostics Hub.
This article is educational and does not replace advice from your treating clinical team.
References
- Denning DW, et al. Chronic pulmonary aspergillosis: rationale and clinical guidelines for diagnosis and management. European Respiratory Journal. 2016;47:45–68. https://doi.org/10.1183/13993003.00583-2015
- Ullmann AJ, et al. Diagnosis and management of Aspergillus diseases: executive summary of the 2017 ESCMID-ECMM-ERS guideline. Clinical Microbiology and Infection. 2018;24(Suppl 1):e1–e38. PubMed
- Pulmonary aspergillosis: diagnosis and treatment. European Respiratory Review. 2022. PubMed
- Fan Y, et al. Lateral-flow device for the diagnosis of invasive aspergillosis: a systematic review and diagnostic meta-analysis. BMC Infectious Diseases. 2025;25:388. https://doi.org/10.1186/s12879-025-10769-x

Aspergillosis Carer Checklist: What to Watch For and What Helps

Caring for someone with aspergillosis can sometimes feel unpredictable. This practical checklist helps carers recognise important changes, provide support on difficult days and understand when medical advice may be needed. It is designed as a quick reference rather than a substitute for individual medical advice.
Key Points
- People living with aspergillosis may experience good days and difficult days, but not every change is caused by aspergillosis itself.
- Breathlessness, fatigue, coughing, sputum and changes in everyday functioning are useful things to notice.
- Understanding what is normal for the individual helps carers recognise significant changes.
- Some symptoms need prompt medical advice, while others are medical emergencies.
- Rest, pacing, practical assistance and emotional support can make difficult days easier.
- Carers need support and time to look after their own wellbeing too.
Contents
- Daily Check-in
- Signs That Things May Be Worsening
- What Helps on a Difficult Day
- When to Seek Medical Help
- Preparing for Appointments
- Checklist for the Carer
- Printable Quick Summary
- Further Information
Daily Check-in
Carers do not need to monitor every symptom all the time. It is usually more helpful to recognise changes from the person's normal pattern.
Questions worth considering include:
- Is their breathing about the same as usual, or has it become worse?
- Are they coughing more frequently or having more troublesome coughing episodes?
- Has the amount, colour or consistency of sputum changed?
- Are they noticeably more tired than usual?
- Can they manage ordinary activities such as washing, dressing and eating?
- Are they sleeping significantly better or worse than usual?
- Do they seem unusually distressed, anxious or withdrawn?
- Are prescribed medicines being taken as directed?
A brief note of important changes can be useful, particularly when symptoms fluctuate or the person has difficulty remembering how they felt several days earlier.
However, a sudden or severe change should be assessed promptly rather than waiting to see whether a pattern develops.
Signs That Things May Be Worsening
People with aspergillosis often live with symptoms that vary from day to day. A difficult day does not necessarily mean the fungal disease is becoming more active.
Possible causes include fatigue, physical overexertion, poor sleep, inflammation, respiratory infections, medication effects or changes in the underlying lung condition.
Signs that deserve attention include:
- Increasing breathlessness
- A substantial rise in fatigue or time spent resting
- More frequent or distressing coughing
- Changes in sputum production
- Increased wheezing or chest tightness
- Reduced ability to manage normal activities
- Fever or a general feeling of illness
- Symptoms that persist or progressively worsen
It is useful to distinguish between symptoms that are familiar and manageable and those that are new, unusual or substantially worse.
Important: Not every deterioration is an aspergillosis flare-up. Bacterial infections, other respiratory problems and unrelated medical conditions can produce similar symptoms.
What Helps on a Difficult Day
Simple practical support can make a considerable difference when someone is feeling particularly unwell or exhausted.
- Encourage pacing: Help spread necessary activities throughout the day, with rest between them.
- Reduce unnecessary demands: Postpone non-essential activities when symptoms are troublesome.
- Offer practical assistance: Help with meals, shopping, household tasks or transport.
- Support prescribed treatment: Help the person follow their agreed medication and respiratory care routines.
- Allow time: Avoid rushing someone who is breathless or severely fatigued.
- Listen: Ask what would be most helpful rather than assuming.
- Notice changes: Keep a brief record of symptoms that are new or significantly different.
- Respect independence: Offer help without taking over activities the person wishes to manage themselves.
Fatigue associated with chronic lung disease can be profound. Encouraging someone to push through severe exhaustion may make their day harder rather than better.
Equally, persistent or unexplained exhaustion should not automatically be attributed to aspergillosis without considering other possible causes.
When to Seek Medical Help
Carers should be familiar with the person's usual symptoms and any individual action plan provided by their clinical team.
Seek emergency help
Call 999 in the UK if the person develops:
- Severe difficulty breathing, particularly if they cannot speak normally or are struggling for air
- Sudden severe chest pain, especially with breathlessness, sweating or collapse
- New severe confusion, collapse or difficulty remaining awake
- Coughing up a substantial amount of blood, or bleeding accompanied by breathing difficulty, faintness or rapid deterioration
Seek prompt medical advice
Contact the GP, specialist team or NHS 111 if the person develops:
- Breathlessness that is noticeably worse than usual
- A new fever or symptoms suggesting a chest infection
- New blood in their sputum, even if the amount is small
- A significant change in cough or sputum
- Unusual or persistent deterioration in fatigue or everyday functioning
- Concerning symptoms after starting or changing medication
People with a history of haemoptysis (coughing up blood) may have specific instructions from their specialist team. Follow those instructions where provided.
If you are unsure how urgently someone needs assessment, NHS 111 can advise. Do not delay calling 999 when symptoms suggest an emergency.
Preparing for Appointments
Clinic appointments, telephone consultations and hospital visits can be tiring. A short written summary can help the patient and carer make the most of the time available.
Before an appointment, consider:
- What has changed since the last review?
- Which symptoms are currently most troublesome?
- Has breathlessness, fatigue or coughing changed?
- Have there been any new infections or episodes of coughing up blood?
- Have medicines or doses changed?
- Have any possible side effects appeared?
- Are there test results or treatment decisions that need explaining?
- What are the most important questions to ask?
It can help to agree on the two or three most important questions beforehand.
Carers can provide valuable observations, but the person living with aspergillosis should remain involved in discussions and decisions wherever possible.
Checklist for the Carer
Caring for someone with a long-term condition can be physically and emotionally demanding. Carers sometimes concentrate so much on the other person's needs that they neglect their own.
Questions worth asking yourself include:
- Am I getting enough rest?
- Have I eaten properly and taken breaks today?
- Am I trying to manage everything alone?
- Could family, friends or local services help with practical tasks?
- Have I had some time for my own interests or activities?
- Do I need someone to talk to about the pressures of caring?
- Do I know whom to contact if I cannot provide care temporarily?
Looking after your own wellbeing helps make caring more sustainable.
Carers may also be entitled to a carer's assessment through their local council, which can identify practical support and other services.
Printable Quick Summary
This section can be printed or saved as a quick reminder.
Watch for: Changes in breathlessness, fatigue, coughing, sputum, fever and ability to manage everyday activities.
What helps: Rest, pacing, practical assistance, prescribed medication routines, emotional support and brief notes about important changes.
Seek prompt medical advice for: Worsening breathlessness, fever, new blood in sputum, significant changes in coughing or unexplained deterioration.
Call 999 for: Severe breathing difficulty, sudden severe chest pain, collapse, severe confusion or substantial coughing up of blood.
Remember: Follow the person's individual emergency or respiratory action plan where one has been provided.
Further Information
These related guides provide more detailed advice:
- Supporting Someone with Aspergillosis: A Guide for Carers and Families
- Energy Pacing for Carers
- When Someone with Aspergillosis Has a Bad Day
- Understanding Aspergillosis Medicines: A Guide for Carers
Patients and carers can also join the National Aspergillosis Centre patient support meetings to share experiences and find practical support.
Author: Aspergillosis Patient Support Team
Editorial update: 19 October 2026
Next scheduled review: October 2027
This article provides general information and does not replace individual medical advice. Clinical review attribution should reflect an actual completed review.

Understanding Aspergillosis Medicines: A Guide for Carers

Medicines used to treat aspergillosis can be very important, but they can also be complicated. Carers often help with medication reminders, monitoring side effects, keeping track of blood tests and understanding why treatment changes. This guide explains the main treatments, what monitoring involves and how carers can support safe medicine use.
Key Points
- Different forms of aspergillosis require different treatments. Some people need antifungal medicines, others need treatment for allergic inflammation, and some need both.
- Treatment may take time to work and sometimes aims to control a long-term condition rather than provide a quick cure.
- Antifungal medicines can interact with other treatments, including certain inhaled steroids.
- Blood tests and other monitoring help ensure treatment remains safe and effective.
- Steroid treatment should not be stopped suddenly without medical advice.
- Carers can help by keeping accurate medicine records, recognising possible side effects and supporting communication with the clinical team.
Contents
- Why Medicines Matter in Aspergillosis
- Main Types of Treatment
- Antifungal Medicines
- Steroids and Anti-inflammatory Treatment
- Biologic Treatments
- Why Monitoring and Blood Tests Matter
- Recognising Possible Side Effects
- Understanding Drug Interactions
- How Carers Can Help Safely
- When to Seek Medical Advice
- Further Information
Why Medicines Matter in Aspergillosis
Aspergillosis is not one single illness. Treatment depends on the type of disease, its severity and the person's wider health.
Some people need medicines to control fungal infection. Others need treatment to reduce allergic inflammation. Some require a combination of treatments.
Decisions may also be influenced by conditions such as asthma, bronchiectasis, chronic obstructive pulmonary disease (COPD), kidney or liver problems, and other medicines the person takes.
For carers, an important point to understand is that treatment often involves balancing the expected benefits against possible side effects and interactions.
A medicine that works well for one person may not be suitable for another.
Main Types of Treatment
Medicines used in the management of aspergillosis and associated lung conditions may include:
- Antifungal medicines: Reduce fungal growth or activity.
- Corticosteroids: Reduce inflammation, particularly in allergic forms of aspergillosis.
- Biologic medicines: Target particular immune pathways in selected patients with severe asthma or allergic disease.
- Supportive treatments: May include inhalers, antibiotics and medicines for other lung conditions.
Not everyone needs all these treatments. Some people may not need antifungal treatment at all, while others require prolonged courses or changes between medicines.
Antifungal Medicines
Antifungal medicines are used when treatment aims to control fungal growth or infection. They are particularly important in conditions such as chronic pulmonary aspergillosis (CPA), invasive aspergillosis and some cases of Aspergillus bronchitis.
Antifungals may also be used in selected patients with allergic bronchopulmonary aspergillosis (ABPA).
Common oral antifungal medicines include:
- Itraconazole
- Voriconazole
- Posaconazole
- Isavuconazole
Other antifungal medicines, including intravenous treatments, may be used in particular circumstances.
Why treatment can take time
Antifungal medicines do not always produce an immediate improvement. In chronic infections, it may take weeks or months to assess the full response.
Doctors consider symptoms, blood tests, scans and other investigations when deciding whether treatment is working.
A change of antifungal does not necessarily mean that treatment has failed. Sometimes a different medicine is chosen because of side effects, drug interactions, resistance or difficulties achieving adequate drug exposure.
Why antifungal blood levels matter
Some antifungal medicines are absorbed or processed differently from person to person. Measuring the amount of medicine in the blood is called therapeutic drug monitoring (TDM).
TDM is routinely used for itraconazole, voriconazole and posaconazole in many clinical settings. Routine TDM is not generally required for isavuconazole, although it may be considered in particular circumstances.
Blood tests may also be needed to monitor liver function and other potential treatment effects.
Carers can help by keeping track of blood test appointments and checking that the patient knows how and when to take their medicine. Some antifungals have specific instructions about food, timing or other medicines.
Steroids and Anti-inflammatory Treatment
In allergic forms of aspergillosis, particularly ABPA, much of the illness is caused by an excessive immune response to Aspergillus.
Corticosteroids, such as prednisolone, can reduce this inflammation and may improve symptoms.
However, steroids can also cause side effects, especially at higher doses or when used for prolonged periods.
Carers may notice:
- Mood changes or irritability
- Difficulty sleeping
- Increased appetite or weight gain
- Raised blood sugar
- Muscle weakness
- Increased susceptibility to infections
- Changes in skin or bone health with longer-term treatment
These effects can influence everyday life and relationships. Sometimes changes in mood or sleep are caused partly by the treatment rather than the illness itself.
Why steroids must not be stopped suddenly
Long-term steroid treatment can suppress the adrenal glands, reducing the body's ability to produce its own cortisol.
Stopping steroids abruptly, or reducing the dose too quickly, can cause serious problems in someone whose adrenal function has been suppressed.
Important: Patients should not stop or change steroid treatment without medical advice. Anyone with known adrenal insufficiency should follow their individual steroid replacement and sick-day instructions.
Antifungals and inhaled steroids
Some azole antifungal medicines can increase exposure to certain corticosteroids, including inhaled or nasal steroids. This can increase the risk of steroid side effects and adrenal suppression.
Clinicians and pharmacists should review these combinations carefully. Carers can help by ensuring that inhalers, nasal sprays, creams and tablets are all included on the patient's medicine list.
Biologic Treatments
Some people with severe asthma, allergic inflammation or ABPA may be offered biologic medicines.
These treatments target particular parts of the immune system involved in inflammation.
Examples used for severe asthma and, in selected circumstances, ABPA include omalizumab, mepolizumab, benralizumab, dupilumab and tezepelumab.
Their suitability depends on the individual patient's condition, eligibility and specialist assessment. Not all biologics are specifically licensed for ABPA.
Biologic treatments may help improve asthma control, reduce exacerbations or reduce the need for oral steroids in suitable patients.
Carers may find it useful to understand:
- Why a particular biologic has been recommended
- How the clinical team will assess whether it is helping
- Whether injections are given at home or in a clinic
- Which side effects should be reported
- Whether other treatments need to continue
Biologics do not automatically replace antifungal medicines or other prescribed treatments.
Why Monitoring and Blood Tests Matter
Monitoring is an important part of aspergillosis treatment. It helps clinicians check both whether a medicine is effective and whether it is causing unwanted effects.
Depending on the treatment, monitoring may include:
- Antifungal blood levels
- Liver function tests
- Kidney function and electrolyte tests
- Blood counts or blood sugar measurements
- Assessment of possible steroid side effects
- ECG monitoring for medicines that may affect heart rhythm
- Lung function tests, imaging or other assessments of disease activity
Not every patient needs every test. The monitoring schedule depends on the medicine, other health conditions and the treating team's recommendations.
Regular blood tests do not necessarily mean something is wrong. They are often a routine part of keeping treatment safe.
Carers can help by keeping a calendar of appointments and encouraging the patient to ask about results that have not been communicated.
Recognising Possible Side Effects
Side effects vary between medicines and between individuals. Some are mild and temporary, while others require treatment changes or prompt assessment.
Possible symptoms include:
- Nausea, abdominal discomfort or poor appetite
- Unusual tiredness or weakness
- Changes in sleep or mood
- Skin rashes or increased sensitivity to sunlight
- Visual disturbances with certain antifungal medicines
- Dizziness, tingling or other neurological symptoms
- Swelling or changes in blood pressure
Not every new symptom is caused by medication. The underlying illness or another health condition may be responsible.
It can be helpful to record:
- When the symptom began
- Whether a medicine was recently started or changed
- How severe the symptom is
- Whether it is improving or worsening
- Any other changes in health or treatment
These observations can help the clinical team decide whether further investigation or a treatment adjustment is needed.
Understanding Drug Interactions
Drug interactions are particularly important with azole antifungal medicines.
An interaction occurs when one medicine changes the effect, concentration or absorption of another medicine.
Some interactions can increase the risk of side effects. Others can reduce the effectiveness of treatment.
Important combinations may involve:
- Corticosteroids, including certain inhalers and nasal sprays
- Some medicines used for heart conditions
- Blood thinners
- Medicines that reduce stomach acid
- Immunosuppressive medicines
- Certain antibiotics and other antifungals
- Herbal remedies and supplements
For example, some acid-suppressing medicines can interfere with the absorption of certain itraconazole formulations. Other medicines may affect the way azole antifungals are broken down by the body.
Always check before adding or changing medicines. Patients should tell their pharmacist or prescribing clinician about all medicines they use, including those bought without a prescription.
Carers do not need to memorise every possible interaction. The most useful contribution is helping maintain a complete and accurate medication list.
How Carers Can Help Safely
Carers can provide valuable support without needing to become medication experts.
Keep an up-to-date medicine list
Include prescribed tablets, inhalers, nasal sprays, injections, creams, supplements and over-the-counter medicines.
Record the dose and timing where possible, and note any recent changes.
Help with appointments and monitoring
Keeping track of blood tests, clinic appointments and prescription renewals can reduce stress and help prevent missed monitoring.
Watch for changes
Carers may notice changes in mood, sleep, appetite, energy or general wellbeing that the patient has not recognised.
Recording these observations can make them easier to discuss with the clinical team.
Encourage questions
Useful questions for appointments include:
- What is this medicine intended to achieve?
- How long might it take to work?
- What monitoring is needed?
- Which side effects should we report?
- Are there medicines or supplements that should be avoided?
- What should we do if a dose is missed or the person cannot keep medicines down?
Missed-dose instructions differ between medicines, so it is best to follow the specific advice provided by the pharmacist or treating team rather than automatically doubling the next dose.
Respect the patient's independence
Not everyone wants the same level of assistance. Discuss what help is welcome and involve the patient in decisions wherever possible.
When to Seek Medical Advice
Contact the treating team promptly if someone develops new or concerning symptoms after starting or changing treatment, particularly:
- A new or worsening rash
- Persistent vomiting or difficulty keeping medicines down
- Yellowing of the skin or eyes, dark urine or unusual abdominal pain
- New visual disturbances, dizziness or neurological symptoms
- Marked weakness, faintness or symptoms that could suggest a problem with steroid treatment
- Significant or unexplained deterioration in general health
When emergency help is needed
Call 999 in the UK if the person develops:
- Severe difficulty breathing
- Collapse or loss of consciousness
- Seizures
- Severe confusion or difficulty remaining awake
- Signs of a serious allergic reaction, such as swelling of the tongue or throat or breathing difficulty
People with known adrenal insufficiency should follow their emergency steroid plan and seek urgent medical help if an adrenal crisis is suspected. Persistent vomiting may prevent oral steroid replacement from being absorbed.
Do not stop or change prescribed treatment independently unless instructed by a healthcare professional or the person's individual emergency plan.
Further Information
Managing medicines for aspergillosis can be complicated, especially when several treatments are being used together.
Carers can make an important contribution by helping with organisation, noticing possible side effects and supporting communication with healthcare professionals.
For more information, explore our Treatment of Aspergillosis guide.
Patients and carers can also join the National Aspergillosis Centre patient support meetings to share experiences and discuss practical challenges.
Remember: A treatment change does not always mean that the disease is getting worse. Sometimes it means the clinical team is finding a safer or more effective approach for the individual patient.
Author: Aspergillosis Patient Support Team
Editorial update: 19 October 2026
Next scheduled review: October 2028
This article provides general information and does not replace individual advice from a doctor or pharmacist. Clinical review attribution should reflect an actual completed review.
Energy Pacing for Carers: Helping Someone with Aspergillosis Manage Their Energy
One of the hardest things for carers to understand is why someone with aspergillosis can seem reasonably well one day and then be exhausted for the next day or two. This guide explains why energy can be so limited, why pacing matters, and how carers can help without taking over.
Key Points
- Fatigue in aspergillosis is real, physical and often unpredictable.
- People may need to spread activities carefully across the day or week.
- Doing too much on a “good day” can lead to a “crash” afterwards.
- Pacing is not laziness; it is a practical way of managing limited energy.
- Carers can help by supporting a steady, sustainable rhythm rather than pushing through exhaustion.
Contents
- Why energy is limited in aspergillosis
- What pacing means
- The boom-and-bust cycle
- A simple way to think about limited energy
- How carers can help
- What not to say on difficult days
- Common questions carers ask
Why energy is limited in aspergillosis
Many people with aspergillosis live with a combination of breathlessness, coughing, inflammation, poor sleep and the physical strain of chronic illness. Even when they are sitting still, their body may be using more energy than expected.
Energy may also be reduced because:
- the lungs may not move oxygen as efficiently as normal
- the immune system may be working hard because of infection, inflammation or allergy
- the effort of breathing may be greater
- sleep may be disrupted by cough, wheeze, discomfort or anxiety
- medications and other health conditions may also contribute to tiredness
This means that ordinary activities such as showering, shopping, cooking, talking for a long time, going to appointments or dealing with stress can take far more out of someone than other people realise.
What pacing means
Pacing means planning activity in a way that protects limited energy. Instead of using all available energy at once, the person spreads it more carefully through the day or week.
Pacing often involves:
- breaking jobs into smaller steps
- resting before exhaustion becomes severe
- alternating activity with rest
- choosing which tasks matter most
- accepting that not everything can be done on the same day
The aim is not to avoid all activity. The aim is to avoid exhausting the body so much that recovery takes days.
The boom-and-bust cycle
Many people with chronic illness get caught in a “boom-and-bust” cycle. On a better day, they try to catch up with everything they have missed. They may do household jobs, go out, make phone calls, attend appointments and try to feel “normal” again.
The problem is that this often leads to a crash afterwards, with much worse fatigue, breathlessness or exhaustion for the next day or two.
This can be frustrating for carers too. A good day may seem to suggest recovery, only for the person to feel very unwell again soon afterwards. Often this is not a setback in the illness itself, but the effect of spending too much limited energy at once.
A simple way to think about limited energy
Some people find it helpful to imagine that each day begins with a limited number of “spoons” or units of energy. Healthy people may have enough energy that they do not need to think much about it. But someone with aspergillosis may have far fewer spoons to spend.
For example, getting washed and dressed may use one spoon. Preparing a meal may use another. A hospital appointment may use several. If all the spoons are used early in the day, there may be nothing left for the evening or even the next day.
This idea is not perfect, but it can help carers understand that energy needs to be budgeted carefully. It also helps explain why someone may cancel plans, stop halfway through a task, or need to rest after something that appears minor.
How carers can help
Carers can make pacing easier by helping the person protect energy rather than spend it all at once.
- Encourage rest before exhaustion becomes severe
- Help break larger jobs into smaller steps
- Accept that some tasks may need to wait
- Help prioritise what really matters that day
- Offer practical help with high-effort tasks such as shopping, carrying, cleaning or transport
- Try not to judge energy levels by appearance alone
- Recognise that emotional stress can use energy too
Sometimes the most helpful question is not “Can you do this?” but “Is this worth spending your energy on today?”
What not to say on difficult days
Even well-meaning comments can feel painful when someone is exhausted.
Comments that may be unhelpful include:
- “But you were fine yesterday.”
- “Maybe you just need to push through it.”
- “You need to do more and build your stamina.”
- “You look alright to me.”
More helpful responses might be:
- “It sounds as though your body has had enough today.”
- “What is the most important thing to save your energy for?”
- “What can I help with?”
- “Let’s slow things down.”
Common questions carers ask
Should I encourage them to do more?
Gentle activity can be helpful for many people, but repeatedly pushing past exhaustion is usually not. The balance is often between staying active enough and avoiding a crash.
Why can they do something one day but not the next?
Because energy levels in chronic illness often fluctuate. The cost of one activity may also only become obvious later.
Is pacing “giving in” to the illness?
No. Pacing is often a practical, sensible way of living better with limited energy.
Further Information
Pacing can be one of the most important day-to-day tools for people living with aspergillosis and for those who support them. Understanding limited energy often reduces frustration for everyone involved.
Author: Aspergillosis Patient Support Team
Reviewed by: National Aspergillosis Centre
Last reviewed: March 2026

When Someone with Aspergillosis Has a Bad Day: A Guide for Carers

People living with aspergillosis sometimes experience days when symptoms worsen or their energy levels suddenly drop. These days can be stressful and worrying for carers. This guide explains possible reasons, practical ways to help, and how to recognise symptoms that need medical attention.
Key Points
- People with aspergillosis and other chronic lung conditions may experience fluctuations in symptoms and energy.
- A difficult day does not necessarily mean the aspergillosis is getting worse, but new or worsening symptoms should not automatically be dismissed as a flare-up.
- Practical help, rest and pacing may make difficult days easier to manage.
- Carers should know which symptoms require medical advice and which may be emergencies.
Contents
- Why Bad Days Happen
- Symptoms That May Change
- How Carers Can Help
- Providing Emotional Support
- When to Seek Medical Help
- Further Support
Why Bad Days Happen
People living with aspergillosis may have days when they feel noticeably worse than usual. There are several possible explanations:
- Physical activity that has exceeded their available energy
- Poor sleep or accumulated fatigue
- Stress or emotional strain
- Changes in airway inflammation
- A respiratory infection or worsening of an underlying lung condition
- Changes in aspergillosis activity or complications
- Side effects of medicines or other health problems
Not every difficult day represents a flare-up of aspergillosis. Equally, a new infection or significant deterioration should not be assumed to be ordinary fatigue.
It helps to understand what is normal for the person and recognise when symptoms are different from their usual pattern.
Symptoms That May Change
The symptoms experienced during a difficult day depend on the type of aspergillosis and any underlying lung disease.
Changes may include:
- Greater tiredness or exhaustion
- Increased breathlessness
- More frequent coughing
- Changes in the amount or appearance of sputum
- Chest discomfort
- Reduced appetite
- Difficulty concentrating or feeling mentally exhausted
For some people, fatigue is the main difficulty. Others may experience changes in breathing or coughing that require closer attention.
How Carers Can Help
During a difficult day, simple practical support can make a substantial difference.
- Ask what would help. Avoid assuming the person needs the same support every time.
- Encourage pacing. Help reduce non-essential activities and allow time for recovery.
- Offer practical assistance. Meals, shopping, household tasks and appointments may become difficult.
- Support prescribed treatment. Help the person follow their agreed treatment plan without changing medication or doses independently.
- Notice changes. Pay attention to symptoms that are unusual, persistent or worsening.
- Respect independence. Offer help without taking over tasks the person wants and is able to manage.
Fatigue associated with chronic lung disease can be profound. It is not simply ordinary tiredness or a lack of motivation.
Providing Emotional Support
Difficult days can be discouraging. The person may feel frustrated, frightened, isolated or guilty about needing additional help.
Helpful approaches include:
- Listening without judgement
- Acknowledging how difficult the symptoms feel
- Asking whether the person wants practical help, company or quiet time
- Avoiding pressure to push through severe fatigue
- Recognising that emotional distress and physical symptoms can affect one another
Rather than saying that a worsening of symptoms is normal, it may be more helpful to say: “I can see today is particularly difficult. Is there anything different about how you're feeling that we should pay attention to?”
Carers also need rest and support. Looking after someone with a long-term illness can be demanding, and it is reasonable to ask others for help.
When to Seek Medical Help
Seek emergency help
Call 999 in the UK if the person develops:
- Severe difficulty breathing, particularly if they cannot speak normally or are struggling for air
- Sudden severe chest pain, especially with breathlessness, sweating or collapse
- New severe confusion, collapse or difficulty remaining awake
- Coughing up a substantial amount of blood or bleeding accompanied by breathing difficulty, faintness or rapid deterioration
Seek prompt medical advice
Contact the person's GP, specialist team or NHS 111 if they develop:
- Breathlessness that is worse than usual
- A new fever or symptoms suggesting a chest infection
- New blood in their sputum, even if the amount is small
- A significant change in sputum, coughing or chest discomfort
- Fatigue or weakness that is unusually severe, persistent or unexplained
- Symptoms that continue to worsen rather than returning towards their usual level
People who have an individual emergency or respiratory action plan should follow that plan. Those with a history of significant haemoptysis may have specific instructions from their specialist team.
Further Support
For more advice about managing limited energy, read our guide to Energy Pacing for Carers.
Carers and patients may also benefit from the patient support meetings hosted by the National Aspergillosis Centre.
Sharing experiences with others living with aspergillosis can provide reassurance and practical suggestions, although peer support should not replace medical assessment when symptoms change significantly.
Author: Aspergillosis Patient Support Team
Last editorial review: 19 October 2026
Next scheduled review: October 2028
This information is intended to support carers and does not replace individual medical advice. Clinical review attribution should only be added where a review has actually been completed.