


Talking to Friends and Family about Aspergillosis
Aspergillosis can be difficult to explain to friends and family.
Most people have never heard of it. The different forms of aspergillosis can be confusing, symptoms may not always be visible, and the illness can affect people very differently.
If you have recently been diagnosed, you may still be trying to understand it yourself. You do not need to become an expert before talking to the people around you.
Often, the most useful thing is simply to help them understand what aspergillosis means for you and what kind of support would actually help.
Last updated: 9 September 2026
Last reviewed: 9 September 2026
Why aspergillosis can be difficult to explain
The word Aspergillus refers to a common mould, but aspergillosis is not one single illness.
Some people have an allergic reaction to Aspergillus, some develop long-term infection in damaged lungs, and others may have different forms of disease. Treatment and symptoms therefore vary considerably from one person to another.
If someone wants a simple introduction, our What is aspergillosis? page explains the main types and how they affect people.
You do not have to explain every medical detail at once. Starting with a few important points is often easier for everyone.
Decide what you want them to understand
Before starting the conversation, it can help to think about what you actually want the other person to know.
For example:
- that aspergillosis is a real and sometimes serious long-term condition
- that your symptoms can vary from day to day
- that fatigue or breathlessness may limit what you can do
- that treatment may take a long time or cause side effects
- that you may sometimes need practical help
- that you still want to be treated as yourself, rather than only as someone who is ill
You may not need to cover all of these things in one conversation.
Explain it simply
Medical terminology can make aspergillosis sound more complicated than it needs to be.
You might start with something such as:
“I have a lung condition caused by my body reacting to, or being infected by, a common mould called Aspergillus. It can affect my breathing and energy levels, and I may have better and worse periods.”
You can then explain your particular diagnosis and treatment if the person wants to know more.
It is perfectly reasonable to say:
“I’m still learning about it myself.”
You do not have to know the answer to every question.
Explain what it is like for you
Friends and family may understand the name of the illness without understanding what living with it actually involves.
That is often the more important conversation.
You might explain:
- what breathlessness feels like
- how fatigue affects your day
- whether coughing interrupts sleep or activities
- how frequently you attend hospital or have tests
- whether medicines cause troublesome side effects
- which activities have become more difficult
- what happens during a bad period or infection
Specific examples are often easier to understand than saying simply that you are “tired” or “unwell”.
“But you look well”
Many symptoms of aspergillosis are not obvious to other people.
Someone may look well while experiencing significant fatigue, breathlessness, coughing, pain, poor sleep or medication side effects.
This can sometimes create misunderstandings.
A friend may see you going out one day and assume that you should be able to do the same thing the following day. In reality, symptoms and energy levels can fluctuate considerably.
Being able to do something does not necessarily mean it was easy — or that it did not have consequences afterwards.
It can help to explain that you may need to pace your activities, rest after exertion or change plans at short notice.
Fatigue can be particularly hard to explain
Fatigue associated with chronic illness is not always the same as ordinary tiredness.
Rest may help, but it may not completely restore your energy.
Some people find it helpful to think of energy as a limited daily budget. Necessary activities — showering, dressing, shopping, attending an appointment or preparing food — all use some of that energy.
On a difficult day, relatively ordinary tasks may use most of what is available.
This can help family members understand why deciding not to attend an event or asking for help with a task is not simply a matter of motivation.
Be specific about what helps
People often genuinely want to help but do not know what to do.
“Let me know if you need anything” is kindly meant, but it still leaves the person who is unwell having to decide what to ask for.
It can be easier to suggest something specific.
For example:
- driving you to an appointment
- coming with you to a consultation
- picking up some shopping
- helping with a physically demanding household task
- checking in during a difficult week
- meeting somewhere that does not require a lot of walking
- understanding when plans need to change
- simply listening without immediately trying to solve the problem
Small practical changes can make a substantial difference.
People may react differently from the way you expect
Telling someone about a long-term illness can produce all sorts of reactions.
Some people immediately want to know everything. Others may become worried, change the subject or try to reassure you by saying that it “doesn't sound too bad”.
This does not necessarily mean they do not care.
They may be unsure what to say or may need some time to absorb what you have told them.
If something they say is unhelpful, you can gently explain what you need instead.
For example:
“I know you’re trying to reassure me, but it actually helps more when you acknowledge that this can be difficult.”
When friends or family do not understand
Occasionally, someone may continue to underestimate the effects of your illness even after you have tried to explain it.
You cannot always make another person understand.
It may help to give them reliable information to read, invite them to an appointment where appropriate, or ask another family member to help explain what has changed.
Sometimes you may also need to set boundaries around what you can realistically do.
Protecting your health is not the same as rejecting friends or family.
Let people learn with you
You do not need to carry all the responsibility for educating the people around you.
Friends, relatives and carers can use the Carers & Family Hub to learn more about aspergillosis and about supporting someone living with a long-term condition.
They may also find it helpful to read the information relevant to your particular type of aspergillosis.
If they attend an appointment with you, it may help to agree beforehand what role you would like them to have — for example, listening, taking notes or helping you remember questions.
For family and friends: how you can help
If someone close to you has aspergillosis, one of the most useful things you can do is listen to how the illness affects them.
Try not to assume that you know how they feel because they look well, or because they managed a particular activity previously.
You can help by:
- believing them when they describe their symptoms
- asking what kind of support would be useful
- being flexible when symptoms alter plans
- learning a little about their condition
- avoiding pressure to “push through” severe fatigue or breathlessness
- allowing them to remain as independent as possible
- remembering that they are still the same person you knew before their diagnosis
If you provide regular practical or emotional support, our guide to coping when caring becomes overwhelming also explains why carers need support of their own.
You are more than your illness
Talking openly about aspergillosis can make life easier, but it does not have to become the centre of every conversation.
You are still a partner, parent, friend, colleague, neighbour or grandparent — and you still have interests, opinions and plans that have nothing to do with aspergillosis.
Good support means recognising the illness without allowing it to define the whole person.
Helping friends and family understand aspergillosis can take time. You do not have to explain everything at once.
A little more understanding can make it easier for the people around you to provide the kind of support that is genuinely useful.


Living Well with Aspergillosis: Understanding Palliative and Supportive Care
The words palliative care can be frightening. Many people hear them and immediately think that treatment is stopping or that someone must be approaching the end of life.
But palliative care is broader than end-of-life care. Its purpose is to improve quality of life by helping with difficult symptoms and the physical, emotional, social and practical effects of serious illness.
Importantly, palliative care can be provided alongside active treatment. For someone with aspergillosis, this could mean continuing antifungal medicines, inhalers or other treatment while also receiving additional help with symptoms, wellbeing or planning for the future.
Last updated: 9 September 2026 and Last reviewed: 9 September 2026.
What is palliative care?
Palliative care focuses on the person as well as the disease.
Depending on someone's needs, it can include help with:
- breathlessness, pain, cough and other difficult symptoms;
- fatigue and reduced ability to manage everyday activities;
- anxiety, low mood or fear about the future;
- practical and social difficulties caused by illness;
- support for family members and carers;
- understanding priorities and making plans for future care.
Some of this support may be provided by your existing GP, respiratory team, nurses or other healthcare professionals. People with more complex needs may benefit from a specialist palliative care team.
Palliative care is not the same as end-of-life care
The terms are sometimes used together, which can cause confusion.
Palliative care is support aimed at improving quality of life for people living with serious or life-limiting illness. It may be appropriate alongside active treatment and can sometimes be provided over a considerable period.
End-of-life care refers specifically to care for people approaching the end of their lives.
Someone receiving palliative care is therefore not necessarily dying, and accepting palliative support does not mean that other treatment has been abandoned.
How might supportive or palliative care help someone with aspergillosis?
Aspergillosis affects people very differently. Many people remain relatively stable for long periods, while others have persistent symptoms, progressive lung disease, repeated infections or other health conditions alongside aspergillosis.
For someone whose illness is having a substantial effect on everyday life, additional supportive or palliative care may help.
Managing difficult symptoms
Breathlessness, cough, chest discomfort and fatigue can sometimes remain troublesome even when the underlying lung disease is being treated as effectively as possible.
Supportive care can focus on reducing the impact of these symptoms. This may involve medicines, but symptom management can also include physiotherapy, breathing techniques, rehabilitation, equipment, psychological approaches and changes that make everyday activities easier.
The aim is not to replace treatment for aspergillosis. It is to address the problems that remain despite treatment.
Emotional and psychological support
Living with a long-term lung condition can bring uncertainty, frustration, anxiety and sometimes fear about deterioration or the future.
Supportive care recognises these concerns as part of healthcare rather than something separate from it.
Depending on local services and individual needs, support may involve members of the existing healthcare team, psychological services, counselling, social support or specialist palliative care professionals.
Practical support
Illness can affect mobility, independence, work, finances and the ability to manage everyday tasks.
Different members of the wider healthcare and social-care team may be able to help with equipment, adaptations, rehabilitation, benefits or care needs.
Not all of this is technically “palliative care”. What matters is identifying the problems that are affecting someone's quality of life and finding the most appropriate source of help.
Support for family members and carers
Serious or long-term illness affects more than the person with the diagnosis.
Partners, relatives and friends may gradually take on more responsibility: attending appointments, organising medicines, providing transport, managing the home or supporting someone through periods of worsening health.
They may also be coping with uncertainty and their own worries about the future.
Supportive and palliative care should recognise the needs of families and carers as well as those of the patient. Depending on the service, this may include information, emotional support, help with planning, advice about practical support or signposting to carer services.
See our guide Practical Support for Carers of Someone with Aspergillosis.
When might it be worth asking about additional support?
There is no single point at which everyone with aspergillosis should receive palliative care. Support should be based on individual needs.
It may be worth discussing additional supportive or palliative care with your healthcare team if, for example:
- symptoms such as breathlessness or pain remain difficult to control;
- your health is becoming more difficult to manage despite treatment;
- you are having repeated hospital admissions or significant periods of deterioration;
- several health conditions are making your care particularly complex;
- illness is having a major effect on your independence or quality of life;
- you or your family are finding uncertainty about the future particularly difficult;
- you would like to discuss what matters to you if your health changes in the future.
These do not automatically mean that you need specialist palliative care. They are reasons to have a conversation about what additional support might be useful.
How do I ask for help?
You can start with your GP, respiratory team, specialist nurse or another healthcare professional involved in your care.
You do not necessarily have to ask specifically for “palliative care”. You can explain the problem you want help with.
For example:
“My breathlessness is still having a major effect on everyday life even though we're treating my lung condition. Is there any additional symptom support available?”
Or:
“We're finding the uncertainty about my health difficult. I'd like to talk about what might happen in the future and what support would be available.”
Your healthcare team can then consider whether help is best provided through your existing services, rehabilitation, psychological or social support, community services, a hospice service or a specialist palliative care team.
Does palliative care mean going into a hospice?
No.
Hospices provide much more than inpatient care. Depending on local services, they may offer outpatient appointments, symptom-management clinics, rehabilitation, psychological or family support, day services, telephone advice and care in people's homes.
Many people receiving supportive or palliative care never stay in a hospice.
Services vary considerably between areas, so your GP or healthcare team can advise what is available locally.
Planning ahead
Some people want to think about what would matter to them if their health became worse. Others are not ready to have those conversations, particularly when they have only recently been diagnosed.
There is no need to make every possible decision at once.
Planning ahead can simply begin with conversations about:
- what matters most to you;
- what you hope treatment will help you continue doing;
- what worries you about the future;
- who you would like involved in decisions;
- where and how you would prefer to receive care if your needs increased.
These conversations can form part of personalised care and support planning and can be reviewed as circumstances or preferences change.
Advance care planning
For some people, particularly those with progressive or advanced illness, planning may eventually include more formal decisions about future healthcare.
This can include recording wishes and preferences, considering who should make decisions if you lose the ability to make them yourself, and discussing treatments that might or might not be appropriate in particular circumstances.
These are important decisions and should be discussed carefully with healthcare professionals who understand your health and circumstances.
Planning ahead is about having more control over future care, not assuming that deterioration is inevitable or imminent.
What if someone suggests palliative care to me?
Hearing the words “palliative care” can be unsettling, particularly if nobody explains why the subject has been raised.
Ask what the healthcare professional means and what particular problem they think the service could help with.
You might ask:
- Why do you think this would help me now?
- What support would the team actually provide?
- Would my current treatments continue?
- Would my respiratory or aspergillosis team still be involved?
- Is this mainly for symptom control, planning ahead, or both?
A referral for palliative care should not mean that decisions are being made about you without you. You should understand what is being proposed and have the opportunity to discuss what matters to you.
What if I think I need more support but it has not been offered?
Tell your healthcare team what is becoming difficult.
Rather than assuming that a particular service is the answer, explain the unmet need — difficult symptoms, emotional distress, practical problems, repeated deterioration or worries about future care.
Different areas organise supportive and palliative services differently, and not everyone will need a specialist palliative care referral. Your healthcare team can help identify the most appropriate service for your situation.
For family members and carers
If the person you support wants you involved, you can help them think about what matters most and what questions they would like to ask.
It can be tempting to push for conversations about the future because you are worried yourself. Try to follow the person's pace where possible. Some people want detailed information and early planning; others prefer to deal mainly with what is happening now.
Carers can also ask for help for themselves. Caring for someone with complex or worsening illness can become exhausting, and needing additional support does not mean that you have failed.
See When Caring Becomes Overwhelming: Support for Family Carers.
Finding reliable information and support
There are national organisations that provide reliable information about palliative and supportive care, hospices, planning ahead and support for families.
See our Trusted Online Resources for Palliative and Supportive Care for organisations and further information.
The key message
Palliative care is not synonymous with dying, and it is not about giving up on treatment.
For some people living with severe, complex or progressive aspergillosis, supportive or palliative care can provide another layer of help alongside treatment of the underlying disease.
The important question is not simply, “Am I ready for palliative care?”
A more useful question may be:
“What problems are making life difficult now, and what additional support could help?”

🌐 Trusted Online Resources for Palliative and Supportive Care
If you are looking for more information about palliative or supportive care, it can be difficult to know where to start. The organisations below provide reliable information about symptom support, living with serious illness, help for families and carers, local services and planning ahead.
You do not need to be approaching the end of life to find some of these resources useful. Palliative and supportive care can sometimes provide additional help alongside treatment for your underlying condition.
If you are new to the subject, you may want to start with our guide Living Well with Aspergillosis: Understanding Palliative and Supportive Care.
1. Marie Curie UK
🔗 https://www.mariecurie.org.uk
One of the UK’s leading providers of end-of-life support.
-
Clear guides on what palliative care is
-
Advice on symptom management, emotional support, and practical issues
-
Online chat and helpline: 0800 090 2309
-
Information for families and carers
2. Hospice UK
🔗 https://www.hospiceuk.org
National charity supporting over 200 hospices in the UK.
-
Search tool to find local hospice services
-
Guidance on advance care planning, DNACPR, and choosing care settings
-
Support for people receiving palliative care at home
3. NHS: Palliative and End of Life Care
🔗 https://www.nhs.uk/conditions/end-of-life-care/
Official NHS overview of palliative care.
-
Describes when and how palliative care is offered
-
Explains where care can happen (home, hospital, hospice)
-
Advice on legal planning, such as Advance Decisions and Lasting Power of Attorney
4. Good Life, Good Death, Good Grief (Scotland)
🔗 https://www.goodlifedeathgrief.org.uk
Scottish-based initiative that helps people plan ahead.
-
Leaflets on how to talk about death and dying
-
"Planning Ahead" toolkit for people with long-term illness
-
Supports both patients and professionals
5. Compassion in Dying
🔗 https://www.compassionindying.org.uk
Specialist in advance care planning and patient rights.
-
Downloadable Advance Statement and Advance Decision forms
-
Free support to write a Living Will
-
Helpline: 0800 999 2434
6. Palliative Care Adult Network Guidelines (PCANG)
🔗 https://book.pallcare.info/
Clinical guidelines, but useful for patients seeking clarity on symptom control (e.g. breathlessness, cough, fatigue).

European Aspergillosis PAG at ERS 2026: from patient to partner
People living with aspergillosis have knowledge that cannot be found in a scan, blood test or textbook: what it is really like to seek a diagnosis, manage treatment, cope with uncertainty and keep living life. The European Aspergillosis Patient Advisory Group (PAG) is making sure that experience helps shape the future.
From patient to partner
At the 2026 European Respiratory Society (ERS) Congress, the PAG presented a poster describing how a small European patient network has grown over two years—from people receiving information and support to partners helping shape education, research and awareness.
Its message was simple: involving people with lived experience early helps projects ask better questions, use clearer language and reflect the realities of day-to-day life with aspergillosis.
What is the European Aspergillosis PAG?
The European Aspergillosis PAG was established within the European Lung Foundation to bring patient perspectives into CPAnet, the ERS Clinical Research Collaboration for chronic pulmonary aspergillosis. It has developed in collaboration with the National Aspergillosis Centre and Aspergillosis Trust.
Its active members bring experience from six European countries: the United Kingdom, Belgium, Denmark, the Netherlands, Portugal and Ireland. Together, they are building a bridge between patients, clinicians, researchers and patient organisations.
What has the group been doing?
The PAG’s contribution is practical, not tokenistic. Members have helped to:
- identify priorities and shape research questions;
- review study plans, participant information and recruitment materials;
- co-produce leaflets, webinars, presentations and other patient education;
- make research findings clearer and more useful for patients;
- share lived experience at meetings, conferences and awareness events; and
- help build a more connected international aspergillosis community.
Over the past two years, this has included patient meetings, World Aspergillosis Day activity, an online event with participants from 49 countries, and resources made available in nine languages.
Why it matters: a research project or information resource may be scientifically excellent, but it will work better if it also makes sense in real life—when someone is tired, worried, managing several medicines or trying to explain a rare disease to family, friends or an employer.
ERS: taking patient involvement into the respiratory community
ERS is one of the world’s major meetings for respiratory medicine. It brings together clinicians, researchers, allied health professionals and patient organisations to share new evidence, develop collaborations and discuss the future of lung health. For a rare disease such as aspergillosis, it is an important place to be seen and heard.
Presenting at ERS made the PAG’s work visible to the wider respiratory community. It helped show that people affected by a rare fungal lung disease can contribute to better research, better information and better care—not simply as participants, but as collaborators. Being in the room also helps ensure that patient priorities are considered early, while studies, resources and services are still being designed.
It also helps connect aspergillosis with the broader respiratory community. Many people with aspergillosis are cared for alongside asthma, bronchiectasis, COPD, tuberculosis or other lung conditions. Raising awareness at ERS can help more professionals recognise the disease, understand its impact and know where specialist expertise and patient support can be found.
The poster followed the journey from lived experience, through connection and support, to confidence to contribute, collaboration and patient partnership and leadership.

“It was a really proud moment standing there and sharing what we have achieved together over the last two years. What started as a small group of patients has grown into a European network, and it’s wonderful to see the work we are doing being shared in this setting with delegates, clinicians and researchers from across Europe and beyond.
But most importantly, this is our story. Every one of you has contributed to it through your experiences, ideas, time and willingness to get involved.
For me, seeing patients represented in this arena and being able to talk about what we are achieving together means a huge amount.
So I just wanted to say thank you and how incredibly proud I am of our PAG and everything we have achieved so far. And I think we can be proud that this is only the beginning.”
Lisa McNeil, European Aspergillosis Patient Advisory Group
Could you get involved?
You do not need to be an expert, to speak at conferences or to have all the answers. The most valuable starting point is your experience of living with aspergillosis.
There are different ways to contribute. Some people may want to review a leaflet or survey; others may join an online discussion, share views on a research question, help improve patient information or simply hear about opportunities as they arise. Participation should fit around your health, energy and confidence.
If you would like to hear more about the European Aspergillosis PAG and future opportunities to get involved, please register your interest here.
Working together, with clear boundaries
The PAG works with ERS projects, ERS-funded activities and non-commercial research. It does not work directly with commercial organisations or industry-sponsored projects. This helps ensure that patient involvement remains independent, respectful and focused on what matters to people living with aspergillosis.
Every contribution matters. By sharing experience, patients can help make the next leaflet clearer, the next study more relevant and the next step in care more responsive to real life.

Prednisolone tapering: mood changes, low cortisol and staying safe
Prednisolone can be an important treatment for some forms of aspergillosis, particularly allergic bronchopulmonary aspergillosis (ABPA). It reduces harmful inflammation, but it can also affect how you feel emotionally. This article explains why a change in mood during a steroid taper deserves to be taken seriously.
Can reducing prednisolone affect mood?
Yes, it can. Feeling unusually low, anxious, irritable, tearful, overwhelmed or unlike yourself can happen while taking prednisolone. It can also happen while the dose is being reduced. That does not mean the feelings are “all in your head”, nor does it prove that the taper is the only cause. Living with a long-term illness, poor sleep, pain, worries and difficult events can all affect mood too.
The important point is that a noticeable change in mood during a taper is real and worth mentioning to the team managing your steroids.
Why might this happen?
There can be more than one explanation, and they can overlap.
- Prednisolone can affect the brain as well as inflammation. Some people experience anxiety, irritability, sleep problems, low mood or mood swings while taking it. These effects are more likely at higher doses, but can occur at any dose.
- Glucocorticoid withdrawal syndrome. After longer-term treatment, the body has adapted to receiving steroid medicine. Lowering the dose can bring withdrawal symptoms such as fatigue, weakness, aches, sleep disturbance and mood changes. This is a recognised medical problem.
- Recovery of the body’s cortisol system. Long-term prednisolone can temporarily reduce the body’s own production of cortisol. Cortisol helps regulate blood pressure, energy, metabolism and the response to physical stress. Recovery differs greatly between people.
- A flare of the illness being treated. Symptoms of asthma, ABPA or another condition can return as the dose falls. Feeling physically worse can understandably affect sleep and emotional wellbeing.
- Everything else going on in life. Steroid-related changes and ordinary human stress are not mutually exclusive. A difficult period may feel much harder while your body is adjusting.
Withdrawal symptoms and adrenal insufficiency are not the same
They can feel similar, which is why it is not safe to diagnose yourself from symptoms alone.
| Possible issue | What it means | Possible symptoms |
|---|---|---|
| Prednisolone effects | The medicine itself is affecting mood or sleep. | Anxiety, low or high mood, irritability, insomnia, racing thoughts or feeling emotionally labile. |
| Glucocorticoid withdrawal syndrome | The body is adjusting as a steroid dose is lowered. Cortisol production may be adequate. | Fatigue, weakness, muscle or joint aches, sleep disturbance and mood changes. |
| Glucocorticoid-induced adrenal insufficiency | The body is not yet making enough of its own cortisol after steroid treatment. | Fatigue, weakness, dizziness, nausea, loss of appetite, low blood pressure and feeling very unwell. |
A clinician may need to consider your dose history, the condition being treated and sometimes cortisol testing. The dose is often reduced more slowly as it approaches the amount of cortisol the body normally makes, but there is no single schedule that is right for everyone.
What should I do if I feel low or emotionally unstable during a taper?
- Tell your prescribing team or GP promptly. Describe when symptoms began, recent dose changes, sleep, other physical symptoms and how much daily life is being affected.
- Do not stop prednisolone suddenly or change the taper on your own. If a slower taper, a temporary pause or a short-term dose change is appropriate, this should be agreed with the clinician who knows your situation.
- Keep the basics steady where possible. Take prednisolone exactly as prescribed (usually in the morning), try to protect sleep, eat and drink regularly, and let someone close to you know you are having a difficult time.
- Ask about an adrenal plan if you have been taking steroids for weeks or longer. Your team can tell you whether you need sick-day rules, a steroid emergency card, testing or endocrinology input.
Feeling low during a taper is not a personal failure. It may be a medicine effect, a withdrawal effect, the strain of illness, life stress—or a mixture. You deserve support for it.
If you are admitted to hospital and cannot explain
A common worry is becoming too unwell, drowsy or confused to explain that you take, or have recently reduced, steroid treatment. This matters because people with known or suspected steroid-related adrenal insufficiency may need urgent steroid treatment during a serious illness, injury, operation, vomiting or diarrhoea.
Carry a Steroid Emergency Card if your clinician has advised one. It gives healthcare professionals essential information quickly. A short personal medical summary kept in your wallet and on your phone can also help. Include your diagnosis, current steroid and dose, recent taper, allergies, usual clinical team, emergency contact and any individual sick-day or emergency-injection plan.
Ask your team what should apply to you. Not everyone taking a short course of prednisolone needs an emergency card, but it is particularly important to discuss after longer-term treatment or if you have adrenal insufficiency.
When should I seek urgent help?
Contact NHS 111, your urgent clinical contact or your medical team the same day if you have a significant or worsening mood change, feel unable to cope, become confused, have frightening or unusual thoughts, or develop severe fatigue, vomiting, marked dizziness/fainting, worsening weakness or symptoms of low blood pressure.
Call 999 or go to A&E immediately if you have thoughts of harming yourself or ending your life. If you have known or suspected adrenal insufficiency and are seriously unwell—especially with vomiting, diarrhoea, severe infection, collapse or extreme weakness—follow your personal sick-day/emergency-steroid plan and seek emergency medical help.
A note for family and friends
Someone tapering prednisolone may seem more tearful, irritable, anxious or withdrawn than usual. A calm check-in can be genuinely helpful: ask how they are coping, listen without trying to minimise it, and encourage them to speak to their clinical team. If you are worried about their immediate safety, stay with them and get urgent help.
Further information
- NHS: Side effects of prednisolone tablets and liquid
- European Society of Endocrinology: patient leaflet on glucocorticoid-induced adrenal insufficiency
This information supports, but does not replace, advice from the clinician prescribing your steroids.

Research update: new ABPA treatment results, and lessons from viral infections
This fortnight’s research includes encouraging results for a treatment that may help some people with allergic bronchopulmonary aspergillosis (ABPA), as well as new studies on the relationship between severe viral infections and invasive aspergillosis.
The most important message is that promising research does not automatically change treatment today. It does, however, help clinicians and researchers identify where future care may improve.
Most important: dupilumab in ABPA
A new clinical trial tested dupilumab in 62 people aged 12 and over with asthma and ABPA. Dupilumab is a biologic medicine already used for some types of severe asthma and eczema. It works by reducing two signals involved in allergic, type-2 inflammation.
After 24 weeks, people receiving dupilumab had better lung-function improvement than those receiving placebo. They also had fewer severe respiratory flare-ups. Among people taking regular oral steroid tablets at the start of the study, 71% of those receiving dupilumab no longer needed them after 24 weeks, compared with 14% in the placebo group.
This is an encouraging early controlled trial, particularly for people whose ABPA and asthma remain difficult to manage or who experience steroid side effects. However, dupilumab is not currently an approved treatment specifically for ABPA, the study was relatively small, and longer-term results are still needed. Nobody should change treatment because of this study alone; decisions about biologics need to be made with their specialist team.
Severe influenza and invasive aspergillosis
A large study from 21 intensive-care units in China looked at people admitted with severe influenza A pneumonia. Of 542 critically ill patients, 179 developed invasive pulmonary aspergillosis.
Invasive aspergillosis was usually identified very soon after influenza began, and it was linked with poorer outcomes. Diabetes, bacterial co-infection, kidney replacement therapy and corticosteroid exposure were among factors associated with greater risk.
This study concerns people who were extremely unwell with influenza and needed intensive-care treatment. It does not mean that ordinary seasonal flu commonly causes aspergillosis, or that people living with chronic pulmonary aspergillosis (CPA) or ABPA should be alarmed after every viral illness. It does reinforce the importance of clinicians considering invasive fungal infection when someone with severe flu pneumonia is not improving as expected.
COVID-19, underlying lung disease and Aspergillus
A Korean population study of more than 550,000 people diagnosed with COVID-19 found that COVID-19 was associated with a later diagnosis of respiratory aspergillosis. Diabetes, COPD and other health conditions increased the risk further.
The study included both invasive and non-invasive forms of aspergillosis, and people with both COVID-19 and aspergillosis had poorer COVID-19 outcomes. Because this was a study of health records, it can show an association but cannot prove exactly why it occurs. For example, people needing steroid treatment are often already more seriously unwell.
Again, this should be interpreted calmly. Most people with COVID-19 will not develop aspergillosis. The findings are most relevant to people with severe infection, significant lung disease or immune suppression, and to the clinicians caring for them.
A possible new way to monitor ABPA activity
Total IgE blood testing is widely used to help monitor ABPA. A new study followed 122 people during treatment and examined whether more specific Aspergillus fumigatus IgE tests could add useful information.
One marker, called recombinant Asp f4-specific IgE, rose in all 15 people who had an ABPA exacerbation during follow-up. Total IgE rose in 12 of the 15 people.
This is interesting research, but it is not ready to replace the tests currently used in clinic. Larger studies in different centres are needed first. In future, more specific markers may help clinicians judge whether ABPA is responding to treatment or beginning to flare.
CPA and sarcoidosis
A new review examines CPA in people with sarcoidosis, particularly those with more advanced scarring and cyst-like damage in the lungs. It estimates that CPA affects around 2% of people seen in specialist sarcoidosis centres.
The review highlights the importance of recognising new or changing symptoms, using scans alongside Aspergillus-specific IgG blood tests and microbiology, and planning carefully for problems such as coughing up blood. It is a useful reminder that CPA usually develops where there is pre-existing structural lung damage; it is not simply a matter of being exposed to mould.
Azole resistance remains a worldwide concern
A worldwide review has confirmed that resistance to azole antifungal medicines in Aspergillus fumigatus is an increasing issue. Resistance can emerge during antifungal treatment, but can also arise from environmental exposure to azole-like fungicides used in agriculture.
The review does not suggest that every patient will encounter resistance. Its message is that surveillance, good laboratory testing and access to specialist advice remain important—especially when someone is not responding as expected to antifungal treatment.
What to take from this update
The dupilumab trial is the most hopeful item this fortnight. It offers stronger evidence that a targeted biologic treatment may reduce symptoms, flare-ups and steroid use for some people with ABPA.
The viral-infection studies are a reminder that severe flu and COVID-19 can occasionally create conditions in which invasive aspergillosis becomes more likely—mainly in people who are already seriously ill or vulnerable. They should improve clinical awareness, not create anxiety for everyone living with an Aspergillus-related condition.
This update summarises newly published research for patients, carers and non-specialist healthcare professionals. It does not replace individual medical advice. Please discuss any concerns about symptoms or treatment with your clinical team.
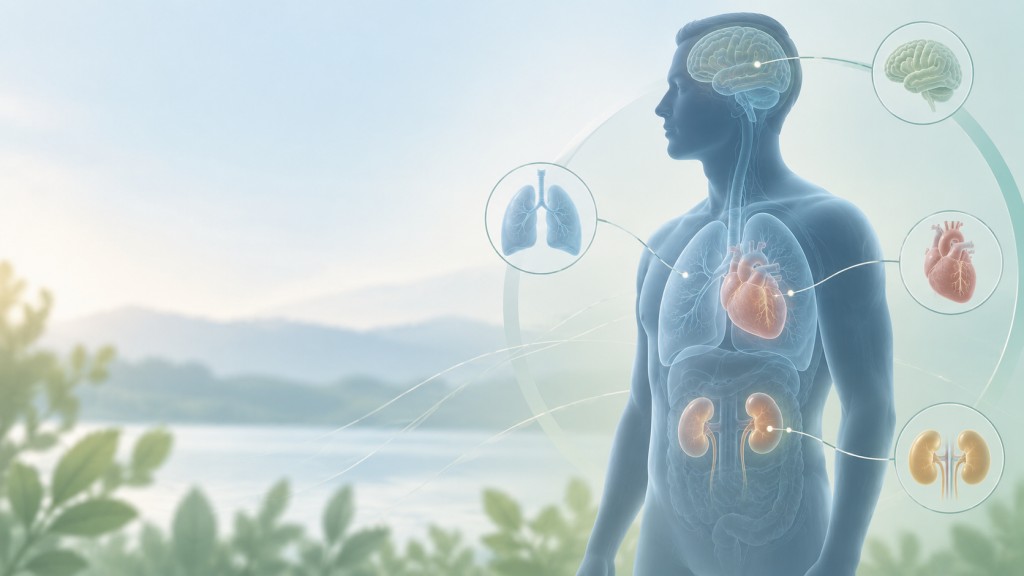
When Aspergillus Affects Other Parts of the Body
Invasive aspergillosis usually starts in the lungs. Rarely, particularly when a person is severely immunocompromised or critically unwell, infection can affect other parts of the body.
This is very different from chronic pulmonary aspergillosis (CPA), ABPA, Aspergillus bronchitis or an aspergilloma. Having one of those long-term conditions does not mean that infection will spread through the body.
Key points
- Rare invasive Aspergillus infections can involve organs outside the lungs.
- They mainly occur in people with major immune suppression, severe illness or particular medical risk factors.
- They are diagnosed and treated by specialist hospital teams.
- Antifungal medicines are central to treatment, but scans, biopsies, drainage or surgery may sometimes be needed.
- These rare infections are not the expected outcome for people with chronic forms of aspergillosis.
Who is most at risk?
Infection outside the lungs is most likely to be considered when a person has invasive aspergillosis and is very unwell, or when their immune system is severely weakened.
This can include some people who are:
- Having intensive chemotherapy for blood cancer
- Experiencing prolonged severe neutropenia
- Receiving a stem-cell, bone-marrow or organ transplant
- Taking high-dose steroids or other strong immune-suppressing medicines
- Critically unwell in hospital, including after severe influenza or another serious viral illness
Rare local infections can also occasionally follow an injury, surgery or a medical procedure. The circumstances are very individual, which is why specialist assessment matters.
Which parts of the body can be affected?
When invasive infection spreads beyond the lungs, it can rarely involve other organs. The symptoms depend on the affected area and on the person’s underlying illness.
Brain and central nervous system
Infection involving the brain or central nervous system is rare and serious. Possible symptoms can include severe or unusual headache, confusion, seizures, weakness, changes in speech, balance problems or visual symptoms. These symptoms have many possible causes, but they need urgent medical assessment in someone known to be at high risk.
Heart and blood vessels
Very rarely, Aspergillus can affect the heart valves or blood vessels. This is usually considered in highly specific hospital situations, such as after major surgery or in someone with substantial immune suppression. It requires specialist infectious-disease, cardiology and surgical input.
Kidneys, bones, joints and skin
Kidney, bone, joint and skin involvement is uncommon. It may occur as part of more widespread invasive infection or, in some cases, after direct injury or a procedure. Symptoms vary widely, so doctors use scans, laboratory tests and sometimes a tissue sample to establish the cause.
Eye and ear infections
Aspergillus can also cause local infections of the ear or eye. These are usually separate local conditions rather than evidence that chronic lung aspergillosis is spreading. Eye symptoms such as pain, redness, sensitivity to light or reduced vision need urgent assessment.
How are these infections diagnosed?
No single test provides every answer. Hospital teams may combine:
- Symptoms and medical history
- CT, MRI or other scans
- Blood tests and fungal markers
- Samples from the lungs, blood, skin or another affected site
- A biopsy or surgical sample when this is needed and safe
Finding Aspergillus in a sample does not automatically prove invasive infection. Results are interpreted alongside scans, symptoms and the person’s immune status.
Treatment and specialist procedures
Invasive Aspergillus infections are treated in hospital by specialist teams. Antifungal medicines are usually the main treatment, chosen according to the site of infection, other medicines, kidney and liver function, possible resistance and the person’s overall condition.
Sometimes a procedure is also needed. This may involve:
- Taking a biopsy or other sample to confirm the diagnosis
- Draining an infected collection of fluid
- Removing damaged or infected tissue where it is safe and helpful to do so
- Specialist surgery for a localised infection, such as one affecting the sinuses, heart or another accessible site
These decisions are made individually. Surgery is not automatically required, and it is never a simple decision when someone is already seriously unwell.
A reassuring distinction
It is understandable to feel worried after reading about rare Aspergillus infections online. However, case reports and medical articles often describe people with very different risks from those of someone living with CPA, ABPA, SAFS or Aspergillus bronchitis.
Chronic forms of aspergillosis need proper monitoring and treatment, but they do not usually develop into infection of the brain, kidneys, heart or other organs. If you are worried about a new symptom, discussing it with your own healthcare team is more useful than trying to compare your situation with an internet story.
When should I seek urgent help?
Seek urgent medical help for severe or rapidly worsening symptoms, including major breathing difficulty, confusion, a severe headache with neurological symptoms, significant change in vision, or a rapid deterioration in how you feel.
If you are having cancer treatment, have had a transplant, are taking strong immune-suppressing medicines, or have recently been seriously ill in hospital, contact your treating team promptly about new or worsening symptoms.
Related information
Visit the Invasive & Acute Aspergillosis Hub
Learn about invasive aspergillosis
Aspergillus infections of the ear, eye and nails
References
- Patterson TF, Thompson GR, Denning DW, et al. Practice guidelines for the diagnosis and management of aspergillosis. Clinical Infectious Diseases. 2016;63:e1–e60.
- Brown JS, Armstrong-James D, Ayling-Smith J, et al. British Thoracic Society Clinical Statement on Aspergillus-related chronic lung disease. Thorax. 2025;80(Suppl 1):3–21.

Flu, COVID-19 and Aspergillus: When Is It a Concern?
Severe viral infections can occasionally be complicated by invasive pulmonary aspergillosis. This is mainly a concern for people who are seriously ill in hospital, particularly intensive care.
The strongest evidence concerns severe influenza and severe COVID-19. Other severe viral pneumonias can also leave the lungs vulnerable, but catching an ordinary cold, flu or COVID-19 at home does not usually lead to Aspergillus infection.
Key points
- Severe influenza and COVID-19 can occasionally be complicated by invasive Aspergillus infection.
- This is mainly relevant in hospital and intensive-care settings.
- It is not a usual consequence of routine seasonal flu, COVID-19 or other viral infections managed at home.
- Doctors consider Aspergillus when someone with severe viral pneumonia is not improving as expected or develops new lung changes.
- Chronic aspergillosis does not mean that a person will automatically develop invasive infection when they catch a virus.
Why can severe viral illness increase risk?
A severe respiratory virus can damage the lining of the airways and lungs, disrupt normal immune defences and lead to critical illness. In that setting, Aspergillus may sometimes cause a serious lung infection.
This is different from chronic forms of aspergillosis. It develops rapidly during severe acute illness and requires hospital diagnosis and treatment.
Influenza-associated pulmonary aspergillosis
Influenza-associated pulmonary aspergillosis is most often considered in people admitted to hospital with severe flu, especially if they need intensive-care treatment. Doctors may investigate when fever, breathing problems or scan changes persist or worsen despite treatment.
It is not a reason for most people with flu to assume they have a fungal infection.
COVID-19-associated pulmonary aspergillosis
COVID-19-associated pulmonary aspergillosis can occur in some people with severe COVID-19, particularly those who are critically unwell and need intensive-care support. The illness itself, treatment used in severe disease and other health problems can all affect risk.
Most people with COVID-19, including those recovering at home, do not develop Aspergillus infection.
Other viral infections
Other viruses can sometimes cause severe viral pneumonia. When a person is critically unwell, has major immune suppression or has significant lung damage, hospital teams may consider a range of possible infections, including Aspergillus.
The important point is the severity of illness and the person’s overall risks — not simply the name of the virus.
Who may be at higher risk?
Doctors are particularly alert when severe viral pneumonia occurs alongside factors such as:
- Intensive-care admission or severe respiratory failure
- Major immune suppression
- Intensive chemotherapy, transplant treatment or prolonged neutropenia
- High-dose steroids or other strong immune-suppressing medicines
- Substantial underlying lung disease
How is it diagnosed?
No single test confirms every case. Hospital teams combine symptoms, CT scans, respiratory samples and laboratory tests such as fungal culture, PCR or galactomannan testing.
Finding Aspergillus in a sample does not automatically mean invasive infection. Results need to be interpreted alongside the person’s scans, symptoms and level of immune suppression.
What does this mean for people with chronic aspergillosis?
People with CPA, ABPA, Aspergillus bronchitis, SAFS or an aspergilloma should take viral infections seriously in the same way as other people with long-term lung conditions. However, these chronic conditions do not mean that Aspergillus infection will automatically become invasive after flu or COVID-19.
Vaccination, prompt medical advice when symptoms are severe or worsening, and following your usual respiratory care plan remain the most useful precautions.
Related information
Visit the Invasive & Acute Aspergillosis Hub
Learn about invasive aspergillosis
Visit the Vaccines Hub
References
- Koehler P, et al. Defining and managing COVID-19-associated pulmonary aspergillosis. Lancet Infectious Diseases. 2021;21:e149–e162.
- Feys S, et al. Influenza-associated and COVID-19-associated pulmonary aspergillosis. Lancet Respiratory Medicine. 2024.

Aspergillus Infections of the Ear, Eye and Nails
Aspergillus can occasionally cause local infections of the ear, eye or nails. These are different from lung aspergillosis and usually do not mean that an existing lung condition is spreading through the body.
They can still need the right specialist assessment. The key is to recognise when symptoms need prompt attention, especially if the eye is involved.
Key points
- Ear, eye and nail infections are usually local conditions.
- They are not usually caused by CPA, ABPA or another chronic lung form of aspergillosis spreading through the body.
- Many other conditions can cause similar symptoms, so a correct diagnosis matters.
- Eye symptoms need urgent assessment because infections of the eye can threaten sight.
- Ear and nail infections are often treatable but may need a sample or specialist review.
How common are these conditions?
Ear, eye and nail symptoms are far more often caused by something other than Aspergillus.
- Ear symptoms are commonly due to earwax, eczema, irritation or bacterial outer-ear infection. Fungal ear infection is less common, and Aspergillus is only one possible cause.
- Red, painful or irritated eyes are much more often caused by dryness, allergy, viral or bacterial infection, or another eye condition. Fungal eye infection is uncommon, but it needs urgent assessment because it can be serious.
- Nail changes are commonly caused by injury, skin conditions or other fungi. Even when a nail infection is fungal, Aspergillus is not the usual cause.
So these conditions are worth recognising, but they are not something most people with aspergillosis should expect to develop. A clinician may need to examine the area or take a sample before confirming the cause.
Aspergillus infection of the ear
A fungal infection of the outer ear canal is called otomycosis. Several fungi can cause it, including Aspergillus and Candida. It is a local infection of the ear canal, not a lung infection.
Possible symptoms include:
- Itching or irritation in the ear
- Earache or discomfort
- A blocked feeling or reduced hearing
- Discharge or debris from the ear
- Flaking skin around the ear canal
Otomycosis can be more likely after repeated water exposure, local irritation, ear eczema, use of cotton buds or previous ear treatment. It can also occur in people with diabetes or reduced immune defences.
A GP, pharmacist or ENT clinician may examine the ear. Treatment commonly involves careful removal of debris and local treatment chosen for the likely cause. Avoid putting cotton buds, hairpins or unprescribed drops into the ear canal, as this can worsen irritation or push material deeper inside.
Aspergillus infection of the eye
Fungal infection of the eye is uncommon, but it is important because it can damage sight if treatment is delayed. Infection of the cornea, the clear surface at the front of the eye, is called fungal keratitis.
Aspergillus is one possible cause. Infection may be more likely after an eye injury, particularly one involving soil, plant material or dust, after eye surgery, or in people with certain eye conditions or major immune suppression.
Seek urgent eye-care advice if you have:
- A painful red eye
- New sensitivity to light
- Blurred or reduced vision
- A white or cloudy spot on the surface of the eye
- Eye pain or redness after an injury
Do not try to self-treat a painful or red eye with leftover drops. An optometrist, eye casualty service or ophthalmology team can assess the cause and arrange specialist treatment if needed.
Aspergillus infection of the nails
Aspergillus can occasionally cause a fungal nail infection. However, many nail changes are caused by other fungi, psoriasis, eczema, injury, circulation problems or ordinary ageing.
Nails may become thicker, discoloured, brittle, crumbly or partly detached from the nail bed. These changes do not show which organism is responsible.
A clinician may take a clipping or scraping before recommending treatment. This helps avoid unnecessary medicines and allows treatment to be matched to the likely cause. Nail infections often take time to improve because healthy nail has to grow back.
Does this mean my lung aspergillosis is spreading?
Usually, no. A local ear, eye or nail infection is not normally evidence that CPA, ABPA, Aspergillus bronchitis or an aspergilloma is spreading through the body.
Tell your treating team about any new diagnosis, particularly if you are taking antifungal medicines or immune-suppressing treatment, so they can consider possible interactions and your wider health. But a new local problem is usually assessed through the relevant GP, ENT, eye or dermatology service.
When should I seek advice?
Arrange a routine appointment for persistent ear symptoms, changing nails or recurrent local infections. Seek urgent eye-care advice for eye pain, redness, light sensitivity or any change in vision.
If you are severely immunocompromised, have recently had an organ or stem-cell transplant, or are receiving intensive cancer treatment, contact your specialist team promptly about new or worsening symptoms.
Related information
Visit the Invasive & Acute Aspergillosis Hub
Learn about invasive aspergillosis
Rare Aspergillus infections outside the lungs
References
- Patterson TF, Thompson GR, Denning DW, et al. Practice guidelines for the diagnosis and management of aspergillosis. Clinical Infectious Diseases. 2016;63:e1–e60.
- Bongomin F, et al. A review of onychomycosis due to Aspergillus species. Mycopathologia. 2018;183:485–493.

The Power of Keeping a Health Diary When You Have Aspergillosis

Last reviewed: September 2026
Audience: People living with aspergillosis, families and carers
Key points
- A health diary can help you understand symptoms, triggers and changes over time.
- It can be especially useful if you experience fatigue, brain fog or memory problems.
- It can make clinic appointments more focused and productive.
- A diary may show progress that is hard to notice day to day.
- The best diary is simple, quick and realistic to keep using.
Contents
- Why keep a health diary?
- How it can help with aspergillosis
- Brain fog and memory
- Spotting patterns and triggers
- Using your diary at appointments
- The psychological benefit
- Simple diary template
- Common questions
- When to seek medical advice
Why keep a health diary?
Living with aspergillosis often means symptoms change from day to day. Some days may be manageable. Others may involve more coughing, breathlessness, fatigue, sinus symptoms, poor sleep or medication side effects.
Because these changes can happen gradually, it can be difficult to remember exactly when symptoms started, whether they are getting better or worse, or what might have triggered them.
A health diary gives you a simple record of what is happening over time. It can help you, your family and your healthcare team see patterns that may not be obvious from memory alone.
How a diary can help with aspergillosis
People with aspergillosis may find it useful to record:
- Cough
- Breathlessness
- Fatigue
- Sputum or phlegm
- Wheeze
- Sinus symptoms
- Sleep quality
- Exercise or walking distance
- Mood and wellbeing
- Medication changes
- Possible side effects
You may also want to note possible triggers, such as damp or mould exposure, pollen, dusty environments, changes in weather, respiratory infections, stress, travel or changes in medication.
Brain fog and memory
Many people with long-term lung conditions describe episodes of brain fog. This may feel like forgetfulness, poor concentration, difficulty finding words, feeling mentally slower than usual, or feeling as though your head is “empty”.
Brain fog can have many possible causes, including fatigue, poor sleep, infection, inflammation, stress, anxiety, pain, medication side effects, low oxygen levels or other health problems.
A diary acts as an external memory. Instead of trying to remember when something changed, you can look back and see what was happening at the time.
Spotting patterns and triggers
| What you record | What it may help show |
|---|---|
| Symptoms | Whether cough, breathlessness or fatigue are improving or worsening |
| Sleep | Whether poor sleep is linked to worse symptoms |
| Exercise | What level of activity is manageable |
| Weather | Whether heat, humidity, cold air or storms affect symptoms |
| Environment | Possible links with damp, mould, dust or pollen |
| Medication | Possible benefits, side effects or changes during dose reduction |
| Infections | Early warning signs or repeated patterns |
Using your diary at appointments
Healthcare professionals may ask questions such as:
- When did your symptoms start?
- Are they getting better or worse?
- Have you noticed any triggers?
- Have you changed any medication recently?
- How far can you walk now compared with before?
- Have you had any infections or courses of antibiotics?
These questions are not always easy to answer from memory, especially when you are tired or anxious. A diary can help you give clearer, more accurate information.
You may find it useful to bring a short summary to your appointment, such as:
- Three things that have improved
- Three things that have worsened
- Any medication changes
- Your main questions for the appointment
For family members and carers: If the person you support would find it helpful, you can help them keep the diary or prepare a short summary before an appointment. Agree together what they want recorded and what they would like you to raise with the healthcare team. The diary should support the person's involvement in their care rather than become something managed for them.
Sometimes the diary tells a different story
When you have had a difficult few days, it can feel as though nothing is improving. A diary may show that the wider picture is more encouraging.
For example, you may feel:
“Nothing has changed.”
But your diary may show:
- You are walking further than three months ago
- You are sleeping better
- You have had fewer chest infections
- You are coughing less at night
- You are doing more social activities
Equally, a diary can show gradual deterioration that might otherwise be missed. Both types of information can be useful.
The psychological benefit
Chronic illness can feel unpredictable. A diary can help restore a sense of control by changing the question from:
“Why do I feel awful?”
to:
“What changed recently?”
This can reduce uncertainty and help you feel more involved in your care.
A diary can also become a record of resilience. It may include difficult days, but it can also capture walks completed, holidays taken, family events attended, personal goals reached and challenges overcome.
Keep it simple
Many people stop keeping a diary because they try to record too much. A simple diary is usually more useful than a complicated one.
A daily entry might take less than two minutes and include:
- Symptoms, scored from 0 to 10
- Energy level, scored from 0 to 10
- Sleep quality
- Exercise or activity
- Medication changes
- Anything unusual
Consistency matters more than detail.
Paper, phone or app?
There is no single correct way to keep a diary. You could use:
- A notebook
- A printed diary sheet
- A phone notes app
- A calendar
- Voice notes
- A spreadsheet
- A symptom tracking app
- A fitness tracker or smartwatch
The best diary is the one you will actually use.
Simple diary template
Daily health diary
Date: __________________________
Symptoms, 0–10
Cough: ______
Breathlessness: ______
Fatigue: ______
Sinus symptoms: ______
Overall wellbeing: ______
Sleep
Hours slept: ______
Sleep quality, 0–10: ______
Activity
Exercise or activity today:
__________________________________________________
Medication
Any medication changes or side effects?
__________________________________________________
Notes
Anything unusual today?
__________________________________________________
__________________________________________________
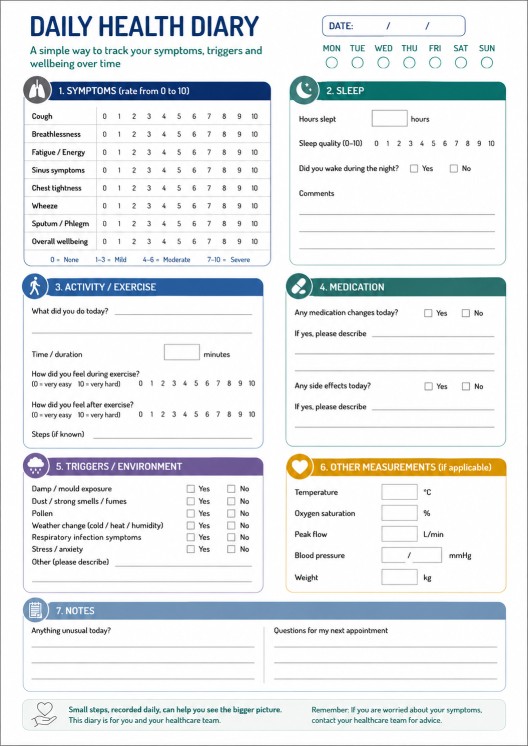
Daily Diary - PDF downloadable
Common questions
Do I need to write every day?
No. Some people write daily. Others only record changes, flare-ups, medication changes or important events.
What if I forget for a few days?
That is very common. Simply restart when you remember. A diary does not have to be perfect to be useful.
Should I record test results?
You can if you find it helpful. Some people record blood results, oxygen saturations, lung function, weight, clinic letters or medication levels. Do not worry if this feels too much. A simple symptom diary is still useful.
Can a diary replace medical advice?
No. A diary is a tool to support conversations with your healthcare team. It should not be used to diagnose or treat symptoms without medical advice.
When to seek medical advice
Seek medical advice promptly if you experience:
- Sudden or significant worsening of breathlessness
- Coughing up large amounts of blood
- Persistent fever
- Severe chest pain
- New confusion or rapidly worsening brain fog
- Weakness, speech problems, facial drooping or visual changes
- Symptoms that are worsening quickly or feel unusual for you
If you are unsure, contact your healthcare team, NHS 111, your GP, or emergency services depending on severity.