

Living with Aspergillosis: Understanding the Brain–Lung Connection
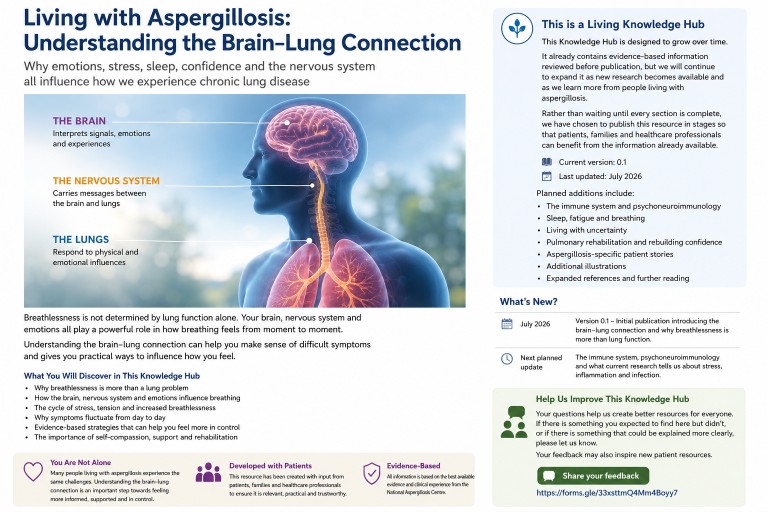
Why emotions, stress, sleep, confidence and the nervous system all influence how we experience chronic lung disease
Aspergillosis Living Knowledge Hub | Built with patients | Living document
This is a Living Knowledge Hub
Unlike a traditional article, this Knowledge Hub is designed to evolve.
As new scientific research becomes available, and as people living with aspergillosis ask new questions, we will continue to expand and improve this resource.
The current version already contains evidence-based information that has been reviewed before publication, but it is only the beginning.
This approach allows us to share useful information now, rather than waiting until every section is complete, while continuing to improve the resource over time.
- Current version: 0.2
- Last updated: August 2026
- Status: Living Knowledge Hub
- Reading time: approximately 28 minutes
- Who is this for? People living with aspergillosis, families, carers and healthcare professionals
- Review policy: This Knowledge Hub is reviewed whenever important new evidence becomes available and at least annually to ensure it remains accurate and up to date.
Planned additions
- Living with uncertainty and recognising meaningful change
- More detail on pulmonary rehabilitation and rebuilding confidence
- Further patient experiences and questions
- Additional illustrations and diagrams
Contents
- Before you begin: you are not imagining it
- Why we wrote this guide
- Why does my breathing feel worse when my scan has not changed?
- Why does the brain matter if my lungs are the problem?
- Can emotions really change my breathing?
- How do the brain, stress system and immune system communicate?
- Can stress make aspergillosis worse?
- Why do sleep and breathing affect each other?
- Where do medicines fit into the brain–lung connection?
- When coughing becomes socially difficult
- What if I also have bronchiectasis, asthma or sinusitis?
- What can help?
- What’s new?
- Help us improve this Knowledge Hub
Before you begin…
If you have arrived here because someone suggested that stress or anxiety might be affecting your breathing, this page is for you.
If you have arrived here because you are wondering why some days are so much harder than others, this page is for you.
If you have ever worried that family members, friends or even healthcare professionals thought your symptoms were “all in your head”, this page is for you too.
And if you are a family member or healthcare professional trying to understand what it is really like to live with aspergillosis, we hope this guide helps explain an aspect of chronic lung disease that is rarely discussed in detail.
The most important message comes first.
Your illness is real.
Your symptoms are real.
Modern respiratory medicine recognises that the brain, lungs, nervous system and immune system constantly work together. Understanding that relationship does not make your illness any less real. It helps explain why living with chronic lung disease can sometimes be so challenging.
Why we wrote this guide
Over many years at the National Aspergillosis Centre, we have listened to many people living with aspergillosis.
Again and again, we hear similar questions.
“Why do I feel much worse today when my scan hasn’t changed?”
“Why does poor sleep affect my breathing so much?”
“Can stress make my symptoms worse?”
“If my emotions affect my breathing, does that mean my illness isn’t real?”
These are important questions. Unfortunately, they can be difficult to answer fully during a busy clinic appointment.
This guide has been written to provide the explanation many people tell us they never had.
It brings together modern respiratory medicine, neuroscience, immunology, pulmonary rehabilitation and the lived experience of people with aspergillosis.
Our aim is not simply to explain the science. Our aim is to help you understand your own experience.
A false choice
Many people living with chronic illness feel they have been offered two very different explanations for their symptoms.
Either the symptoms are caused by the lungs, or the symptoms are caused by anxiety.
Modern medicine increasingly recognises that this is a false choice.
The lungs are real. The brain is real. The nervous system is real. The immune system is real. Hormones are real.
Every one of these systems communicates continuously with the others. When we understand that partnership, many experiences that once seemed confusing begin to make sense.
More than just the lungs
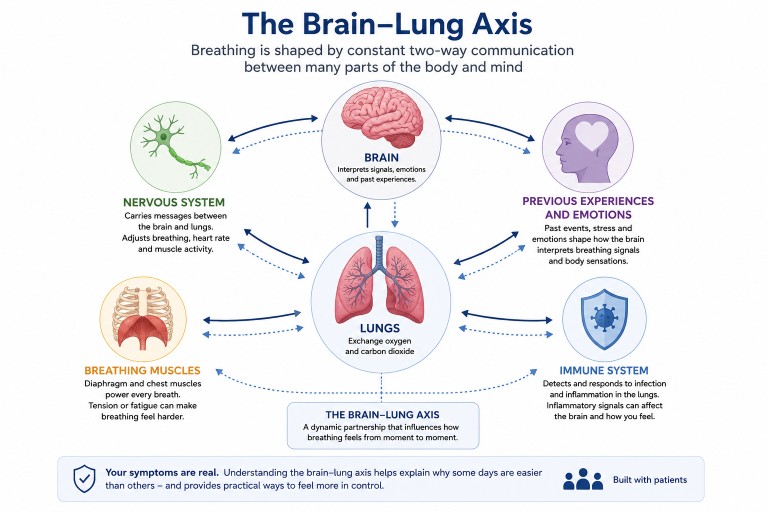
Most of us think breathing happens entirely inside the lungs. In reality, every breath depends on an extraordinary partnership between many different parts of the body.
| Body system | Its role in breathing |
|---|---|
| The lungs | Exchange oxygen and carbon dioxide. |
| The brain | Interprets breathing signals and decides how much air the body needs. |
| The nervous system | Adjusts breathing, heart rate and muscle activity. |
| The breathing muscles | Power every breath you take. |
| The immune system | Responds to infection and inflammation in the lungs. |
| Your previous experiences | Help the brain judge whether breathing feels safe or threatening. |
Scientists often describe this constant communication as the brain–lung axis.
Understanding how this partnership works has transformed the way respiratory specialists think about chronic breathlessness.
What you will learn
By the end of this guide you will understand:
- why scans and lung function tests do not always match how you feel
- why frightening experiences can change the way breathing feels
- why sleep, fatigue and emotions influence symptoms
- what scientists know about stress and the immune system
- why pulmonary rehabilitation works
- how confidence can be rebuilt after serious illness
- what is known, and what is still uncertain, about these important questions.
If you remember only one thing from this opening section, remember this:
Your illness is real. Your symptoms are real. The science that explains the connection between the brain and lungs is real too.
Why Does My Breathing Feel Worse When My Scan Hasn’t Changed?
This is probably one of the most common questions asked by people living with chronic lung disease.
“My doctor says my CT scan looks stable, so why do I feel so much worse?”
It is an excellent question. It is also one that causes enormous frustration.
Many people begin wondering whether they are imagining their symptoms or whether something has been missed.
Fortunately, modern respiratory medicine has a much better explanation.
The first thing to understand
A CT scan is an extraordinarily useful investigation. It allows doctors to see inflammation, cavities, bronchiectasis, scarring and many other important changes inside the lungs.
But a scan has one important limitation.
It shows what your lungs look like.
It cannot show what breathing feels like.
Those are two different things.
Structure versus function
A useful way to think about this is to separate structure from function.
| Structure | Function and lived experience |
|---|---|
| CT scans | Breathing comfort and effort |
| X-rays | Exercise tolerance |
| Blood tests | Energy and fatigue |
| Lung function tests | Quality of life and confidence |
Your medical team needs both kinds of information. One does not replace the other.
Breathlessness is an experience
The American Thoracic Society defines breathlessness, also called dyspnoea, as:
“A subjective experience of breathing discomfort that consists of qualitatively distinct sensations that vary in intensity.”
That definition is important. It tells us that breathlessness is something that is experienced.
The lungs send information. The brain turns that information into the experience of breathing.
An orchestra, not a solo instrument
Imagine listening to an orchestra. You do not hear only the violins. You hear the combined sound of strings, woodwind, brass and percussion.
Breathing works in much the same way. What you experience is produced by many different systems working together.
| System | Contribution |
|---|---|
| Lungs | Move oxygen and carbon dioxide. |
| Heart | Delivers oxygen. |
| Breathing muscles | Generate each breath. |
| Brain | Interprets signals. |
| Nervous system | Adjusts breathing. |
| Sleep | Influences fatigue and resilience. |
| Confidence | Changes how safe breathing feels. |
| Previous experiences | Influence future breathing responses. |
No single instrument produces the whole performance.
What your scan cannot see
Your CT scan cannot show:
- how well you slept
- whether your breathing muscles are tired
- whether you recently recovered from a viral infection
- whether you feel anxious about another haemoptysis
- whether today’s humidity is making your chest feel tight
- whether your body is still recovering from yesterday’s activity
- how much mental effort breathing requires today.
All of these may influence how breathing feels. None of them mean your illness is imaginary.
Research Spotlight
Why the modern definition of breathlessness matters
Older medical thinking often treated breathlessness as a simple consequence of lung damage.
Research over recent decades has shown that the experience of breathlessness depends upon interactions between the lungs, brain, nervous system and many other factors.
This is why modern respiratory medicine increasingly measures quality of life alongside scans and lung function tests.
Why this matters: it validates what patients have always known: how they feel cannot always be predicted by test results alone.
Why this matters if you have aspergillosis
If your scan has not changed but your breathing feels worse, this does not automatically mean:
- the disease has suddenly progressed
- the scan is wrong
- your symptoms are “all in your head”.
It means breathing is influenced by many different parts of the body working together.
Understanding those interactions is one of the biggest advances in modern respiratory medicine.
Why Does the Brain Matter If My Lungs Are the Problem?
This question worries many people.
“If my doctor starts talking about my brain, are they saying my illness isn’t real?”
The answer is simple. No.
Talking about the brain is not changing the diagnosis. It is explaining how breathing works.
Your lungs cannot create the sensation of breathlessness on their own, just as your ears cannot create music on their own, or your eyes cannot create vision on their own.
Every one of these experiences depends on the brain interpreting information coming from the body. Breathing is no different.
Your brain is your body’s prediction machine
Most of us imagine the brain as a computer that simply receives information. Modern neuroscience paints a much more interesting picture.
The brain is constantly trying to predict what is about to happen.
Every second it asks questions such as:
- Am I safe?
- Am I getting enough oxygen?
- Should I breathe faster?
- How hard are my breathing muscles working?
- Does this feel familiar?
It compares what it expects to happen with what is actually happening.
If everything matches, breathing usually fades into the background. If something unexpected happens, breathing suddenly becomes the centre of attention.
This is one reason healthy people rarely notice their breathing, while people living with chronic lung disease may think about it many times each day.
The smoke alarm inside your brain
A smoke alarm has one job: to detect danger. It would rather ring unnecessarily than miss a real fire.
Your brain works in much the same way.
If you have experienced:
- a severe asthma attack
- haemoptysis
- being unable to catch your breath
- an emergency admission to hospital
- months of unexplained symptoms before diagnosis
your brain learns something very important.
“Breathing can sometimes become dangerous.”
Once that lesson has been learned, your brain naturally pays much closer attention to breathing than it did before.
This is not a fault. It is exactly what evolution intended. Your brain is trying to protect you.
Patient Perspective
“After coughing up blood I became frightened every time I coughed.
I knew the bleeding had stopped, but every cough made me wonder whether it was happening again.
Learning that my brain was trying to protect me, not trick me, changed the way I understood my recovery.”
The Brain–Lung Axis
Scientists describe the close communication between the brain and lungs as the brain–lung axis.
This communication works in both directions.
| The lungs tell the brain… | The brain tells the lungs… |
|---|---|
| How much oxygen is available. | How fast to breathe. |
| How much carbon dioxide is present. | How deeply to breathe. |
| Whether the airways are irritated. | When to cough. |
| How hard the breathing muscles are working. | How to respond to exercise. |
Every breath is the result of this continuous conversation.
Why this matters if you have aspergillosis
If you understand that breathing is created by a partnership between the lungs and brain, several confusing experiences suddenly make much more sense.
- Why one day can feel much harder than another.
- Why sleep affects breathing.
- Why fatigue affects breathing.
- Why confidence affects breathing.
- Why pulmonary rehabilitation improves symptoms even when scans remain unchanged.
- Why frightening respiratory events can continue to affect confidence long after the lungs have recovered.
None of these observations suggest your illness is psychological.
They demonstrate how remarkably sophisticated the breathing system really is.
Research Spotlight
Brain imaging studies have shown that breathlessness activates areas of the brain involved in attention, emotion and decision-making, as well as areas involved in sensory processing.
This reinforces an important message:
Breathlessness is not simply a signal from the lungs. It is a whole-body experience.
Can Emotions Really Change My Breathing?
Many people living with aspergillosis are reluctant to ask this question.
Some worry that even mentioning stress or emotions will mean their symptoms are no longer taken seriously. Others have experienced exactly that in the past.
Modern respiratory medicine takes a very different view.
It recognises two equally important facts.
- Your lung disease is real.
- Your emotional state can influence how that disease is experienced.
These statements are not contradictory. They describe how the human body normally works.
Every emotion has a physical effect
Think about the last time you were startled. Before you had time to think, your body had already responded.
- Your heart rate increased.
- Your breathing became faster.
- Your muscles tightened.
- Your mouth became dry.
- Your attention narrowed onto the potential danger.
You did not choose any of those reactions. They happened automatically.
This is because emotions are not separate from the body. They are produced by the body and immediately affect the body’s physiology.
Breathing is especially sensitive
Unlike many other organs, the breathing system has to respond continuously to both physical demands and emotional demands.
| Situation | What happens? |
|---|---|
| Walking upstairs | Your breathing increases because your muscles need more oxygen. |
| Receiving frightening news | Your breathing may also increase, even though your muscles are resting. |
| Laughing | Your breathing pattern changes completely. |
| Crying | Your breathing becomes irregular and deeper. |
| Feeling calm and relaxed | Your breathing usually slows and becomes more efficient. |
These changes happen in everyone.
People with chronic lung disease often notice them more because their breathing system is already working harder.
Why frightening experiences matter
Imagine two people climbing exactly the same flight of stairs.
One has never experienced serious breathing problems. The other has previously been admitted to hospital with severe breathlessness.
Their lungs may be working equally hard. But their brains interpret those signals differently.
The first person thinks:
“I’m out of breath because I climbed the stairs.”
The second person may immediately wonder:
“Is something going wrong again?”
Neither response is irrational. They reflect different life experiences.
This is one reason why previous severe respiratory events can continue to influence confidence long after recovery.
Patient Perspective
“I realised I wasn’t frightened of exercise.
I was frightened of becoming breathless because, in the past, breathlessness had meant I was seriously ill.”
The vicious circle of fear
Fear itself does not damage the lungs. However, fear can unintentionally make breathing feel more difficult.
Breathlessness
       ↓
Concern
       ↓
Breathing becomes faster
       ↓
Chest muscles tighten
       ↓
Breathing feels harder
       ↓
More concern
This is not imaginary. Every stage involves genuine physical changes.
The encouraging news is that this cycle can also be interrupted.
Understanding
       ↓
Greater confidence
       ↓
Calmer breathing
       ↓
More efficient breathing
       ↓
Activity feels easier
       ↓
Confidence grows
This does not remove aspergillosis. It changes how effectively the whole breathing system works together.
Research Spotlight
Why pulmonary rehabilitation improves confidence
Research consistently shows that pulmonary rehabilitation improves quality of life, exercise capacity and confidence, even when lung function changes only modestly.
Patients often describe feeling more in control of their breathing.
This improvement reflects better physical conditioning, improved breathing efficiency, increased confidence and a better understanding of symptoms.
These benefits are recognised internationally and form an important part of managing many chronic respiratory diseases.
Why this matters if you have aspergillosis
You are not expected to ignore your emotions.
You are not expected to “stay positive” all the time.
You are not expected to pretend your illness is less serious than it is.
Instead, understanding how emotions influence breathing gives you another tool.
It helps explain why:
- some days feel harder than others
- confidence matters
- breathing techniques can help
- pulmonary rehabilitation works
- being listened to is part of good medical care
Knowledge does not remove the disease.
But it can remove unnecessary fear and replace it with understanding.
Emotions do not make aspergillosis imaginary.
They are one of the many biological systems that influence how living with aspergillosis feels from day to day.
How Do the Brain, Stress System and Immune System Communicate?
The brain and immune system are not separate departments. They exchange information continuously through nerves, hormones and chemical messengers.
The scientific field that studies these connections is called psychoneuroimmunology:
- psycho refers to thoughts, emotions and behaviour
- neuro refers to the brain and nervous system
- immunology refers to the immune system
The name may sound as though it is about psychology alone. It is not. It describes measurable biological communication between the nervous, hormonal and immune systems.
What happens during a stress response?
When the brain detects a possible threat, it activates two closely connected systems.
| System | What it does |
|---|---|
| The sympathetic nervous system | Acts rapidly. Adrenaline and related signals can increase heart rate, blood pressure, alertness and breathing. |
| The hypothalamic–pituitary–adrenal axis | Produces a slower hormonal response involving cortisol, which helps regulate energy use, inflammation and immune activity. |
This response is useful when danger is brief. It prepares the body to act and then, normally, settles again.
Long-lasting illness can be different. Symptoms, uncertainty, poor sleep, repeated hospital visits and frightening events may keep the body’s alarm systems more active than usual. Researchers call the accumulated strain of repeated adaptation allostatic load.
Does stress simply weaken the immune system?
No. That common phrase is too simple.
Stress signals can increase some immune responses and reduce or redirect others. The effect depends on how intense and prolonged the stress is, what else is happening in the body, which part of the immune system is measured and the individual person.
Human studies have shown that sustained psychological stress can be associated with greater susceptibility to some viral respiratory infections. Sleep disruption can also alter inflammatory and immune signalling. However, these findings cannot simply be transferred to every disease or every patient.
The essential distinction
Stress does not create Aspergillus, and there is no good evidence that stress alone causes aspergillosis.
Aspergillosis develops through an interaction between fungal exposure, the lungs, the immune system and individual susceptibility. Stress and sleep may influence parts of that wider system, but they are not substitutes for diagnosis, antifungal treatment, asthma treatment or specialist care.
Why this matters: the brain–immune connection is real, but it must never be used to blame someone for becoming ill or for failing to recover.
Can Stress Make Aspergillosis Worse?
This question needs a careful answer.
There is currently not enough direct research to say that psychological stress makes the fungus grow, causes aspergillosis to progress or produces a relapse. We should not claim more than the evidence shows.
Stress can nevertheless affect the experience and management of illness through several genuine biological and practical routes:
- breathing may become faster or less regular
- heart rate and blood pressure may rise temporarily
- chest and shoulder muscles may tighten
- sleep may become more fragmented
- fatigue and pain may become harder to tolerate
- attention may become fixed on breathing or coughing
- activity may be avoided through fear of breathlessness
- complex treatments and airway-clearance routines may become harder to manage
These effects can make a difficult day feel substantially worse even when the underlying lung disease has not suddenly changed.
The reverse is also important. Worsening respiratory symptoms can create stress. The relationship therefore runs in both directions:
Symptoms can increase stress, and stress can amplify the experience and consequences of symptoms.
Do not assume that a change is “only stress”
A new or persistent deterioration still deserves appropriate medical assessment. Stress may be one influence, but it must not be used to dismiss infection, an asthma flare, mucus plugging, medicine side effects, low oxygen levels or progression of lung disease.
Why Do Sleep and Breathing Affect Each Other?
One reader told us that understanding the importance of sleep was especially helpful. Sleep deserves its own section because the relationship again works in both directions.
Lung symptoms can disturb sleep
Cough, sputum, wheeze, breathlessness, reflux, pain, medicines and worry can all interrupt sleep. People may also wake to clear mucus, use an inhaler or change position.
Research in adults with stable bronchiectasis found sleep disturbance to be common and associated with poorer health-related quality of life. That does not prove that bronchiectasis is the only cause of poor sleep, but it confirms that the problem deserves attention rather than being accepted as an inevitable inconvenience.
Poor sleep can make the next day harder
After disrupted sleep:
- physical and mental energy are reduced
- concentration and memory may be poorer
- the brain may have less capacity to filter or tolerate uncomfortable sensations
- breathlessness and coughing may feel more intrusive
- emotional resilience may be lower
- motivation for exercise, airway clearance and treatment routines may fall
This can produce another self-reinforcing loop:
Night-time symptoms → broken sleep → fatigue and greater symptom burden → reduced activity or coping capacity → a more difficult night.
Could it be a sleep disorder?
Not every sleep problem is caused by aspergillosis. Loud snoring, witnessed pauses in breathing, gasping or choking during sleep, morning headaches and marked daytime sleepiness can be features of obstructive sleep apnoea. These symptoms should be discussed with a GP or respiratory team because sleep apnoea can be assessed and treated.
Sleep is not a cure for aspergillosis. Improving a treatable sleep problem may, however, improve energy, concentration, mood and the ability to manage respiratory illness.
Where Do Medicines Fit into the Brain–Lung Connection?
A reader asked about “the effect of pharmaceuticals within the loop”. This is an important question because medicines can influence several parts of the system at once.
| Medicine or treatment | How it may affect the wider system |
|---|---|
| Antifungal treatment | Targets the fungal infection or fungal burden. Effective treatment may reduce inflammation and respiratory symptoms, while side effects or interactions can affect energy, sleep or general wellbeing. |
| Inhaled bronchodilators | Can make breathing easier by opening the airways. Some people temporarily notice shaking, palpitations or a faster heartbeat, which can themselves feel alarming. |
| Corticosteroids | Can reduce allergic and airway inflammation, particularly in conditions such as ABPA and asthma. Systemic steroids can also affect sleep, mood, appetite, blood pressure, blood glucose and adrenal function. |
| Mucus and airway-clearance treatments | May loosen or mobilise secretions. This can temporarily provoke more coughing even when the treatment is doing something useful. |
| Sedating medicines, alcohol and some pain medicines | May alter alertness, sleep quality or breathing. Their effects vary and can be particularly important when several medicines are taken together. |
Azole antifungals can interact with many other medicines, sometimes increasing or decreasing drug levels. A medication review by a pharmacist or specialist team is therefore part of good aspergillosis care.
Do not stop or change prescribed treatment because of this section. If a medicine appears to affect sleep, mood, heart rate, blood pressure or breathing, discuss the timing, dose, interactions and possible alternatives with the prescribing team or a pharmacist.
What If I Also Have Bronchiectasis, Asthma or Sinusitis?
Another reader asked us to recognise the respiratory conditions that often exist alongside aspergillosis. The brain does not receive neatly labelled messages from one diagnosis at a time. It receives a combined stream of information from the whole respiratory system.
| Condition or problem | Signals it may add |
|---|---|
| Aspergillosis | Inflammation, infection, tissue damage, cough, fatigue and uncertainty about changing symptoms. |
| Bronchiectasis | Mucus retention, airway clearance, recurrent infections and unpredictable coughing. |
| Asthma | Variable airway narrowing, wheeze, chest tightness and sometimes sudden episodes of breathlessness. |
| Chronic sinusitis or nasal disease | Nasal obstruction, post-nasal drainage, facial discomfort, disturbed sleep and upper-airway irritation. |
| Reflux, pain or deconditioning | Additional cough triggers, restricted movement and increased effort during activity. |
This helps explain why treating one part of the problem may bring a real improvement without making every symptom disappear. It also explains why coordinated care and a clear treatment plan matter when several diagnoses overlap.
What Can Help?
Understanding the brain–lung connection should lead to more options, not fewer. It adds supportive treatments to appropriate medical care; it does not replace that care.
1. Learn your own patterns
A short symptom diary can reveal links between sleep, activity, medicines, airway clearance, stressful events and breathing. Look for patterns rather than blaming yourself for individual difficult days.
2. Treat the lungs properly
Antifungals, asthma treatment, infection management, airway clearance and monitoring remain central where clinically indicated. A brain–lung explanation must never become a reason to undertreat physical disease.
3. Rebuild confidence gradually
Pulmonary rehabilitation and appropriately paced activity can help the brain relearn that breathlessness during safe activity does not always signal immediate danger. Progress may be slow and uneven.
4. Use breathing control appropriately
Techniques taught by a respiratory physiotherapist can help some people recover from an episode of difficult breathing or manage the urge to breathe rapidly. Airway clearance and breathing control have different purposes, so personalised instruction is valuable.
5. Investigate persistent sleep problems
Do not assume that severe daytime sleepiness, repeated waking, loud snoring or night-time breathing difficulty is simply part of aspergillosis. Discuss it with a healthcare professional.
6. Review medicines
Ask whether the timing, dose, side effects or interactions of medicines could be affecting sleep, mood, energy, heart rate or breathing. This is particularly important when azole antifungals, steroids or several long-term medicines are used together.
7. Create a plan for genuine deterioration
Knowing what is normal for you—and when to seek help—can reduce uncertainty. Ask your clinical team what changes should trigger routine advice, urgent assessment or emergency help.
Seek urgent medical help
Do not try to manage severe or rapidly worsening breathlessness as anxiety alone. Seek urgent help for symptoms such as severe difficulty breathing, blue or grey lips or skin, confusion, chest pain, fainting, a major fall in oxygen levels, or significant coughing of blood. Follow the emergency advice appropriate to your country.
What the evidence can—and cannot—tell us
| Evidence position | What we can reasonably say |
|---|---|
| Well established | The brain constructs the experience of breathlessness from signals coming from the lungs and the rest of the body. Emotions, attention, previous experiences and physical physiology all contribute. |
| Supported across chronic respiratory disease | Poor sleep, anxiety, disease-specific fears and social restriction are common and can worsen quality of life. Pulmonary rehabilitation can improve exercise capacity, confidence and symptom management. |
| Biologically established but individually complex | The nervous, hormonal and immune systems communicate. Stress and sleep can alter immune and inflammatory signals, but the direction and clinical importance vary. |
| Not yet established | That psychological stress directly causes aspergillosis, makes Aspergillus grow or independently causes a relapse. |
If you remember only one message from this update, remember this:
Good care does not ask whether symptoms come from the lungs or the brain. It asks how the lungs, brain, nervous system, immune system, sleep, medicines and lived experience are interacting—and what can safely be improved.
What’s New?
This Knowledge Hub is updated as new evidence becomes available and in response to questions from readers.
Version 0.2 – August 2026
- Added the immune system and psychoneuroimmunology.
- Explained stress hormones, inflammation and the limits of current evidence.
- Added a detailed section on sleep and breathing.
- Explained how medicines can affect different parts of the brain–lung system.
- Added the patient-identified cycle linking social activity, mucus, coughing and anxiety.
- Recognised the combined effects of aspergillosis, bronchiectasis, asthma and chronic sinusitis.
- Added practical steps and clearer safety advice.
Version 0.1 – July 2026
- Initial publication.
- Introduced the brain–lung connection.
- Explained why breathlessness is more than lung function alone.
- Explored how previous experiences and emotions can influence breathing.
Next planned update
- Living with uncertainty and recognising meaningful change.
- More detail on pulmonary rehabilitation and rebuilding confidence.
- Further patient experiences and questions.
Help Shape Future Editions
Every month we review this Knowledge Hub.
Some improvements come from newly published scientific research.
Others come directly from the questions and experiences shared by people living with aspergillosis, their families and healthcare professionals.
Many of the most valuable pages on aspergillosis.org have started with a single patient question.
If there was something you expected to find but didn’t…
If something wasn’t explained clearly…
If your own experience has been different…
Or if there is a question you think every patient should have answered…
Please tell us.
Your feedback will help shape future editions of this Knowledge Hub and may inspire entirely new patient resources.
📝 Share your feedback (2–3 minutes)
Thank you for helping us build one of the world’s most comprehensive patient education resources on aspergillosis.
This Knowledge Hub has evolved thanks to our readers
Future updates will be listed here so you can see how this resource has grown over time.
| Version | What changed |
|---|---|
| 0.1 | Initial publication introducing the brain–lung connection, explaining why breathlessness is more than lung function, and describing how previous experiences and emotions can influence breathing. |
| 0.2 | Added immune and hormonal communication, stress and inflammation, sleep, medicines, overlapping respiratory conditions, patient-informed social coughing experiences, practical actions and safety advice. |
| 0.3 | Planned: living with uncertainty, pulmonary rehabilitation and further patient-informed additions. |
| 1.0 | First complete edition. |
Further reading and references
- American Thoracic Society Statement: Update on the Mechanisms, Assessment, and Management of Dyspnea
- American Thoracic Society PDF: Mechanisms, Assessment, and Management of Dyspnea
- American Thoracic Society patient information: Pulmonary Rehabilitation
- British Thoracic Society: Pulmonary Rehabilitation resources
- Global Initiative for Asthma (GINA)
- Global Initiative for Chronic Obstructive Lung Disease (GOLD)
- PubMed search: brain imaging and dyspnoea reviews
- PubMed search: quality of life in chronic pulmonary aspergillosis
- Aspergillosis Patients & Carers website
- Cohen S, Tyrrell DAJ, Smith AP. Psychological Stress and Susceptibility to the Common Cold. New England Journal of Medicine. 1991.
- McEwen BS. Stress, adaptation, and disease: allostasis and allostatic load. Annals of the New York Academy of Sciences. 1998.
- Irwin MR. Why sleep is important for health: a psychoneuroimmunology perspective. Annual Review of Psychology. 2015.
- Gao YH et al. Sleep disturbances and health-related quality of life in adults with steady-state bronchiectasis. PLoS ONE. 2014.
- Sigurgeirsdottir J et al. COPD patients’ experiences, self-reported needs, and needs-driven strategies to cope with self-management. International Journal of Chronic Obstructive Pulmonary Disease. 2019.
- NHS: Sleep apnoea—symptoms, assessment and treatment.
- NHS: Side effects of prednisolone tablets and liquid.
Suggested citation: National Aspergillosis Centre. Living with Aspergillosis: Understanding the Brain–Lung Connection. Aspergillosis.org. Version 0.2. August 2026.

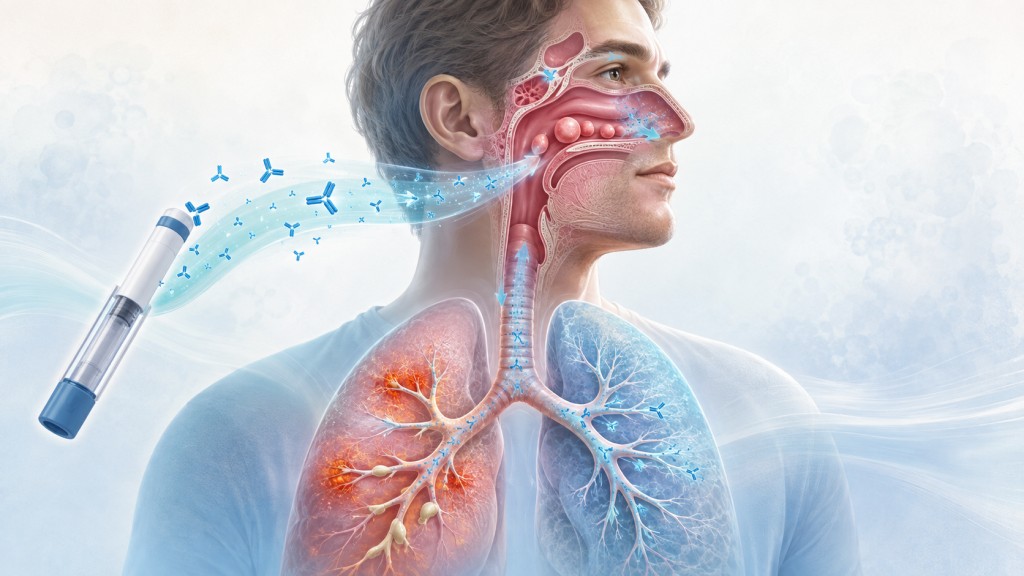
Could One Biologic Treat Nasal Polyps, Asthma and ABPA?
People living with ABPA sometimes also experience severe asthma, chronic sinus inflammation and nasal polyps that return after surgery. These may appear to be separate problems, but they can be driven partly by the same type of immune response.
This has created an important new treatment possibility. Instead of repeatedly treating the nose and lungs as unrelated problems, a biological medicine may sometimes reduce inflammation in both.
Dupilumab (brand name Dupixent) is one such biologic. It is an established treatment for selected people with severe chronic rhinosinusitis with nasal polyps and for some forms of asthma. Early clinical-trial evidence also suggests that it may benefit some people with asthma and allergic bronchopulmonary aspergillosis (ABPA), although it is not currently licensed specifically as an ABPA treatment.
Key points
- Dupilumab can shrink severe nasal polyps, improve nasal blockage and help some people regain their sense of smell.
- It can also improve suitable forms of asthma because the nose and lungs may share the same type of inflammation.
- Promising results have been reported from a randomised phase 2 trial in people with both asthma and ABPA.
- Dupilumab does not kill Aspergillus and is not a replacement for antifungal treatment when antifungals are needed.
- The most suitable biologic should ideally be chosen jointly by ENT, respiratory and severe-asthma specialists.
Why do nasal polyps keep returning?
Nasal polyps are soft, non-cancerous swellings that develop from chronically inflamed tissue inside the nose and sinuses. They can cause:
- persistent nasal blockage;
- loss or reduction of smell;
- an apparent loss of taste, because much of what we experience as flavour depends on smell;
- nasal discharge or post-nasal drip;
- facial pressure; and
- poor sleep and fatigue.
Functional endoscopic sinus surgery (FESS) can remove polyps, improve drainage and allow nasal treatments to reach the sinuses more effectively. However, surgery removes the obstructing tissue; it does not necessarily switch off the inflammation that caused it. In people with strong ongoing inflammation, polyps may therefore grow back—occasionally quite quickly.
A nasal endoscopy shows what is visible inside the nose, while a CT scan helps the ENT team assess the full extent of inflammation and blockage throughout the sinuses. The results help determine whether further surgery, medical treatment or a biologic is the most appropriate next step.
The link between the nose, asthma and ABPA
The upper and lower airways form one connected system. Many people with nasal polyps also have asthma, and both conditions are frequently associated with type 2 inflammation.
In this pattern of inflammation, immune signals including interleukin-4 (IL-4), interleukin-13 (IL-13), interleukin-5, immunoglobulin E (IgE) and eosinophils can contribute to swelling, mucus production and airway symptoms.
ABPA is more complicated because it involves an exaggerated immune response to Aspergillus, usually in a person with asthma, bronchiectasis or another susceptible airway condition. Nevertheless, type 2 inflammation is also an important part of ABPA. This overlap creates the possibility that a treatment targeting one pathway could benefit more than one part of the airway.
However, having both ABPA and nasal polyps does not automatically mean that Aspergillus is growing in the sinuses. Allergic fungal rhinosinusitis is a separate diagnosis requiring its own ENT assessment. You can read more in our guide to Aspergillus and allergic fungal disease in the sinuses.
How does dupilumab work?
Dupilumab is a monoclonal antibody—a highly targeted biological medicine. It attaches to part of the receptor used by both IL-4 and IL-13, reducing signals that drive type 2 inflammation.
It is not a general immune suppressant in the way that oral corticosteroids are, and it is not an antifungal drug. It targets a particular inflammatory pathway rather than killing Aspergillus.
For adults with severe nasal polyps, dupilumab is normally given by injection under the skin, commonly every two weeks. After training, many people can administer it themselves. It is generally used as ongoing maintenance treatment rather than as a short, fixed course, and prescribed nasal corticosteroid treatment is usually continued.
How much can it help nasal polyps?
In the large SINUS-24 and SINUS-52 clinical trials, adding dupilumab to standard nasal corticosteroid treatment reduced polyp size and nasal congestion, improved sinus-related quality of life and improved sense of smell. Across the pooled trial population, it also substantially reduced the need for systemic corticosteroids and further sinus surgery.
Some people notice an improvement in congestion relatively early, but regaining smell and achieving the full benefit may take longer. Not everyone responds, and a completely normal sense of smell cannot be guaranteed—particularly if olfactory nerves have been affected by longstanding disease or another cause.
What do we know about dupilumab in ABPA?
Biologics are already used in selected people with severe asthma and treatment-dependent ABPA, particularly when repeated courses of oral corticosteroids are needed. The 2024 international ISHAM-ABPA guidelines recognised biologics as an option for treatment-dependent disease, but they are not recommended as routine first-line treatment for a new acute ABPA episode.
The phase 2 LIBERTY ABPA AIRED trial was the first randomised placebo-controlled study of dupilumab in adults with asthma and ABPA. It enrolled 62 participants. Results presented at respiratory conferences in 2025 reported improvements in lung function and quality of life, together with fewer severe respiratory exacerbations and reduced corticosteroid use.
These findings are encouraging and provide stronger evidence than earlier case reports. However, the study was small and the findings have so far principally been reported in conference abstracts. Dupilumab is therefore best described as a promising emerging treatment for ABPA, not a proven cure or a licensed ABPA treatment.
It is also important to distinguish control of inflammation from control of fungal growth. Dupilumab may calm the allergic response, but it does not remove Aspergillus from the airway and will not replace antifungal medication when a specialist believes antifungal treatment is required.
Who can receive dupilumab for nasal polyps on the NHS?
In February 2026, NICE recommended dupilumab as an add-on to intranasal corticosteroids for a defined group of adults in England with severe chronic rhinosinusitis with nasal polyps.
The NICE criteria include:
- disease that remains inadequately controlled by systemic corticosteroids or sinus surgery;
- at least one previous sinus operation; and
- a score of at least 50 on the 22-item Sinonasal Outcome Test (SNOT-22).
SNOT-22 is a questionnaire measuring the effect of sinus symptoms on daily life, including blockage, smell and taste, sleep, fatigue, concentration and emotional wellbeing. A polyp “stage” seen during nasal endoscopy is useful clinical information, but it is not by itself the same as meeting the full NHS eligibility criteria.
Access arrangements can differ outside England and may change over time. A specialist team must assess eligibility and whether dupilumab is the best option for the individual.
Choosing a biologic when several conditions overlap
Dupilumab is not the only biologic used in airway disease. Other medicines target IgE, IL-5, the IL-5 receptor or TSLP. The best choice depends on the complete clinical picture, which may include:
- the severity and recurrence of nasal polyps;
- asthma control and the number of exacerbations;
- ABPA activity and previous treatments;
- blood eosinophil levels and fractional exhaled nitric oxide (FeNO);
- total IgE and allergen-specific IgE;
- the need for repeated or maintenance oral steroids;
- other conditions such as eczema; and
- previous response or side effects with another biologic.
For someone with severe recurrent nasal polyps, asthma and ABPA, dupilumab may be particularly attractive because it has the potential to address inflammation in both the upper and lower airways. However, another biologic may be a better match for some patients. Ideally, ENT and respiratory or severe-asthma teams should coordinate the decision rather than considering each condition in isolation.
For a broader explanation, see how NHS specialists choose biologics for ABPA and severe asthma.
What are the possible side effects?
Dupilumab is generally well tolerated, but possible adverse effects include:
- redness, swelling, itching or discomfort at the injection site;
- eye irritation or conjunctivitis;
- joint pain;
- cold sores; and
- a temporary rise in blood eosinophils.
Serious allergic reactions are rare. New or worsening eye symptoms, marked joint symptoms, a rash, breathing deterioration or other concerning symptoms should be reported to the treating team. Patients should not stop asthma inhalers, nasal treatment, corticosteroids or antifungals when starting a biologic unless their specialist provides a supervised plan.
A note about IgE and IgG
Patients understandably sometimes refer to having a “high IgG” or a “high allergy count”, but several different antibody tests may be used in ABPA.
- Total IgE reflects overall allergic activity and is commonly followed over time in ABPA.
- Aspergillus fumigatus-specific IgE demonstrates allergic sensitisation to the fungus.
- Aspergillus-specific IgG can provide evidence of immune exposure and forms part of the wider diagnostic picture, but it is not interchangeable with total IgE.
Biologic treatment can alter inflammatory markers, so blood results must be interpreted alongside symptoms, lung function and imaging rather than in isolation.
Questions to ask your specialist team
- Do my symptoms and SNOT-22 score meet the criteria for biologic treatment?
- Is my loss of smell likely to be caused entirely by polyps, or should other causes be considered?
- Could one biologic reasonably treat both my nasal disease and asthma?
- How active is my ABPA at present, and what benefit might the biologic provide?
- Will my ENT and respiratory or severe-asthma teams discuss the choice together?
- How and when will my response be assessed?
- Which nasal sprays, rinses, inhalers or other treatments should I continue?
The outlook
For people whose polyps return quickly after surgery, being told that another operation is unlikely to solve the underlying problem can be disappointing. The arrival of biologic treatment changes that conversation. It offers a way of targeting the inflammation that drives polyp regrowth rather than repeatedly removing its consequences.
For patients who also have asthma and ABPA, the possibility is especially interesting: one targeted treatment may sometimes benefit the whole airway. It will not be the right answer for everybody, and it does not replace careful ABPA monitoring or antifungal treatment when needed. Nevertheless, it represents a significant and increasingly evidence-based addition to care.
Sources and further reading
- NICE: Dupilumab for treating severe chronic rhinosinusitis with nasal polyps (2026).
- Bachert C, et al. Dupilumab in severe chronic rhinosinusitis with nasal polyps: SINUS-24 and SINUS-52. The Lancet (2019).
- Revised ISHAM-ABPA working group clinical practice guidelines. European Respiratory Journal (2024).
- Bourdin A, et al. Dupilumab efficacy in asthma and ABPA: LIBERTY ABPA AIRED. European Respiratory Journal conference abstract (2025).
- Dupixent UK Summary of Product Characteristics.
This information is intended to support, not replace, discussion with your medical team. Treatment eligibility and the balance of benefits and risks must be assessed individually.
Can We Predict Who Will Develop Aspergillosis? Genetics, Epigenetics and the Search for Individual Risk
Everyone inhales Aspergillus spores, usually every day, but only a small minority of people develop aspergillosis. Asthma, bronchiectasis, previous tuberculosis, lung cavities, transplantation and immune-suppressing treatment explain much of this difference—but not all of it.
Why does one person develop allergic bronchopulmonary aspergillosis (ABPA), another develop chronic pulmonary aspergillosis (CPA), and most people remain unaffected?
Researchers increasingly think that part of the answer lies in inherited differences affecting the airway lining, fungal recognition, immune-cell behaviour and inflammation. Epigenetics—the processes that alter how genes behave without changing the DNA sequence—may add another layer by connecting genetics with environment, exposure, inflammation and treatment.
Manchester has played an important part in this research. By combining patient DNA with studies of macrophages, airway cells, fungal load and gene editing, researchers have begun to show not merely which genetic variants are associated with aspergillosis, but how some of them might alter what happens when a fungal spore reaches the lung.
The central puzzle: exposure is common, disease is rare
Aspergillus spores are found in soil, compost, dust, decaying vegetation and indoor and outdoor air. Healthy lungs normally trap and remove inhaled spores before they can grow.
Several protective systems work together:
- mucus and moving airway cilia remove inhaled particles;
- airway epithelial cells form a protective barrier and detect fungal material;
- macrophages engulf spores that reach the air sacs;
- neutrophils attack spores that begin to germinate;
- antibodies, complement proteins and immune signals coordinate the response.
Aspergillosis becomes more likely when one or more of these defences is impaired—or when the immune response becomes excessive and allergic rather than protective.
Even so, people with apparently similar risk factors can have very different outcomes. Many people with severe asthma never develop ABPA. Many people with old tuberculosis cavities never develop CPA. Some transplant recipients develop invasive aspergillosis while others undergoing similar treatment do not.
This unexplained variation is what susceptibility genetics is trying to understand.
Genetic susceptibility is not genetic destiny
There is no single “aspergillosis gene”. Researchers instead distinguish between two broad forms of inherited risk.
Rare, high-impact variants
Rare harmful variants can cause recognised immune disorders such as chronic granulomatous disease and some hyper-IgE or combined immune-deficiency syndromes. These can substantially impair antifungal defence and occasionally lead to severe or invasive aspergillosis.
These disorders are important, but they do not explain most cases of ABPA or CPA. They are covered in more detail in our article Aspergillosis, immunity, and risk.
Common susceptibility variants
Common variants normally have much smaller effects. A variant might make the airway barrier slightly less effective, alter the removal of spores or make allergic inflammation more likely. On its own, the difference may cause no illness.
Risk may emerge only when several factors coincide:
- a susceptible airway or immune response;
- asthma or existing structural lung disease;
- corticosteroids or another immune-modifying treatment;
- repeated or heavy fungal exposure;
- ageing, infection, smoking or other acquired influences.
A susceptibility variant changes probability, not destiny. Having one does not mean that someone has aspergillosis or will develop it.
The Manchester genetics story
In 2014, University of Manchester researchers announced an ambitious project to investigate genetic susceptibility to CPA using next-generation exome sequencing.
An exome represents the protein-coding part of a person’s DNA. Although it accounts for only a small proportion of the complete genome, it contains many of the variants most likely to alter the structure or function of proteins.
The original project planned to examine approximately 160 patients from across the UK. Earlier research had concentrated on a limited number of immune genes. Exome sequencing allowed researchers to search much more widely and investigate pathways that might not previously have been connected with fungal disease.
Manchester’s wider patient and research collections have subsequently supported studies involving CPA, ABPA, fungal asthma and suitable control groups. The most informative discoveries have come from combining genetic findings with laboratory experiments.
This is important because a statistical association alone does not prove that a variant causes disease. Researchers need to show that the variant changes the behaviour of a relevant cell or biological pathway.
ZNF77: how the airway lining can encourage fungal growth
One of the clearest discoveries from Manchester’s exome work involved a variant called rs35699176 in ZNF77.
ZNF77 is a transcription factor, meaning that it helps regulate the activity of other genes. Researchers suspected that the variant might affect the bronchial epithelium—the layer of cells lining the airways.
Using CRISPR gene editing, the Manchester team recreated the variant in human bronchial epithelial cells. The altered cells:
- failed to form a normal, tightly joined epithelial layer;
- produced abnormal amounts of extracellular-matrix and adhesion proteins;
- allowed more Aspergillus fumigatus spores to attach;
- permitted earlier spore germination;
- supported greater subsequent fungal growth;
- produced altered inflammatory signals following fungal exposure.
Some extracellular-matrix proteins appeared to act rather like glue, making it easier for spores to adhere to the airway surface. Once attached, the spores germinated earlier and produced more extensive hyphal growth.
The researchers then looked for the same effect in patients. In the relatively small groups studied:
- people carrying the variant had approximately 15 times more A. fumigatus DNA in bronchoalveolar-lavage samples;
- among 45 people with ABPA, the variant was found in 9 of 32 with a positive sputum PCR but in none of the 13 with a negative PCR;
- carriers had approximately twice the fungal burden in sputum.
The major insight was that susceptibility does not have to involve conventional immune deficiency. An inherited difference in the physical and biochemical properties of the airway lining may make fungal colonisation easier.
However, the patient numbers were small and the association requires further validation. ZNF77 testing is not currently used routinely to predict fungal colonisation or ABPA.
EEA1: susceptibility can involve an overactive response
A separate Manchester study used exome sequencing in 96 people with ABPA and 167 asthmatic controls. Researchers identified variants in EEA1, a gene involved in the internal cellular compartments used to engulf and process material.
To test whether the association had a functional effect, the researchers studied macrophages obtained from people with ABPA.
Macrophages carrying the ABPA-associated EEA1 variants showed:
- increased uptake of A. fumigatus spores;
- increased acidification of the compartments containing them;
- an unusually active response to fungal material.
This finding was initially counterintuitive. The problem was not that the macrophages simply failed to respond. Instead, an exaggerated cellular response could contribute to the excessive inflammation characteristic of ABPA.
The study therefore provided another important lesson: genetic susceptibility can produce disease through too much inflammation as well as too little protection.
What has Manchester learned about CPA?
CPA usually develops in lungs already altered by previous tuberculosis, bronchiectasis, COPD, emphysema, sarcoidosis, non-tuberculous mycobacterial infection or other structural disease.
However, most people with these conditions do not develop CPA. Manchester researchers therefore compared immune responses and genetic variants in people with chronic cavitary pulmonary aspergillosis and control groups.
Their macrophage studies suggested a distinctive pattern:
- the initial response to fungal stimulation could be delayed;
- later production of inflammatory signals was greater;
- expression of several fungal-recognition receptors differed from healthy controls.
This supports a model in which early fungal clearance is not sufficiently effective, but is followed by a prolonged or excessive inflammatory response. That combination could allow Aspergillus to persist while also contributing to continuing lung damage.
Reported CPA associations have involved:
- IL1B, IL1RN and IL15, which participate in inflammatory signalling;
- TLR1 and CLEC7A/Dectin-1, which help recognise fungal material;
- VEGFA, involved in blood vessels and tissue repair;
- PLAT, involved in fibrinolysis and tissue remodelling;
- DENND1B, which participates in immune signalling.
These findings suggest relevant pathways, but they have not produced a clinically validated CPA screening panel.
Although the original Manchester project planned exome sequencing of approximately 160 people with CPA, a comprehensive final analysis of that entire cohort does not appear to have been published as a single definitive study. The available publications provide important mechanistic findings, but not a complete catalogue of validated CPA susceptibility variants.
What has been found more widely in ABPA?
Research from Manchester and elsewhere points towards several interacting processes in ABPA.
Type 2 allergic inflammation
IL-4 and IL-13 promote IgE production, eosinophilic inflammation, mucus secretion and other components of allergic immunity.
A Manchester-led association study investigated 195 variants across 22 genes. Associations involving IL13, IL4R and TLR3 remained significant after correction for multiple testing.
The findings support the idea that ABPA is not simply severe asthma combined with fungal exposure. Some people may inherit a tendency to mount an unusually strong or poorly regulated response to Aspergillus.
Airway clearance
CFTR is best known as the gene responsible for cystic fibrosis when a person inherits two disease-causing variants. Cystic fibrosis impairs mucus clearance and substantially increases the risk of ABPA.
Some people without cystic fibrosis carry one CFTR variant or have a milder CFTR-related disorder. Researchers are investigating whether reduced CFTR function contributes to mucus retention and fungal persistence in a subset of people with ABPA or bronchiectasis.
Fungal recognition
Associations have also been reported involving HLA variants, surfactant proteins and fungal-recognition pathways.
A 2023 study linked a heterozygous variant in CARD9 with ABPA. CARD9 transmits signals after immune cells recognise fungi. The finding is interesting, but it is not yet a clinically validated predictor.
PTX3 and invasive aspergillosis
The strongest progress towards clinically useful susceptibility testing has occurred in invasive aspergillosis, particularly after transplantation or intensive chemotherapy.
Pentraxin 3, or PTX3, binds to Aspergillus spores and helps neutrophils and other immune cells recognise and remove them.
Studies involving stem-cell and solid-organ transplant recipients have associated certain PTX3 variants with impaired antifungal activity and a higher risk of invasive aspergillosis.
In stem-cell transplantation, the donor’s genotype can matter because the donated cells produce the recipient’s new blood and immune cells.
A genetically guided prevention trial
The PTX3-targeted Antifungal Prophylaxis trial is testing whether genetic screening can help determine which people receiving intensive treatment for acute myeloid leukaemia should receive broad-spectrum antifungal prophylaxis.
Participants are tested for two PTX3 variants and placed into higher- or lower-risk groups. They are then assigned different prophylactic strategies involving posaconazole or fluconazole.
This is a significant step because the genetic result is not collected merely for future research: it is being used to stratify prevention within the trial.
There is currently no comparable genetic-screening trial for ABPA or CPA.
Summary of the principal candidate pathways
| Gene or pathway | Possible relevance | Current position |
|---|---|---|
| ZNF77 | Airway-barrier integrity, fungal adhesion and colonisation | Strong functional Manchester study; requires larger clinical validation |
| EEA1 | Macrophage uptake and processing of spores | ABPA association with supporting laboratory evidence |
| IL13 and IL4R | Type 2 allergic inflammation and IgE responses | Associated with ABPA, but not clinically predictive |
| HLA | Presentation and recognition of fungal proteins | Several reported ABPA associations; variable between populations |
| TLR and CLEC7A pathways | Recognition of fungal material | Candidate associations in ABPA, CPA and invasive disease |
| CFTR | Mucus clearance and airway defence | Important in cystic fibrosis; wider contribution remains under investigation |
| CARD9 | Signalling after fungal recognition | Rare deficiency causes major susceptibility; ABPA association is emerging |
| PTX3 | Labels spores for immune recognition and clearance | Strongest translational evidence in invasive aspergillosis |
What can epigenetics add?
The DNA sequence inherited from our parents is not the complete set of instructions used by every cell. Cells also regulate which genes are active, when they are activated and how strongly they are expressed.
Epigenetics describes mechanisms that influence gene activity without changing the underlying DNA sequence. These include:
- DNA methylation;
- chemical modification of histone proteins around which DNA is packaged;
- changes in chromatin accessibility;
- microRNAs and other molecules that regulate gene expression;
- longer-lasting reprogramming of innate immune cells, sometimes called trained immunity.
Some epigenetic patterns can change during life. They may be influenced by ageing, infection, smoking, air pollution, medication, inflammation and environmental exposure.
This makes epigenetics a plausible bridge between genes and environment. Two people could inherit similar genetic risks but develop different immune responses because their cells have experienced different exposures or illnesses.
Does DNA methylation cause susceptibility?
There is substantial evidence that DNA methylation is involved in asthma, allergy and immune development. Experimental work also shows that exposure to Aspergillus can alter gene expression and regulatory pathways in epithelial and immune cells.
However, direct human evidence that a particular methylation pattern causes susceptibility to ABPA or CPA remains very limited.
A methylation difference detected in someone with established aspergillosis could:
- have existed before the illness and contributed to susceptibility;
- have developed in response to fungal exposure or disease;
- reflect asthma, bronchiectasis or chronic inflammation;
- have been influenced by smoking, corticosteroids or other treatment;
- reflect a change in the types of cells present in the sample.
Researchers therefore need studies that collect samples before disease develops, or compare carefully matched groups, to distinguish cause from consequence.
Methylation is currently a promising research direction—not an established explanation for why an individual developed aspergillosis.
Patient genetics and fungal genetics are different
Manchester also maintains major resources relating to the genome of Aspergillus fumigatus itself.
The COFUN project aims to create approximately 10,000 fungal strains, each with a different gene removed. By observing what happens when individual genes are deleted, researchers can identify genes involved in:
- fungal growth and survival;
- pathogenicity and tissue damage;
- stress responses;
- azole and other antifungal resistance;
- potential new drug targets.
Manchester research has identified both conventional resistance mechanisms involving cyp51A and non-target mechanisms involving transporters, transcription factors, mitochondrial function and cellular signalling.
This is fungal genomics rather than human susceptibility genomics. Both are important, but they answer different questions: one examines why a patient may be vulnerable, while the other examines why a fungal strain may be particularly resistant or capable of causing disease.
Why is there still no clinical susceptibility test?
Several obstacles have slowed translation into patient care:
- ABPA, CPA and invasive aspergillosis have different mechanisms;
- many studies have included relatively few patients;
- variant frequencies differ between populations;
- underlying diseases and treatments are powerful confounding factors;
- some associations disappear when examined in independent cohorts;
- the effect of any one common variant is usually small;
- a statistical association does not necessarily demonstrate causation.
The Manchester ZNF77 and EEA1 studies are valuable because they went beyond association and demonstrated biological effects in relevant human cells. Even so, they require larger prospective clinical validation before testing can guide care.
Could several markers be combined?
A useful prediction system is unlikely to depend on one gene. It may combine:
- multiple genetic variants in a polygenic risk score;
- immune-cell function and inflammatory biomarkers;
- gene-expression and epigenetic patterns;
- CT findings and the extent of lung damage;
- asthma, bronchiectasis, COPD or previous tuberculosis;
- corticosteroids and other immune-modifying treatments;
- fungal sensitisation, antibodies, culture and PCR;
- environmental exposure.
This combined approach is sometimes called multi-omics or precision medicine. Rather than searching for one faulty gene, researchers examine how inherited variation, gene regulation, immune cells, lung structure, fungal biology and exposure interact.
Is testing useful for patients now?
There is currently no clinically validated genetic, polygenic or methylation test that can reliably predict ABPA or CPA.
Specialist genetic or immunological investigation may nevertheless be appropriate when aspergillosis:
- occurs unusually early in life;
- is recurrent, invasive or affects unusual sites;
- occurs without the expected lung or treatment-related risk factors;
- is accompanied by recurrent bacterial, viral or other fungal infections;
- occurs alongside features suggesting an inherited immune disorder.
Commercial sequencing can also identify a variant of uncertain significance. This means that a DNA difference has been found but there is insufficient evidence to determine whether it affects health. Such a result is not a diagnosis and requires specialist interpretation.
Routine genetic testing of healthy relatives of people with ABPA or CPA is not currently recommended solely because of the family connection.
What this means for patients
The Manchester research has helped replace a simple idea—“some patients have weak immunity”—with a more sophisticated picture.
Susceptibility may involve:
- an airway surface that allows spores to adhere and germinate;
- immune recognition that starts too slowly;
- a later response that becomes excessive or damaging;
- mucus that is difficult to clear;
- several small inherited differences acting alongside lung damage and exposure.
Genetics probably contributes to the striking differences between people exposed to the same fungus. Epigenetic regulation may add another layer by allowing inflammation, treatment and environment to influence how genes behave.
But current evidence does not show that most people with aspergillosis carry a single faulty gene. Nor can a genetic or methylation test yet tell most patients precisely why they became ill or predict what will happen next.
The immediate value of this research is a better understanding of disease mechanisms. Its longer-term promise is more practical: identifying people who need closer monitoring, selecting preventive treatment for those at greatest risk and matching treatment to the biological pathway driving disease.
For now, symptoms, clinical history, lung structure, immune status, imaging and established fungal tests remain much more important than susceptibility genetics in diagnosing and managing aspergillosis.
Selected research and further reading
- University of Manchester: the original CPA exome-sequencing project.
- Gago S et al. Lung colonisation by Aspergillus fumigatus is controlled by ZNF77.
- Overton NLD et al. EEA1 variants, ABPA and macrophage phagocytosis.
- Overton NLD et al. Genetic susceptibility to ABPA in asthma.
- Smith NL et al. IL-1 and IL-15 pathways in chronic cavitary pulmonary aspergillosis.
- Smith NL et al. Macrophage receptor expression and genetic associations in chronic cavitary pulmonary aspergillosis.
- PTX3-targeted antifungal prophylaxis trial.
- Manchester Fungal Infection Group.
- Aspergillosis, immunity, and risk.
Last reviewed: August 2026

Air Conditioning, Mould and Aspergillosis
Air conditioning can make hot weather more comfortable and may help reduce indoor humidity. However, any system that becomes damp, dirty or poorly maintained can provide conditions in which mould and bacteria grow.
This is particularly important for people with aspergillosis, severe asthma, bronchiectasis or other respiratory conditions. Air conditioning does not inevitably expose people to Aspergillus—the condition and maintenance of the equipment are what matter.
How can mould develop in an air-conditioning system?
Air conditioners cool warm air. As the air cools, water condenses on the cooling coils and should drain safely away. Problems can develop when:
- condensate collects in a blocked, damaged or poorly draining tray;
- filters and internal surfaces accumulate dust and remain damp;
- the unit or surrounding building has a water leak;
- the equipment is left unused while damp and dirty;
- maintenance and filter replacement are neglected.
Damp dust and debris can support fungal growth. Air moving through contaminated equipment may then carry fungal particles, fragments and odours into the occupied room. UK indoor-air guidance recommends regular cleaning and filter replacement to maintain ventilation performance and reduce microbial growth and bioaerosols.
Can air conditioning help prevent mould?
Yes. Correctly sized and properly maintained air conditioning can remove moisture from indoor air. This may make mould growth less likely, particularly during warm, humid weather.
A conventional air conditioner normally uses a refrigerant circuit, similar to a refrigerator or heat pump. Warm indoor air passes over a cold evaporator coil, where water vapour condenses. The collected water is then:
- carried away through a condensate drain;
- collected in a tank that must be emptied; or
- in some portable units, evaporated again and expelled outside with the hot air through the exhaust hose.
During very humid conditions, a self-evaporating portable unit may still collect more water than it can expel, so its internal tank may need emptying.
An air conditioner must also release the heat it has removed. Fixed split systems use an outdoor condenser, while portable air conditioners usually discharge hot air through a hose fitted to a window or external vent. A unit with no refrigerant compressor and no way to release heat outside is unlikely to be a true room air conditioner.
A unit that is too large may cool a room quickly without removing enough moisture, while a poorly maintained or blocked unit may leak water or allow condensation to accumulate.
Air conditioners and evaporative air coolers are different
Some portable devices are marketed as “air conditioners,” “mini air conditioners” or “personal air conditioners” but are actually evaporative air coolers. These pass air across wet paper, pads, filters or wicks.
Evaporation can make the outgoing air feel cooler, but these devices add water to the indoor air rather than removing it. They work less effectively in humid conditions and may be unsuitable in a home that is already damp or poorly ventilated.
Their water tanks and continually wet internal surfaces also require careful cleaning and drying according to the manufacturer’s instructions. If neglected, they may support the growth of mould or bacteria.
Before buying or using a portable cooling unit, check whether it:
- uses a refrigerant and compressor;
- has an exhaust hose or outdoor condenser through which heat is released;
- removes condensate into a drain or collection tank; or
- relies on a water reservoir and wet pad to cool the air by evaporation.
This distinction is important for anyone trying to reduce indoor humidity or mould exposure.
Warning signs that need attention
Stop using the unit and arrange an inspection if you notice:
- a persistent musty or mouldy smell when it is running;
- visible mould around the vents or inside an accessible cover;
- water dripping from the unit or collecting beneath it;
- a persistently wet filter or condensate tray;
- a noticeable worsening of respiratory symptoms when the unit is operating.
These signs do not prove that Aspergillus is present, but they indicate that the system needs investigation.
Using air conditioning safely at home
- Follow the manufacturer’s servicing and filter-cleaning schedule. Different systems require different intervals.
- Make sure condensate drains freely and investigate any water leakage promptly.
- Replace disposable filters rather than washing them unless the manufacturer specifically describes the filter as washable.
- Keep the area around outdoor air intakes free from compost, decaying vegetation and other obvious sources of dust and mould.
- Do not fit a very dense filter unless the system is designed for it. Restricting airflow can reduce performance and cause additional condensation.
- Remember that many domestic split air-conditioning units recirculate indoor air and do not provide fresh-air ventilation. Continue to ventilate the room appropriately.
A portable HEPA air cleaner may reduce some airborne particles, but it will not correct a contaminated air-conditioning unit, blocked drain or damp building.
Should someone with aspergillosis clean the unit?
People with aspergillosis should not dismantle or clean visibly contaminated equipment themselves. Opening the unit, brushing a filter or using compressed air could release accumulated dust and fungal material.
Ask someone without a respiratory condition to undertake straightforward routine filter maintenance, following the manufacturer’s instructions. Visible mould, a musty smell, internal contamination or drainage problems should be assessed by a competent air-conditioning engineer or ventilation specialist.
Tell the engineer that somebody in the property has aspergillosis or another serious respiratory condition. Ask how contaminated material will be contained and whether the person should leave the room or property while the work is undertaken.
Air conditioning in cars
Vehicle systems can also develop musty odours when the cabin filter is dirty or moisture remains around the evaporator. Have the cabin filter and drainage system checked during routine servicing. A persistent smell should be investigated rather than covered with an air freshener or deodorising spray.
At work, in hotels and while travelling
You may not be responsible for maintaining equipment at work or in rented accommodation, hotels and holiday properties. If a unit smells musty, leaks water or appears visibly dirty:
- switch it off if it is safe and practical to do so;
- ask for another room or working area;
- report the problem to the employer, landlord or accommodation manager;
- do not open or clean an unfamiliar unit yourself.
A musty smell alone cannot identify the organism involved, and respiratory symptoms can have many causes. Seek medical advice if symptoms become severe or do not settle after leaving the affected environment.
Further information
- UK Government: Indoor Air Quality Report
- US Environmental Protection Agency: mould and HVAC systems
- How can I remove mould from my home safely?
- Aspergillosis Housing Hub

How Can I Remove Mould from My Home Safely?
Updated August 2026
Visible mould should be dealt with promptly, but cleaning it can release spores and fragments into the air. Cleaning products can also irritate the eyes, skin and airways.
If you have aspergillosis, significant lung disease or a weakened immune system, ask someone else to remove the mould whenever possible. Large, persistent or widespread mould should be assessed and removed professionally.
Cleaning is only part of the solution
Mould grows where there is excess moisture. Removing the visible growth may reduce immediate exposure, but it will return unless the source of the damp is identified and corrected.
Possible causes include:
- condensation on cold walls, ceilings or windows;
- inadequate or broken ventilation;
- leaking pipes, roofs or gutters;
- water entering around windows or through external walls;
- inadequate heating or insulation;
- furniture preventing air from circulating around cold walls; and
- previous flooding or water damage.
Before cleaning, photograph the affected area. If you rent your home, report the damp and mould to your landlord or housing provider in writing. Cleaning mould yourself does not remove the landlord’s responsibility to investigate relevant building defects or health hazards.
For more detailed advice, see Preventing Damp in Your Home.
When not to clean mould yourself
Arrange professional assessment or removal if:
- the mould covers a large area or affects more than one room;
- it keeps returning after cleaning;
- there is a persistent musty smell but no obvious source;
- wallpaper, plasterboard, carpets or insulation are extensively affected;
- the mould followed flooding, sewage contamination or dirty water;
- there is structural damp or a significant leak;
- removal would involve disturbing wallpaper, carpets, ceilings or building materials; or
- the person who would do the cleaning has aspergillosis, asthma, significant lung disease or a weakened immune system.
Disturbing contaminated wallpaper, carpets, plasterboard or insulation can release large quantities of spores and should not be treated as ordinary household cleaning.
How to clean a very small patch
A small, localised patch may be cleaned by someone who is well enough to do so, provided the moisture problem is also being addressed.
- Keep other people away. Close the internal door to reduce the spread of spores and cleaning aerosols into the rest of the home.
- Ventilate to the outside. Open a window during and after cleaning, where it is safe to do so. Do not use a fan that could blow spores around the room.
- Wear protective equipment. Use waterproof gloves and eye protection. A well-fitting FFP2 or FFP3 mask can reduce inhalation of mould spores and some liquid droplets. However, these masks do not protect against chemical gases or vapours, so ventilation remains essential. See our face-mask guidance.
- Choose a product intended for household mould. Check that it is suitable for the surface and follow its instructions exactly. Do not assume that using extra product or leaving it on for longer will work better.
- Avoid creating spray mist. Do not breathe directly over the area. If the label permits, applying the product to a cloth rather than spraying it into the air may reduce inhalation exposure.
- Wipe rather than disturb. Use a damp disposable cloth or sponge. Do not dry-brush, sand, scrape or use an ordinary vacuum cleaner, as this can spread spores and fragments.
- Dry the surface completely. Mould is likely to return if the material remains damp.
- Dispose of waste safely. Place used cloths, sponges and removed material in a bag, seal it and dispose of it. Wash reusable protective clothing separately and wash your hands after removing gloves.
Bleach-based mould removers
Many purpose-made mould removers contain sodium hypochlorite—the active ingredient in bleach. These products can kill and remove superficial mould from suitable hard, non-porous surfaces and may also remove staining.
However, sodium hypochlorite products remain hazardous. They can irritate or damage the eyes and skin, and their spray or fumes may aggravate sensitive airways. They may discolour or damage some materials and cannot reliably remove mould that has penetrated porous materials.
Ordinary household or thick toilet bleach is generally formulated and labelled for toilets, laundry or disinfection—not necessarily for removing mould from walls or other household surfaces. It may also contain fragrances, detergents or other ingredients. Do not improvise with toilet bleach unless its label specifically states that it is suitable for the intended surface and purpose.
Use no more product than the label recommends. Sodium hypochlorite is a broad biocide and can harm aquatic organisms, so avoid unnecessary use and follow the disposal instructions.
Never mix bleach or a bleach-based mould remover with another cleaning product. Contact with acids, descalers, ammonia and some other chemicals can release dangerous gases.
Bleach-free and “quat” mould products
Some bleach-free disinfectants and mould products contain quaternary ammonium compounds, often called quats. Names on the ingredients list may include benzalkonium chloride or didecyldimethylammonium chloride (DDAC).
Quat products can be effective on suitable surfaces and may be less likely to cause bleaching or discolouration. However, “bleach-free” does not mean harmless or environmentally friendly.
Quats can irritate the skin, eyes and airways. Evidence from people with repeated occupational exposure shows that some quats can cause sensitiser-induced asthma. Their effects from occasional domestic use are less certain, but people with sensitive lungs should still minimise exposure.
If using a quat-based product:
- follow the label exactly;
- wear gloves and protect your eyes;
- ventilate the room well;
- avoid breathing spray mist;
- use only the amount required; and
- follow the disposal instructions, as some quats are hazardous to aquatic life.
Never combine a quat product with bleach, a chlorine-based mould remover or another cleaner. Use one product only and keep different disinfectants stored separately.
What about soft or porous materials?
Mould can grow inside carpets, ceiling tiles, insulation, mattresses, soft furnishings, unsealed wood and damaged plasterboard. Surface cleaning may not remove growth from within these materials.
Badly affected porous materials may need to be safely removed and discarded. Washable clothing should be cleaned according to its care instructions and dried completely. Valuable or delicate items may require advice from a specialist cleaner.
After cleaning
Check the area regularly. If the mould returns, the underlying moisture problem has not been resolved. Do not repeatedly clean or paint over it without further investigation.
The safest approach is to use the least hazardous method that will remove the mould effectively, while minimising exposure to both mould spores and cleaning chemicals.
How can I find a trustworthy professional?
There is no single UK licence that guarantees competence in mould remediation. Membership logos and qualifications are useful, but they should always be checked with the organisation that issued them.
- Start with an independent diagnosis. For extensive, recurring or unexplained damp and mould, consider an independent RICS-chartered building surveyor. Alternatively, look for a damp surveyor holding the CSDB or CSTDB qualification. Ideally, the person diagnosing the problem should not also be selling the treatment.
- Obtain two or three written quotations. Each quotation should explain the moisture source, what materials will be cleaned or removed, how spores and dust will be contained, and how recurrence will be prevented.
- Check credentials independently. Possible directories include the Property Care Association, TrustMark and, particularly for substantial water-damage or mould-remediation work, the IICRC Global Locator. Check the person or business in the relevant directory rather than relying on a logo displayed on its website.
Before appointing anyone, ask for:
- evidence of suitable insurance;
- relevant qualifications and recent experience of similar work;
- a written survey, scope of work, price and timescale;
- a method for protecting occupants and preventing mouldy dust and spores spreading through the home;
- details of containment, ventilation, HEPA-filtered equipment and waste disposal where appropriate;
- confirmation that the leak, condensation or other moisture source will be corrected—not merely covered with paint or chemicals;
- references, guarantees and a written complaints procedure.
Be cautious about a “free damp survey” provided by a company selling one particular treatment. Warning signs include pressure selling, an immediate diagnosis based only on a photograph or damp-meter reading, recommending fogging or biocide treatment without correcting the moisture source, and promising a permanent cure without explaining why the mould developed.
Tell the surveyor or contractor that somebody in the home has aspergillosis or another serious respiratory condition. Ask how the person will be protected during the work and when it will be safe for them to return.
If the mould followed an insured leak or flood, contact the insurer before commissioning work. Tenants should normally report the problem to their landlord and obtain written agreement before arranging or paying for professional work. See our Housing Hub for further guidance.
Further information
- Preventing Damp in Your Home
- Housing and Environment Hub
- Choosing the Right Face Mask for Aspergillosis
- UK government guidance on damp, mould and health
- UK HSE guidance on using biocidal products safely
Lung Colonisation by Aspergillus fumigatus Is Influenced by a ZNF77 Gene Variant
Updated August 2026
Most people regularly inhale spores from Aspergillus fumigatus, but healthy airways usually remove them before they can persist or grow. Researchers have been investigating why this natural clearance appears to work less effectively in some people.
A study published in Nature Communications in 2018 identified a possible genetic factor. Researchers from the Manchester Fungal Infection Group studied a variant called rs35699176 in a gene known as ZNF77.
What does ZNF77 do?
ZNF77 helps regulate the airway epithelium—the layer of cells lining and protecting the breathing tubes. This lining is not simply a physical barrier. It also helps trap, remove and respond to inhaled microorganisms.
In laboratory experiments, researchers used gene editing to introduce the ZNF77 variant into human bronchial epithelial cells. Cells carrying the variant formed a less complete protective layer and produced increased amounts of proteins to which fungal spores could adhere.
Compared with ordinary airway cells, the altered cells allowed Aspergillus fumigatus spores to:
- attach more readily to the airway surface;
- begin germinating sooner;
- grow more rapidly; and
- produce a stronger inflammatory response.
What was found in people with ABPA?
The researchers also examined respiratory samples from relatively small groups of patients. Among 45 people with allergic bronchopulmonary aspergillosis (ABPA), the ZNF77 variant was found in nine of the 32 people whose sputum contained detectable Aspergillus. It was not found in the 13 people whose sputum PCR test was negative.
People carrying one copy of the variant also tended to have higher fungal loads in their airways. However, the study did not show that they had more severe asthma, poorer lung function or worse clinical outcomes.
Does this mean ZNF77 causes ABPA?
No. ABPA is a complex condition involving fungal exposure, airway disease, immune responses and probably several genetic and environmental influences. One gene variant cannot by itself explain why someone develops ABPA.
The study suggested that rs35699176 may make the airway surface more permissive to Aspergillus fumigatus. This could be one part of the process that allows the fungus to persist and trigger allergic inflammation in susceptible people.
Can patients be tested for this variant?
ZNF77 testing has not become part of routine ABPA diagnosis or treatment. The original patient groups were small, and larger studies following people over time would be needed to establish whether testing reliably predicts disease, treatment response or clinical outcomes.
The 2024 international clinical guidelines for ABPA use evidence of fungal sensitisation, total IgE, eosinophil counts, Aspergillus-specific IgG and characteristic imaging findings. They do not currently recommend ZNF77 genetic testing.
Why does the research still matter?
This study helped demonstrate that the airway lining actively influences whether Aspergillus spores are cleared or allowed to persist. It also identified fungal adhesion to airway cells as a possible target for future research.
Although the finding has not yet produced a clinical test or treatment, it remains an important example of how differences in our airway defences may contribute to susceptibility to aspergillosis.
For patients: having ABPA does not currently indicate a need for ZNF77 testing. Diagnosis and treatment should continue to be based on symptoms, blood tests, imaging, respiratory samples and specialist clinical assessment.
Further reading
- Gago S and colleagues: Lung colonization by Aspergillus fumigatus is controlled by ZNF77
- Revised international guidelines for diagnosing and treating ABPA
Help Us Improve Aspergillosis.org: Our New One-Minute Feedback Survey
We have introduced a simple new way for visitors to tell us whether the information on Aspergillosis.org has helped them.
At the bottom of every article and page, you will now find a short invitation:
Did this page help you? Tell us in one minute.
Why are we asking for feedback?
Aspergillosis.org provides information and support for patients, families, carers and healthcare professionals around the world. Website statistics can tell us how many people visit a page, but they cannot tell us whether the information made a meaningful difference.
Your feedback will help us understand whether a page:
- improved your understanding;
- helped you feel better informed or reassured;
- made you feel more able to manage your health;
- helped you prepare for a conversation with a healthcare professional;
- encouraged you to seek medical advice; or
- provided information worth sharing with someone else.
This evidence will help us improve existing pages, identify subjects that need clearer information and decide what new resources to develop.
How does it work?
When you select the feedback button, a short Microsoft Forms survey will open in a new tab. It should take approximately one minute to complete.
The survey automatically records the title and public web address of the page you were reading. This allows us to understand which individual articles and resources are making a difference.
Is the survey anonymous?
The survey does not ask for your name, email address or contact details, and you do not need to sign in.
Please do not include names, contact details or confidential medical information in the optional comments box.
How you can help
Whenever an article, meeting page or other resource helps you, please take a moment to use the feedback button. Even a very short response gives us valuable evidence about what our community needs and how our work is helping.
Thank you for helping us make Aspergillosis.org more useful, accessible and responsive to the people who rely on it.
Aspergillosis Research Update: Corticosteroid Risks, Azole Resistance and Immune Recovery
Research published between 21 July and 3 August 2026
Recent aspergillosis research has highlighted the relationship between corticosteroid treatment and pulmonary aspergillosis, a possible future method for restoring the activity of azole antifungals, and the importance of the immune response during recovery from invasive aspergillosis.
The most immediately relevant study found a strong, dose-related association between corticosteroid exposure and pulmonary aspergillosis. The other studies are earlier-stage research but may contribute to more personalised monitoring and new treatments in the future.
1. Corticosteroid use linked to an increased risk of pulmonary aspergillosis
A large Danish population-based study has examined whether inhaled and oral corticosteroids are associated with chronic pulmonary aspergillosis (CPA) and invasive pulmonary aspergillosis (IPA).
The researchers identified 1,351 people diagnosed with pulmonary aspergillosis other than allergic bronchopulmonary aspergillosis (ABPA). Each person was matched with five controls of the same age and sex.
Both inhaled and oral corticosteroid use were associated with an increased risk of pulmonary aspergillosis:
- Lower-dose inhaled corticosteroids were associated with approximately 1.7 times the risk.
- Higher-dose inhaled corticosteroids were associated with approximately 2.8 times the risk.
- Lower-dose oral corticosteroids were associated with approximately three times the risk.
- Higher-dose oral corticosteroids were associated with approximately four times the risk.
Higher-dose inhaled corticosteroids were associated with invasive pulmonary aspergillosis, while oral corticosteroid exposure was associated with both CPA and IPA. The association became weaker as more time passed since corticosteroid exposure.
The presence of a dose-response relationship strengthens the evidence: people exposed to higher corticosteroid doses generally had a greater risk. However, this was an observational study and cannot prove that corticosteroids directly caused every case. People requiring higher doses may also have more severe COPD or other lung damage that independently increases their risk.
An accompanying editorial by Professor David Denning argues that the findings should increase awareness of potentially fatal aspergillosis among people with COPD receiving corticosteroids.
What does this mean for patients?
Corticosteroids are important medicines that control inflammation and can prevent serious asthma or COPD exacerbations. This study does not mean that people should stop inhaled or oral corticosteroids.
Instead, it supports careful prescribing, using the lowest effective dose and regularly reviewing whether continued corticosteroid treatment is necessary. Clinicians should also consider aspergillosis when someone with COPD or another chronic lung condition develops unexplained or persistent deterioration, particularly during repeated or high-dose corticosteroid treatment.
Patients should not reduce or stop corticosteroids without discussing this with their clinical team. Suddenly stopping oral corticosteroids can be dangerous, particularly after prolonged treatment.
Read the corticosteroid study in Thorax
Read the accompanying editorial
2. Could resistant Aspergillus be made sensitive to azoles again?
Azole antifungals—including itraconazole, voriconazole, posaconazole and isavuconazole—are central to the treatment of many forms of aspergillosis. Unfortunately, some strains of Aspergillus fumigatus are resistant to one or more azoles, leaving patients with fewer treatment options.
Laboratory researchers have now investigated a different part of the fungal pathway used to produce ergosterol, an essential component of the fungal cell membrane.
They identified an enzyme called Erg7A, or lanosterol synthase, as a potential treatment target. Genetically disrupting this enzyme made resistant Aspergillus more sensitive to azoles. This effect was seen in clinical isolates with different resistance mechanisms, including mutations affecting cyp51A and hmg1.
The researchers also tested an experimental lanosterol-synthase inhibitor called Ro 48-8071. When combined with itraconazole or posaconazole, it produced a strong synergistic effect and restored azole susceptibility in resistant isolates.
What does this mean for patients?
This is promising laboratory research, but it is not yet a treatment that can be offered to patients. Ro 48-8071 also affects the human version of lanosterol synthase, so researchers would need to develop safer compounds that selectively target the fungal enzyme.
Further testing in animal models would be required before any human clinical trial could begin. Nevertheless, the study provides an interesting strategy: instead of abandoning azoles when resistance develops, a future combination treatment might make the fungus responsive to them again.
3. Aspergillus-specific immune cells may help predict recovery
Successful treatment of invasive aspergillosis depends on antifungal medication and on the patient’s immune system recovering sufficiently to control the infection.
The OPTIFIL study examined 39 people with haematological malignancies who had localised invasive pulmonary aspergillosis. Researchers measured immune cells that recognised Aspergillus and produced interferon-gamma, an important immune signalling molecule.
These Aspergillus-specific T cells were detected in 41% of patients. Their presence was associated with better outcomes after six weeks, while their absence was associated with uncontrolled infection.
One important limitation was lymphopenia—a very low number of lymphocytes in the blood—which made the test difficult to interpret in some patients.
What does this mean for patients?
The study supports the idea that monitoring the recovery of antifungal immunity might provide useful information alongside scans, cultures, biomarkers and clinical symptoms.
In the future, this type of test might help identify people whose immune systems are recovering and those who remain at particularly high risk. It could also contribute to research into immune-based treatments.
However, this was a small study involving a highly selected group of patients with blood cancers. The test is not ready for routine clinical use and requires validation in larger and more varied patient populations.
Read the study in The Journal of Infectious Diseases
4. How immune-cell metabolism can weaken antifungal defence
A separate laboratory study investigated itaconate, a naturally produced metabolite that helps regulate inflammation during infection.
Although limiting excessive inflammation can protect lung tissue, the researchers found that itaconate can also suppress parts of the innate immune response during fungal pneumonia. This may reduce the immune system’s ability to control fungal growth.
The study adds to growing evidence that immune responses to fungal infection require a careful balance. Too little immune activity can allow infection to progress, while excessive inflammation can damage the lungs.
What does this mean for patients?
This is early mechanistic research and does not currently change treatment. Itaconate should not simply be considered “good” or “bad”: its effects depend on the infection, immune response and stage of disease.
Understanding these metabolic pathways may eventually help researchers develop treatments that improve antifungal immunity without causing damaging inflammation.
Overall message
The clearest clinical finding from this fortnight is the dose-related association between corticosteroid exposure and pulmonary aspergillosis. It reinforces the importance of reviewing corticosteroid treatment and recognising aspergillosis as a possible explanation for unexplained deterioration in people with chronic lung disease.
The remaining studies point towards two longer-term possibilities: overcoming azole resistance by making resistant fungi sensitive again, and using measurements of antifungal immunity to understand prognosis and personalise care.
Neither approach is ready for routine treatment, but both address major unmet needs in aspergillosis care.
This update summarises recently published research for patients, carers and non-specialist healthcare professionals. Observational associations do not necessarily establish cause and effect, while laboratory findings may not translate into safe or effective treatments in humans. Some appraisal is based on abstracts and available publisher information; full-text review may refine individual details.
This information is educational and does not replace advice from your clinical team. Do not start, stop or alter corticosteroid or antifungal treatment without medical guidance.
Rezafungin for chronic pulmonary aspergillosis: encouraging early evidence while clinical trial continues
A once-weekly intravenous antifungal called rezafungin is being investigated as a possible treatment for chronic pulmonary aspergillosis (CPA). It could eventually provide another option for people who cannot take azole antifungals or whose infection has become resistant to them.
Early evidence includes encouraging results from one patient with difficult-to-treat CPA, together with laboratory evidence that rezafungin is active against a large collection of Aspergillus isolates. However, the main clinical trial is still underway and has not yet reported its results.
Why are new treatments for CPA needed?
CPA is usually treated with azole antifungal medicines such as itraconazole, voriconazole, posaconazole or isavuconazole. These are taken by mouth and can be effective, but treatment commonly lasts for many months and sometimes considerably longer.
Unfortunately, azoles are not suitable for everyone. Problems can include:
- side effects;
- interactions with other medicines;
- difficulty achieving an effective drug concentration;
- liver toxicity or other complications;
- the development of azole-resistant Aspergillus.
When azoles cannot be used, the alternatives are limited. Intravenous antifungals such as liposomal amphotericin B, micafungin and caspofungin may be considered, but some require daily administration and can be difficult to sustain over an extended period.
Rezafungin may offer a more convenient alternative because it only needs to be administered once a week.
What is rezafungin?
Rezafungin is a long-acting member of the echinocandin class of antifungal medicines. Echinocandins interfere with the production of beta-1,3-D-glucan, an important component of the fungal cell wall.
Rezafungin remains in the body for much longer than older echinocandins. After an initial loading dose, it can be given by intravenous infusion once weekly.
The medicine is already approved for treating invasive candidiasis, a serious infection caused by Candida. It is not currently approved as a standard treatment for CPA, and its effectiveness against CPA has not yet been established.
Encouraging experience in one patient
A case report published in JAC-Antimicrobial Resistance described the use of rezafungin in a patient with CPA and very limited treatment options.
The patient had been diagnosed with CPA in 2020 and experienced breathlessness, coughing, lethargy and repeated episodes of coughing up blood. CT scans showed progressive cavities and nodules affecting both lungs.
The patient received once-weekly intravenous rezafungin for 12 weeks through an outpatient intravenous treatment service.
During treatment:
- symptoms improved substantially;
- there were no further emergency visits, compared with eight during the preceding year;
- the patient’s Aspergillus IgG level fell from 165 to 98 mgA/L;
- CT imaging showed a slight improvement in the inflammation surrounding the lung cavities.
The treatment was also considered more convenient than an echinocandin requiring daily intravenous administration.
These findings are encouraging, but this was only one patient. A case report cannot tell us how frequently people with CPA will benefit, how long any improvement will last or how rezafungin compares with existing treatments.
The Phase 2 clinical trial
A Phase 2 study is now formally evaluating rezafungin in adults with CPA who have limited treatment options.
The international study, identified as NCT06794554, plans to include approximately 60 participants. Everyone enrolled receives rezafungin, so this is an open-label, single-arm trial rather than a comparison between rezafungin and another antifungal.
Participants receive:
- a 400 mg intravenous loading dose;
- 200 mg intravenously once a week afterwards;
- a total of 26 doses over six months.
Researchers are assessing changes in symptoms and quality of life using the St George’s Respiratory Questionnaire, together with changes in body weight and CT imaging. Safety and side effects are also being monitored.
The trial began in 2025 and is currently listed as active but no longer recruiting. No results have yet been published or posted on the trial registry. Because each participant receives six months of treatment and requires follow-up, a full analysis is unlikely to be available until 2027.
What do the laboratory findings show?
Additional laboratory results were presented at ESCMID Global in April 2026.
Researchers examined rezafungin against almost 1,000 Aspergillus isolates collected internationally over 11 years. Most were Aspergillus fumigatus, the species most commonly associated with CPA.
Rezafungin showed activity against the isolates at low laboratory concentrations, with broadly consistent results across different geographical regions. Its activity was similar to that of the existing echinocandin anidulafungin.
This supports the biological rationale for studying rezafungin in aspergillosis. However, laboratory susceptibility does not necessarily mean that a medicine will produce a meaningful improvement in patients. That is what the Phase 2 trial must establish.
Why could once-weekly treatment matter?
A treatment requiring one infusion each week could be considerably easier for patients and healthcare services than daily intravenous therapy.
Potential benefits could include:
- fewer hospital or outpatient visits;
- less disruption to patients and carers;
- easier delivery through outpatient intravenous therapy services;
- a non-azole option with fewer drug interactions;
- an additional treatment possibility for azole-resistant CPA.
Rezafungin is still an intravenous treatment, however. It would not offer the convenience of taking tablets at home, and the practicalities and cost of prolonged intravenous treatment would still need consideration.
What don’t we know yet?
Several important questions remain unanswered:
- How many people with CPA respond to rezafungin?
- How substantial are improvements in symptoms and CT appearances?
- Does it stop CPA from progressing?
- How durable is the response after treatment finishes?
- Which patients are most likely to benefit?
- Is six months the most appropriate treatment duration?
- How safe is repeated long-term treatment?
- How does it compare with azoles, other echinocandins or liposomal amphotericin B?
The present trial has no control group and is relatively small, so further comparative studies may be needed even if its results are encouraging.
A promising development—but not yet a proven CPA treatment
Rezafungin is particularly interesting because it combines a different class of antifungal activity with practical once-weekly administration. The published case demonstrates that prolonged outpatient treatment is possible and may benefit an individual with difficult-to-treat CPA. Laboratory findings also confirm activity against a large and geographically diverse collection of Aspergillus isolates.
Nevertheless, rezafungin has not yet been proven effective for CPA. The results of the Phase 2 trial will provide the first structured evidence showing how patients respond over six months.
For now, rezafungin should be viewed as a promising experimental option for people with CPA who have limited alternatives, rather than an established replacement for azole treatment.
for people with CPA who have limited alternatives, rather than an established replacement for azole treatment.
Further information
-
- Rezafungin Phase 2 CPA trial – ClinicalTrials.gov
- Successful outpatient treatment with rezafungin for CPA – JAC-Antimicrobial Resistance
- Activity of rezafungin against Aspergillus species – ESCMID Global 2026 poster
- Olorofim: another antifungal being investigated for difficult-to-treat aspergillosis

Are all your medicines still helping? A guide to polypharmacy and medication reviews
Reviewed: 23 July 2026
People living with several long-term conditions often accumulate medicines gradually. One is prescribed for the original illness, another to prevent complications, and others to manage new conditions or treatment side effects.
Each decision may have made sense when it was made. Years later, however, someone may be taking tablets, inhalers, nebulised treatments, injections, supplements and over-the-counter products prescribed or recommended by several different professionals.
This is known as polypharmacy. It is not automatically a bad thing: several medicines may be necessary and beneficial. The important question is not simply how many medicines someone takes, but whether the complete treatment plan remains safe, manageable and appropriate for the life they are living now.
What does polypharmacy mean?
Polypharmacy means taking multiple medicines. Some definitions use a threshold such as five or more regular medicines, while ten or more is sometimes described as extensive polypharmacy. These numbers are useful for identifying people who may benefit from a review, but they do not tell us whether prescribing is good or bad.
There are two important forms:
- Appropriate polypharmacy: all the medicines have a clear purpose, provide worthwhile benefit and are being used safely.
- Problematic polypharmacy: the combination may cause more harm than benefit, some medicines are no longer needed, or the treatment routine has become unmanageable.
A person taking twelve well-chosen medicines may have appropriate polypharmacy. Someone taking four medicines that interact, duplicate one another or no longer meet their needs may have problematic polypharmacy.
How do medicine lists become so complicated?
Complex treatment plans rarely appear all at once. They grow over time.
This may happen because:
- different conditions are managed by different specialists;
- a medicine started during an illness or hospital admission is never reconsidered;
- a temporary treatment quietly becomes permanent;
- a new medicine is prescribed to manage the side effect of another;
- repeat prescriptions continue after the original reason has changed;
- guidelines for several individual diseases are combined without considering the total burden;
- over-the-counter medicines, vitamins and herbal products are not included in the main record;
- the patient’s priorities, health or ability to manage treatment change.
No single clinician may have done anything wrong. The problem is that each medicine can be considered separately while nobody examines the complete picture.
More medicines can mean more opportunities for harm
As the number of medicines increases, it becomes more difficult to predict their combined effect.
Potential problems include:
- side effects being mistaken for symptoms of the underlying illness;
- one medicine increasing or reducing the effect of another;
- several medicines contributing to fatigue, dizziness, confusion or falls;
- effects on the kidneys, liver, heart rhythm or blood pressure;
- duplicated treatment from different prescribers;
- complicated timing instructions that are difficult to follow;
- missed doses or accidental double dosing;
- monitoring tests not taking place at the right time;
- treatment consuming so much time and energy that quality of life suffers.
Older people may be particularly vulnerable because the way the body processes and removes medicines changes with age. Kidney or liver problems, frailty, low body weight and changes in nutrition can also alter how medicines affect someone.
However, problematic polypharmacy is not restricted to older people. Anyone with multiple conditions, several prescribers or a complicated treatment programme may benefit from a review.
When a side effect leads to another prescription
A prescribing cascade occurs when the side effect of one medicine is mistaken for a new medical condition and treated with another medicine.
For example, a medicine may cause ankle swelling, stomach symptoms, dizziness, coughing or sleep disturbance. If the original medicine is not considered as a possible cause, another treatment may be added.
Sometimes the additional medicine is entirely appropriate. But it is worth asking whether a new symptom appeared after a medicine was started or its dose changed.
A good medication review looks backwards as well as forwards:
What was happening when this medicine was started, and does that reason still apply?
Why this matters in aspergillosis
Antifungal medicines can interact with many commonly prescribed treatments.
Azole antifungals such as itraconazole, voriconazole, posaconazole and isavuconazole affect the enzymes the body uses to process other medicines. Other drugs can also raise or lower antifungal levels, sometimes substantially.
Depending on the particular combination, interactions may affect:
- antifungal effectiveness;
- liver function;
- heart rhythm;
- steroid exposure;
- cholesterol-lowering medicines;
- blood thinners;
- some antibiotics;
- medicines for sleep, pain, anxiety or mood;
- immunosuppressive medicines.
Some interactions can be managed by choosing a different medicine, adjusting a dose or carrying out additional monitoring. Others mean that two medicines should not be used together.
For people taking an azole antifungal, it is particularly important that every prescriber, pharmacist and dentist knows about it before recommending something new. This includes medicines bought without a prescription and herbal products.
Medicines include more than tablets
A complete review should include everything being used regularly or occasionally:
- prescription tablets and capsules;
- inhalers and nebulised medicines;
- creams, ointments and eye or ear drops;
- injections and biologic treatments;
- painkillers, antihistamines and indigestion remedies bought from a pharmacy or shop;
- vitamins, minerals and dietary supplements;
- herbal and complementary products;
- medicines kept “just in case” or taken only when needed.
Patients do not always think of an inhaler, cream or supplement as a medicine, but these products can still cause side effects or interactions.
What is a structured medication review?
A structured medication review is more than checking boxes on a repeat-prescription screen. It is a detailed conversation between the patient and a suitably qualified healthcare professional about the complete medication plan.
NHS England describes it as a review in which the clinician and patient work as equal partners to understand the benefits, risks and alternatives, guided by the person’s needs, preferences and circumstances.
For every medicine, the review should consider:
- Why was it originally prescribed?
- Is there still a clear reason to take it?
- Is it producing a benefit that matters to the patient?
- Could it be causing symptoms or side effects?
- Does it interact with anything else?
- Is the dose still appropriate for the person’s age, weight, kidney and liver function?
- Is the necessary monitoring taking place?
- Can the person use it correctly and take it at the required time?
- Does its likely future benefit justify its present burden?
- Could anything be simplified, changed or safely stopped?
A review may result in fewer medicines, but that is not its only possible outcome. It may identify an undertreated symptom, improve inhaler technique, change the timing of doses, arrange overdue monitoring or replace a medicine with a safer alternative.
Who should review the medicines?
For many people, the best starting point is their GP practice. A GP or clinical pharmacist can examine the full prescription record and consider all the person’s conditions together.
Other professionals may also be involved:
- Clinical pharmacists are particularly skilled in interactions, side effects, monitoring and simplifying complicated regimens.
- Community pharmacists can identify possible problems and help with medicine use, although major changes may need discussion with the prescriber.
- Hospital specialists should review medicines prescribed for conditions requiring specialist expertise.
- Specialist antifungal pharmacists or clinicians should be involved when changes might affect antifungal treatment.
- Respiratory nurses and physiotherapists can help assess inhalers, nebulised treatments and airway-clearance burden.
When several specialists are involved, one person should ideally coordinate the overall plan. A patient should not be left to decide which specialist’s medicine is least important.
When might a review be particularly useful?
Consider asking for a medication review when:
- you take several regular medicines;
- a new medicine is being added to an already complicated list;
- you have recently left hospital;
- more than one clinic is prescribing for you;
- your kidney or liver function has changed;
- you have developed unexplained fatigue, dizziness, falls, confusion, nausea or other symptoms;
- you are unsure why you still take something;
- the treatment timetable has become difficult to manage;
- you have stopped taking something but it remains on the repeat list;
- your health priorities or quality of life have changed;
- no one has reviewed the complete list recently.
Medication should also be reconciled after a hospital admission. Hospital teams may start, stop or change medicines, and those changes do not always transfer perfectly between hospital, GP and community-pharmacy records.
Preparing for a medication review
Before the appointment, make a list of everything you actually take—not only what appears on the repeat prescription.
Include:
- the medicine name and dose;
- how often you really take it;
- what you believe it is for;
- whether it seems to help;
- any side effects or practical difficulties;
- non-prescription and herbal products;
- medicines prescribed by hospitals or private services;
- anything you have stopped or use differently from the instructions.
If making a list is difficult, bring the medicine boxes, inhalers, bottles and supplements with you. This is sometimes called a “brown bag review”. Photographs of packaging can also help during a telephone or video consultation.
Be honest about missed doses or treatments you have chosen not to use. This is valuable safety information, not a test of whether you are a “good patient”. If a treatment does not fit into daily life, the prescriber needs to know.
Questions worth asking
- What is each medicine for?
- How will we know whether it is working?
- Which medicines are essential and which are optional?
- Could any of my symptoms be side effects?
- Do any of these medicines interact with my antifungal treatment?
- Do I still need the same dose?
- Are there blood tests, ECGs, blood-pressure checks or drug levels that I need?
- Could the timing or number of doses be simplified?
- If we stop something, how will it be reduced and what should I watch for?
- Who should I contact if symptoms return?
- Who is responsible for coordinating my overall medication plan?
Deprescribing does not mean withdrawing care
Deprescribing means the planned and supervised reduction or stopping of a medicine when its harms or burdens outweigh its likely benefits.
It should be a shared clinical decision—not an automatic attempt to cut the number of prescriptions and not a way of denying useful treatment.
Some medicines can be stopped straightforwardly. Others must be reduced gradually to prevent withdrawal effects or a dangerous return of the condition they control.
Corticosteroids are a particularly important example. Long-term systemic steroids must not be stopped suddenly because the body’s natural steroid production may have been suppressed. Some antidepressants, sedatives, opioid painkillers and other medicines may also require a carefully planned reduction.
Do not stop a prescribed medicine simply because you suspect it is unnecessary or causing a side effect. Discuss the concern with a pharmacist or prescriber and agree a safe plan.
The aim is a treatment plan that fits the person
A medication review is not only about pharmacology. It is also about daily life.
A treatment can be medically effective but still create problems if it takes hours to complete, causes intolerable side effects or prevents someone doing what matters to them. These burdens should be part of the decision alongside test results and clinical guidelines.
The central question is not:
“How can we remove as many medicines as possible?”
It is:
“Does every part of this treatment plan still have a worthwhile purpose for this particular person?”
Sometimes the answer will be to continue everything. Sometimes a dose can be reduced, monitoring improved or treatment simplified. Occasionally, a medicine that has been taken for years can be safely withdrawn.
What matters is that the complete medication list is reviewed rather than allowed to grow indefinitely—and that the person taking the medicines is fully involved in deciding what happens next.
Further information
- NHS England: Structured medication reviews and medicines optimisation
- NICE: Medicines optimisation
- NICE: Shared decision-making about medicines
- MHRA: Multiple medicines and reporting suspected side effects
This information is intended to support, not replace, discussions with your doctor, pharmacist or specialist team. Do not stop or change prescribed medicines without appropriate clinical advice.
When Coughing Becomes Socially Difficult
One reader described an experience that is rarely captured by scans or lung-function tests.
They noticed that meeting and talking with other people naturally changed their breathing. Deeper breaths, speaking and emotional excitement seemed to mobilise congestion, followed by a coughing episode. The physical need to cough then created anxiety about coughing in front of others.
This illustrates how several real processes can overlap:
Research has not established exactly how each part of this sequence operates in aspergillosis, so we should not pretend that one explanation fits everyone. The cough and mucus are nevertheless physical, while the social anxiety is also real. Each can intensify the other.
What may help?
The goal is not to suppress a cough that is needed to clear mucus. It is to make the episode safer, more manageable and less socially limiting.