

Margaret G: a long life with ABPA
Margaret wrote this account when she was 75. It looks back on decades of asthma, ABPA and other health problems, and on how diagnosis and care changed during her lifetime. The treatments and advice described are from that period, not current medical guidance.
I was often unwell as a child, with coughs and wheezing, though I was not diagnosed with asthma. In 1956, I had an episode of severe sinus congestion and brought up thick brown material. I recovered and thought little more of it at the time.
In 1962, my husband and I went to Nigeria to teach. The country and its people made a deep impression on us, but the years were also marked by political violence and civil war. During that period, I developed a worsening cough and became very ill. Local medical facilities were limited, and I was treated for asthma.
When we returned to the UK in 1968, I had a fever and a chest X-ray that raised concern about pneumonia, tuberculosis or cancer. A chest physician performed a bronchoscopy and removed brown material from my lungs. The laboratory identified aspergillosis. I was treated with positioning, physiotherapy and steroids. After weeks of coughing, I began bringing up thick plugs and could breathe more easily. I recovered and returned to family life.
Living with recurring symptoms
My consultant warned that aspergillosis could return. Over the following years, I had repeated coughs and episodes that I now understand may have been ABPA flare-ups. At the time, the condition was not well understood by many of the doctors I saw. I was often treated for infections, and the cause of my symptoms was not always recognised.
A second opinion at the Royal Brompton Hospital in 1990 changed things. Scans showed bronchiectasis and mucus plugs. I learned breathing and airway-clearance techniques and began long-term treatment. I felt that my illness was finally understood, and I was better able to get help when symptoms worsened.
In 1995, after several viral infections, I became very weak. During treatment, I injured both Achilles tendons. The following year, tests for a prolonged stomach illness led to another diagnosis: a rare leukaemia that affected my neutrophil count. I felt relatively well, so treatment for the leukaemia was postponed, but I learned to take feverish infections seriously and seek care promptly.
As I grew older, coughing became increasingly difficult to cope with. In 2010, a consultant prescribed itraconazole. I still coughed, but the episodes became less violent and prolonged.
Looking back
When I wrote this account, I was 75 and described my quality of life as good, despite fatigue, fragile skin, a croaky voice and poor sleep. I paced myself, walked when I could and valued the support of my husband and the care I had received from NHS staff.
I wondered whether different parts of my life—including illness, stress or exposure to bat droppings—might have contributed to my health problems, but I did not know the cause. I was grateful for the research and medical care that had helped me.
Margaret G

Peter K: choosing surgery for an aspergilloma
Peter shared this account in 2009, with an update in 2011. It describes his own experience and the decisions made with his doctors at that time. Treatment options and clinical practice may have changed since then.
A collapsed lung and a difficult recovery
In 1974, I was diagnosed with a large pneumothorax—a collapsed right lung. Attempts to reinflate it failed. After several weeks in hospital with a vacuum pump attached, I was transferred to Copenhagen University Hospital.
I had an operation, but complications followed. My blood seemed slow to clot, and I was re-operated on four times in one week. I received several blood transfusions and spent two weeks on a ventilator while the internal bleeding gradually stopped.
Recovery took a long time. I returned to work after three months, but it was more than a year before I felt physically back to normal.
I did not know that the surgery had left a small cavity in the upper lobe of my right lung. Apart from another spontaneous pneumothorax in my left lung—which was successfully treated with open-chest surgery in 1986—I had few symptoms for many years. I returned to exercise, travelled and worked long hours.
That changed in the summer of 2004.
A diagnosis of aspergilloma
I was working in California when I developed a cough and thick, greenish sputum. My GP and I thought it might be a seasonal allergy, but it became worse and the sputum gradually turned brown.
On Christmas Day, I coughed up fresh blood for the first time. My wife and I went to the local hospital. I had another episode while waiting to see a doctor, was sent home and told to see my GP the next morning. During the night, I coughed up blood twice more and returned to hospital.
I was admitted to an isolation room while doctors investigated possible tuberculosis. The tests were negative. I received intravenous antibiotics for several days and was then sent home.
After another episode in February 2005, I went straight to the respiratory specialist who had seen me in hospital. He suggested testing for Aspergillus. The test was positive, and I was diagnosed with an aspergilloma—a mass of fungal material in the cavity in my upper right lung. I was told that the cavity was likely related to my previous lung surgery.
I was 65 and had already been thinking about retiring or reducing my hours. My wife and I decided to leave California and return to Denmark. I continued working as a consultant and adviser, but with fewer hours and some international travel. I became an outpatient at a pulmonary infection department in Hillerød, north of Copenhagen.
I took antibiotics and itraconazole over a long period. By spring 2006, it seemed the infection had cleared, so I stopped the medication. Later that year, I began coughing up red sputum and restarted long-term itraconazole. I continued to have episodes of bleeding.
In autumn 2007, I travelled to Manchester to see Professor Denning. He explained that surgery would normally be considered, but the scarring from my earlier operations made it inadvisable in my case. If the bleeding became worse, he said, embolisation might be an option. My doctors in Hillerød had also discussed surgery but were concerned about the risks.
Despite continuing itraconazole, the episodes became more frequent. By late summer 2008, I was coughing up blood almost every night.
Weighing up an operation
I decided to consult a thoracic surgeon at the university hospital in Odense to understand how an operation might be done. He explained that he would consider keyhole surgery to remove the entire lobe containing the aspergilloma. He showed me a recording of a similar operation, with the patient’s permission.
After I returned to Hillerød, my respiratory specialist and I discussed the options. We concluded that, despite the risks, surgery was the best choice for me. My specialist referred me to Odense at my request.
The operation and recovery
I was admitted to hospital in Odense in November 2008. The operation took five hours. My blood-clotting problem returned, but the team used medicines that were available to control the bleeding. My family was told that the operation had been successful: the affected lobe had been removed without damage to the surrounding lung.
I later developed a serious bleeding ulcer in my duodenum, which was attributed to the stress of surgery. I lost a considerable amount of blood and needed a transfusion.
I was told that the cavity had developed a hard, almost bony wall, but that fungal filaments had penetrated it. The filaments were found to be dead, possibly because of the itraconazole. I was later told that the infection might have become invasive if surgery had been delayed.
Follow-up
Samples from the drains placed after surgery showed no Aspergillus. Blood tests a month later did show antibodies, which was disappointing. A CT scan showed nothing unexpected.
By March 2009, a further scan and blood tests were reassuring. My antibody level had almost returned to zero, and my doctor thought there was no fungus remaining in my chest after the operation.
Update: November 2011
It is now three years since my surgery. For the first two years, I had blood tests, X-rays and consultations every three months at Hillerød Hospital. These have now reduced to twice a year. My most recent tests showed no antibodies.
I am leading a normal life without restrictions. I continue to take part in outdoor activities and travel, mostly for pleasure and sometimes for work. I am increasingly confident that the infection has gone, and I feel lucky to have made the right decision for me.
I am grateful to the surgeon and doctors who cared for me. They were willing to explain the details and discuss the options, which helped me understand my situation and make my decision. I am also tremendously thankful to my wife, Gudrun, who supported me throughout.
Peter
Originally written in April 2009; update added in November 2011.

When symptoms remain difficult: keeping the conversation open

Ideas for clinicians when a patient has a diagnosis, but symptoms remain distressing or difficult to manage. This article grew out of an online meeting where people living with aspergillosis discussed how difficult it can be when symptoms remain troublesome and they feel their experience is not fully understood. The suggestions below draw on that patient discussion and published guidance; they are intended to support reflection, not to judge individual clinicians.
A patient may continue to struggle even when their diagnosis is known, investigations have been completed, or treatment has been tried. Sometimes there is no clearer explanation to offer, or no new treatment likely to make the symptoms go away.
That can be a difficult moment in a consultation. A patient may worry that they are not believed. A clinician may worry that discussing stress or mood will sound dismissive—or feel pressure to provide an answer that medicine does not yet have.
The conversation can still be useful. It can acknowledge the impact of symptoms, explain what is known and uncertain, and agree what happens next.
Start with the impact
Symptoms are only part of the patient’s experience. It also matters what they prevent, what they make harder, and what it costs the person to keep going.
A patient may still be working, socialising or caring for others, but need to rest afterwards or be unable to repeat the activity the following day. They may look well in the consultation while describing symptoms that disrupt sleep, concentration, relationships or daily routines.
Questions such as “What is hardest to manage at the moment?”, “What happens after you’ve pushed through?” or “What would you most like me to understand?” can help bring that impact into the conversation.
Acknowledging the impact does not require certainty about its cause. It shows the patient that their account has been heard.
Explain what is known and what remains uncertain
When tests do not reveal a new cause, patients may need a clear explanation of what has been considered, what the results show, and what they cannot tell us. Saying “I don’t have a better explanation today” can be more reassuring than offering a tentative explanation as if it were certain.
“I can see these symptoms are still affecting you. We haven’t found a new explanation in the tests we’ve done. That doesn’t mean I think nothing is wrong. Let’s talk about what we can do now and what should prompt us to review things.”
The wording will depend on the patient and the clinical situation. The aim is to make sure uncertainty does not sound like disbelief.
The General Medical Council’s Good medical practice asks doctors to listen, acknowledge patients’ concerns and experience, explain uncertainty, and encourage open dialogue about health. It also recognises the lasting impact a medical professional’s approach can have on a patient. NICE guidance on patient experience in adult NHS services similarly emphasises involving people in discussions about their care and respecting their needs and preferences.
Discuss mind–body effects without blame
Stress, sleep, mood and the demands of living with a long-term condition may affect how symptoms are experienced and managed. Physical symptoms can also cause stress, disrupt sleep and affect mood. These influences can interact.
Raising them need not suggest that symptoms are imaginary or “all in the mind.” A clinician might ask permission and explain why the topic could be relevant:
“Would it be okay if we also talked about sleep, stress and mood? These can interact with physical symptoms, and understanding that may give us more ways to support you.”
Patients may welcome this conversation, feel uncertain about it, or have previously felt dismissed when psychological factors were raised. Making space for their response—and continuing to consider their physical health—can help preserve trust.
Agree what happens next
Even when there is no new treatment to offer, the appointment can end with a shared plan. Depending on the situation, that might include:
- practical support for managing symptoms and their impact
- whether treatment, medication or other support should be reviewed
- what changes the patient should report or seek help for
- when to review the situation
- who the patient should contact if things change
A plan does not have to promise that symptoms will resolve. It gives both people a way to keep responding if they do not.
What does the research say about communication?
Research on persistent physical symptoms and symptoms without a complete medical explanation is relevant to these conversations, but it does not map perfectly onto every patient with an established diagnosis. It should inform the discussion, not define the person.
A 2022 systematic review examined communication interventions for symptoms often described in the literature as “medically unexplained.” It found the evidence was mixed and limited by differences in the interventions and the quality of studies. The authors recommended further development of communication approaches before more trials are undertaken. This means a conversation aid such as a patient-completed appointment note may be worth developing and evaluating, but should not be presented as a proven intervention. Read the review.
In a qualitative study, patients identified acknowledgement and validation, along with specific recommendations, as helpful parts of communication about persistent symptoms. Read the study. A clinical review by Husain and Chalder discusses assessment and management of persistent physical symptoms and emphasises that symptoms are real and can be distressing. Read the review.
Keep listening
Clinicians work within real limits, including short appointments, complex records and uncertainty about what might help. Patients may also find it hard to describe fluctuating or invisible symptoms, particularly if they have felt dismissed before.
Listening carefully, explaining decisions and making the next step clear cannot guarantee agreement or solve every problem. But they can help keep the relationship intact when there is no easy answer. The aim is for the patient to leave knowing that their concerns have been taken seriously, what remains uncertain, and what will happen next.
This article offers general communication ideas, not clinical guidance. It draws on patient discussion and published resources; it should be reviewed by a clinician before publication.
Further reading
- GMC: Good medical practice — Patients, partnership and communication
- NICE: Patient experience in adult NHS services
- Husain & Chalder (2021): Medically unexplained symptoms: assessment and management
- Byrne et al. (2022): Communication interventions for medically unexplained symptom conditions in general practice
- Anastasides et al. (2019): Helpful ways providers can communicate about persistent medically unexplained physical symptoms
For patients, families and friends: Read our guide to
talking to friends and family about aspergillosis,
which explores how fluctuating symptoms can affect everyday life and what support can help.

Thursday Sessions: When symptoms aren’t believed: being heard when tests don’t explain everything
Reflections from patient discussions about living with chronic illness
In a recent patient discussion, one person recalled being told by a specialist that their symptoms were psychosomatic. Their GP listened, supported them and helped them continue seeking an explanation. The specialist’s comment stayed with them. It made it harder to speak openly about symptoms and left them wondering whether other clinicians would also dismiss what they were experiencing. In time, they received treatment for aspergillosis.
Their experience prompted others in the group to share how difficult it can be when symptoms are not obvious to the people around you. Someone may manage a social event, get through a work meeting or care for a family member, yet feel exhausted or unwell afterwards. To other people, they may look much the same as usual. The effort it took—and the recovery that followed—may be invisible.
Several people recognised the feeling of not being believed. They spoke about trying to describe symptoms to clinicians, family or colleagues and feeling that their experience was doubted or minimised. For some, the difficulty was not only coping with symptoms. It was also having to explain, repeatedly, why those symptoms mattered.
When there isn’t an immediate explanation
Symptoms do not always fit neatly into a test result or a clear diagnosis. Investigations may take time, results may be inconclusive, and different health problems can overlap. A clinician may not know the cause straight away.
That uncertainty can be hard for everyone. But “we haven’t found an explanation yet” is not the same as “nothing is wrong.” A person can be genuinely unwell even when the reason is not yet clear.
The recollection is one person’s experience, not a judgement about every clinician or every use of the word psychosomatic. It shows how a label can be heard, though: not as one possible part of a careful discussion, but as a conclusion that closes the door on further listening.
Mind and body are connected—but symptoms still deserve attention
Stress, anxiety and low mood can affect the body and can make symptoms harder to manage. Physical illness can also affect emotional wellbeing. These things can be true at the same time.
Recognising that connection should not mean assuming that symptoms are “just stress” or that a person’s account is unreliable. A psychological explanation should not be used to dismiss symptoms without taking the person’s concerns seriously and considering what else may need attention. A clinician can acknowledge the effects of stress while still asking what has changed, what investigations are appropriate and what support might help.
Being listened to does not require a clinician to have an immediate answer. It means being treated with respect while the possibilities are considered and the next steps are discussed.
The cost of appearing well
People in the discussion described how much can be hidden from view. A person might manage a visit or a meeting, then find their energy gone. They may look fine while struggling to concentrate, losing their train of thought, or trying to conceal the effects of illness or medication. A short outing can involve planning where to sit, how far to walk and how to get home.
A good day can make it tempting to do everything at once—to take the stairs, stay longer or catch up on what has been postponed. But a person’s ability to do something once does not show how often they can do it, or what it costs them afterwards.
This can be difficult for family members and colleagues to understand, especially if they remember the person before illness changed their capacity. It can also be difficult for the person who is ill: asking for help, changing a plan or needing to rest may feel like letting others down.
What helps people feel heard?
There is no perfect phrase that guarantees understanding. But patients and clinicians can make space for a clearer conversation.
A patient might find it useful to explain:
- what has changed and when it began
- how symptoms affect daily activities, work or sleep
- whether the difficulty varies over time
- what happens after exertion or a demanding day
- what they are most worried about, and what help they are asking for
It may help to write down a few key points before an appointment, especially if concentration or memory is affected. If someone feels their concern has not been understood, they could try saying: “I understand that we don’t have an explanation yet, but these symptoms are affecting my life. Can we talk about what happens next?”
Family members and colleagues do not need to diagnose or solve the problem. Listening without immediately challenging the account, asking what would make the day easier, and accepting that someone may need to stop or change plans can make a real difference.
The importance of being believed
The patient discussion did not resolve why every person had experienced their symptoms, or what should happen in each individual case. What it offered was recognition: people understood how exhausting it can be to live with symptoms and also try to convince others that they are real.
Being believed does not mean that every explanation is already known. It means that a person’s experience is taken seriously, uncertainty is acknowledged, and the conversation remains open.
This article draws on anonymised recollections from patient discussions. It reflects shared experiences and is not a clinical account of any individual’s care.
Further information
- Information and support for people affected by aspergillosis
- NAC online meetings and community support
- How to contact or register with a GP
- Comments for clincians
For healthcare professionals: Read our companion article on
keeping the conversation open when symptoms remain difficult.

ABPA Diagnosis: Why It Is Not Just an IgE Test—and How a New Score May Help
If you have asthma or bronchiectasis, you may have been tested for allergic bronchopulmonary aspergillosis (ABPA). It is common to hear that ABPA is diagnosed using an IgE blood test, but the reality is more complicated.
A high IgE result can support a diagnosis of ABPA, but it does not prove that you have ABPA.
Specialists usually need to bring together several different pieces of information, including symptoms, blood tests, scans and your medical history.
What is ABPA?
ABPA is an allergic lung condition caused by an exaggerated immune response to Aspergillus, a common mould found in the environment.
It most often affects people with asthma or cystic fibrosis, but it can also occur in people with bronchiectasis and other chronic airway conditions.
The immune response can cause airway inflammation, mucus plugging and, over time, bronchiectasis or worsening lung damage.
Why is ABPA difficult to diagnose?
Many of the symptoms of ABPA are also common in asthma, bronchiectasis and respiratory infections. These may include:
- cough;
- wheezing;
- breathlessness;
- increased mucus;
- chest tightness;
- tiredness; and
- repeated flare-ups.
Blood-test results can also overlap with other allergic and inflammatory conditions. A person may have a high IgE level without having ABPA, or may have ABPA even when not every test is strongly abnormal.
What does IgE tell doctors?
IgE is an antibody involved in allergic reactions. Doctors may measure:
- total IgE, which reflects the overall amount of IgE in the blood; and
- Aspergillus-specific IgE, which indicates sensitisation to Aspergillus.
These tests are important, but they answer slightly different questions.
Aspergillus-specific IgE can show that the immune system reacts to Aspergillus. This is called sensitisation. Sensitisation does not always mean that a person has ABPA.
Total IgE may be raised in ABPA, but it can also be raised because of other allergic conditions, asthma, eczema or other causes. Levels can also change over time and may be affected by treatment.
Other information used to diagnose ABPA
Depending on the situation, clinicians may consider:
Symptoms and medical history
Doctors may look for worsening asthma, repeated flare-ups, difficulty clearing mucus, brownish mucus plugs or symptoms that do not behave as expected with usual asthma treatment.
Aspergillus-specific IgE
This helps show whether the immune system is sensitised to Aspergillus. It is an important part of assessment but does not diagnose ABPA by itself.
Aspergillus-specific IgG
IgG or precipitins may provide additional information about the immune response to Aspergillus. These tests are used differently from IgE tests and may be helpful when considered alongside other findings.
Eosinophils
Eosinophils are a type of white blood cell involved in allergic inflammation. A raised eosinophil count may support the diagnosis, but eosinophils can also be raised in asthma, other allergic conditions and several other diseases.
Chest imaging
A chest X-ray or CT scan may show features such as bronchiectasis, mucus plugging or changes that support an ABPA diagnosis.
High-attenuation mucus on a CT scan can be particularly helpful when present, but not everyone with ABPA has this feature.
Changes over time
Doctors may compare blood tests, symptoms and scans over time. A pattern of worsening symptoms, increasing inflammation and changing imaging may be more informative than one isolated result.
A new approach to combining ABPA test results
A recent study examined whether a weighted diagnostic score could improve the way ABPA test results are combined.
The idea is that different diagnostic findings do not necessarily provide the same amount of information. A weighted approach gives greater importance to findings that are more strongly associated with ABPA, rather than treating every result as equally informative.
This may eventually help specialists assess people whose symptoms, blood tests and scans do not fit neatly into one category.
However, this approach is still research. It is not currently a routine clinical test and it does not replace the existing international guidance for diagnosing ABPA.
Read the research paper on PubMed
Why specialist assessment can be important
ABPA can sometimes be diagnosed and managed outside a specialist centre, but difficult or borderline cases may require specialist input.
This is because the diagnosis involves interpreting several imperfect pieces of evidence together. A specialist may need to decide whether a result represents:
- Aspergillus sensitisation;
- ABPA;
- severe asthma with fungal sensitisation;
- another allergic or inflammatory condition;
- bronchiectasis with mucus plugging; or
- another form of aspergillosis.
Specialist review may be especially helpful when symptoms continue despite treatment, when test results disagree, when scans show extensive mucus plugging or bronchiectasis, or when repeated courses of steroids are being considered.
Questions you could ask your doctor
If you have been told that your IgE is high or that you may have ABPA, you could ask:
- Does my result show sensitisation or does it support a diagnosis of ABPA?
- What do my Aspergillus-specific IgE and IgG results mean?
- Have my eosinophils been measured?
- Do my CT or X-ray findings support ABPA?
- Could another condition explain these results?
- Would specialist advice be helpful?
The important message
ABPA is not diagnosed by IgE alone.
IgE is an important part of the assessment, but doctors usually need to consider it alongside symptoms, asthma or bronchiectasis, eosinophils, other Aspergillus blood tests, chest imaging and changes over time.
New research is exploring whether these findings can be combined more accurately. This may eventually make ABPA diagnosis more consistent, particularly for people whose results are difficult to interpret.
For now, if you have been told that your IgE is high, it is reasonable to ask what the result means in the context of your other tests and symptoms.
This article is for information only and is not a substitute for medical advice. Do not start, stop or change treatment without discussing it with your healthcare team.
Further information
- Allergic bronchopulmonary aspergillosis (ABPA)
- Diagnosis of aspergillosis
- Severe asthma with fungal sensitisation

This Week in Aspergillosis Research: Monitoring CPA, Switching ABPA Biologics and Understanding Antifungal Immunity
Research published this week explores how doctors monitor chronic pulmonary aspergillosis, how difficult-to-treat ABPA may be managed, and how the immune system recognises fungi.
As always, these studies add to the evidence base but do not necessarily change treatment immediately.
Monitoring chronic pulmonary aspergillosis using Aspergillus IgG
A study in Chest examined how anti-Aspergillus IgG blood-test results change over time in people with chronic pulmonary aspergillosis (CPA).
Anti-Aspergillus IgG is commonly used as part of the assessment for CPA. It may also help clinicians monitor a patient, but interpreting changes can be difficult. A result may be influenced by how long someone has had the disease, when treatment started and how the disease is progressing.
The researchers looked at “time-normalised” IgG measurements. In simple terms, this means considering the antibody result alongside the length of time since diagnosis or treatment, rather than interpreting one result in isolation.
This approach may eventually help clinicians identify patterns associated with improvement, stability or progression. However, it is not a replacement for reviewing symptoms, scans, lung function and other test results together.
The study is particularly relevant because CPA often requires long-term follow-up, and there is currently no single blood test that can reliably describe everything happening in the lungs.
Switching biologics in difficult-to-treat ABPA
A case report describes the treatment of a person with refractory allergic bronchopulmonary aspergillosis (ABPA), where treatment remained difficult despite several approaches.
ABPA is driven by an exaggerated immune response to Aspergillus in the airways. Treatment may involve corticosteroids, antifungal medication and, in some cases, biologic medicines that target specific parts of the allergic or inflammatory response.
The report focuses on the selection, discontinuation and switching of biologics. It illustrates how treatment decisions may need to be adjusted when a medicine does not provide enough benefit, causes problems, or is no longer the best option for an individual patient.
This is a case report, so it cannot show that one biologic is generally better than another. It does, however, reflect the increasingly individualised nature of ABPA treatment. Decisions may depend on asthma control, eosinophil levels, exacerbations, steroid requirements, side effects and other health conditions.
Patients should not stop or switch biologic treatment without discussing it with their clinical team.
How the immune system recognises fungal cell walls
A review in Virulence examines how the immune system detects the cell walls of human fungal pathogens.
Fungal cell walls contain structures such as β-glucans, chitin and mannans. These can be detected by specialised immune receptors. The resulting immune response may help the body control the fungus, but it can also contribute to inflammation or tissue damage.
This is relevant to aspergillosis because the immune response is central to the different forms of disease. In ABPA, the immune response is excessive and allergic. In chronic disease, the relationship between the fungus, damaged airways and the immune system is more complex. In invasive aspergillosis, weakened or disrupted immune defences may allow the fungus to grow beyond the airways.
The review is not a treatment trial, but it helps explain why exposure to the same environmental fungus does not produce the same outcome in everyone.
Other research this week
Aspergillus flavus and antifungal susceptibility
Researchers in Cameroon examined the genetic diversity and antifungal susceptibility of Aspergillus flavus collected from different environmental settings, including soil, air, crops and clinical samples.
Aspergillus flavus is an important cause of invasive aspergillosis, particularly in some parts of the world. Understanding how strains differ may help explain regional patterns of disease and antifungal resistance.
This was a geographically focused study, so the findings cannot automatically be applied to every country. It nevertheless reinforces the importance of local surveillance and susceptibility testing when resistant infection is suspected.
Amphotericin B in invasive aspergillosis
A multicentre observational study from China examined amphotericin B colloidal dispersion in people with invasive aspergillosis and haematological disease.
The study provides real-world information about the use of this formulation in a group at high risk from invasive fungal infection. However, it concerns hospital-based treatment of invasive aspergillosis and should not be confused with treatment decisions for ABPA or CPA.
The choice of antifungal depends on the type of aspergillosis, the patient’s other illnesses, kidney and liver function, drug interactions, susceptibility results and previous treatment.
New diagnostic criteria for invasive aspergillosis in COPD
A recently published international study proposes diagnostic criteria for invasive pulmonary aspergillosis in people with COPD.
Invasive aspergillosis can be difficult to recognise in COPD because symptoms and scan findings may resemble a severe bacterial exacerbation or another lung problem. The authors propose combining the patient’s risk factors, imaging and results from more than one Aspergillus test.
These criteria are intended to support clinical diagnosis and research. They do not mean that a positive Aspergillus test alone proves invasive disease. Aspergillus can sometimes be detected in damaged or colonised airways without causing invasive infection.
What does this mean for patients?
The main theme this week is the move towards more individualised diagnosis and treatment.
- interpreting CPA antibody results more intelligently over time;
- tailoring ABPA treatment when the first approach is not sufficient;
- understanding why immune responses to fungi differ between people;
- monitoring antifungal resistance in different regions; and
- improving the diagnosis of invasive aspergillosis in people with underlying lung disease.
None of these studies means that patients should change treatment themselves. They show how research is gradually improving the information available to clinicians when making difficult decisions.
This article summarises early or newly published research. It is for information only and is not a substitute for medical advice.

Aspergillosis and Diet: Managing Weight Loss, Poor Appetite and Food Avoidance

For: patients, carers, general practitioners, specialist nurses and other non-specialists
Last reviewed: 22 September 2026
Important: This page provides general information and does not replace advice from your own clinical team.
Key points
- Eating difficulties can occur in people with aspergillosis, particularly chronic pulmonary aspergillosis (CPA) and other chronic lung conditions.
- Breathlessness, coughing, fatigue, reflux, nausea, altered taste and medicine side effects can all make eating difficult.
- Some people gradually avoid more and more foods because they believe these worsen mucus, reflux or fungal disease.
- The immediate nutritional priority is often enough energy, protein and fluids—not a perfect diet.
- Small, frequent meals and nourishing drinks may be easier than three large meals.
- Unplanned weight loss, persistent nausea, reflux or a very restricted diet should be discussed with a healthcare professional or dietitian.
Why eating can become difficult
Many people living with aspergillosis find that eating becomes harder than it used to be. This may be particularly important in chronic pulmonary aspergillosis, where weight loss, fatigue and poor general health can occur.
Several problems may overlap:
- Breathing takes more effort and may increase energy needs.
- Coughing or breathlessness can interrupt meals.
- Fatigue can make shopping, cooking and eating feel exhausting.
- Chronic inflammation can reduce appetite and contribute to muscle loss.
- Antifungal medicines and other treatments may cause nausea, indigestion, altered taste or poor appetite.
- Reflux, bloating or early fullness may make even small meals uncomfortable.
This can create a difficult cycle: eating becomes unpleasant, food intake falls, weight and strength decrease, and eating then becomes even more difficult.
Who is most likely to be affected?
Nutritional problems can affect anyone with a long-term illness, but they may be more likely in people with:
- chronic pulmonary aspergillosis
- bronchiectasis, COPD or previous tuberculosis
- long-term fatigue, breathlessness or coughing
- persistent nausea or reflux
- recent unplanned weight loss
- side effects from antifungal or other medicines
- anxiety around eating because meals repeatedly trigger symptoms
People with ABPA may also experience eating difficulties. Steroid treatment, asthma symptoms, reflux, medicine side effects and changes in appetite can all affect diet.
How eating difficulties may feel
People do not always describe the problem as a nutrition issue. They may say:
- “I get full after a few mouthfuls.”
- “I cannot face a proper meal.”
- “Eating makes me cough.”
- “Food feels uncomfortable.”
- “Some foods seem to sit badly.”
- “I only eat a few safe foods now.”
These experiences may reflect a combination of breathlessness, reflux, medicine effects, fatigue and learned food avoidance—not a lack of willpower.
When eating becomes very restricted
Some people gradually reduce their diet because certain foods seem safer or easier to manage. This may involve avoiding dairy products, sweet foods, bread, meat, acidic foods or anything associated with a previous unpleasant episode.
Sometimes there is a genuine reason to avoid a particular food. For example, reflux may be worsened by certain foods, or dry and crumbly foods may trigger coughing. However, repeated difficult experiences can lead to over-restriction, where more food groups are removed than necessary.
A very narrow diet can result in:
- weight loss
- loss of muscle
- greater weakness and fatigue
- nutritional deficiencies
- slower recovery from illness
- increased anxiety around food
The aim is usually to adapt food so that it is easier and more comfortable to eat, rather than removing whole food groups without a clear reason.
Could reflux or stomach symptoms be contributing?
Yes. Nausea, reflux, bloating, early fullness and abdominal discomfort can all reduce appetite. Reflux may also irritate the throat and contribute to coughing, throat-clearing or chest discomfort around meals.
Possible contributors include:
- medicine side effects
- gastro-oesophageal reflux disease
- reduced activity and chronic illness
- constipation
- an unrelated digestive condition
If eating repeatedly causes nausea, upper abdominal discomfort or reflux, this should be treated as a symptom requiring review rather than simply a dietary preference.
Practical ways to make eating easier
Try little and often
Five or six small eating opportunities may be easier than three large meals. This could include a small breakfast, snack, light lunch, nourishing drink, evening meal and supper snack.
Choose easier foods
Soft and moist foods are often easier than dry, chewy or crumbly foods. Examples include:
- porridge
- yoghurt
- custard or rice pudding
- mashed potato with added butter or cheese
- scrambled eggs
- soup with cream or grated cheese
- stews, casseroles and sauced dishes
Use drinks as nutrition
Some people find nourishing drinks easier than solid food. Options may include milk-based drinks, smoothies, milkshakes, fortified hot drinks or prescribed oral nutritional supplements.
Rest before meals
If fatigue or breathlessness are major barriers, try eating after a period of rest rather than immediately after exertion. Some people find breakfast or lunch easier than an evening meal.
Sit upright
Sitting upright while eating and remaining upright afterwards may help when reflux, coughing or chest discomfort are problems.
Eat slowly
Small mouthfuls, pauses and a slower pace may make eating more manageable. There is no need to finish a meal quickly.
Supporting weight and muscle
When weight maintenance is difficult, it may help to increase the energy and protein content of foods that are already tolerated.
- Add butter, cream, cheese, yoghurt, milk powder or olive oil where suitable.
- Choose full-fat products rather than reduced-fat versions if weight loss is a concern.
- Add grated cheese to soup, mashed potato, eggs or vegetables.
- Make porridge with milk rather than water.
- Keep easy snacks available, such as yoghurt, cheese and crackers, hummus, custard or rice pudding.
Protein helps preserve muscle. Useful sources include milk, yoghurt, cheese, eggs, meat, fish, poultry, beans, lentils and suitable nut products.
If food alone is not enough, a doctor or dietitian may suggest oral nutritional supplements. These are often taken between meals rather than instead of meals.
Food and antifungal medicines
Some medicines can affect appetite, taste, digestion or bowel function. If nausea, altered taste or poor appetite began after a medicine was started or changed, discuss this with the prescribing team.
Food can also affect how some medicines are absorbed. For example:
- Itraconazole capsules are generally taken with or just after food, while itraconazole liquid is generally taken on an empty stomach.
- Voriconazole is usually taken on an empty stomach.
- Some medicines interact with antacids or acid-suppressing medicines.
Formulations and instructions can differ. Follow the advice supplied with your prescription and ask a pharmacist or clinical team if you are unsure.
Common diet myths
There is no special diet that treats aspergillosis. For information about dairy, sugar, anti-fungal diets, Candida diets and other common claims, read Diet and Aspergillosis: What Helps, What Doesn’t, and What Matters Most.
When to seek medical advice
Speak to your doctor, specialist team or dietitian if you have:
- ongoing unplanned weight loss
- difficulty eating most days
- a very narrow diet
- persistent nausea, reflux, bloating or abdominal discomfort
- increasing weakness or fatigue
- concerns that medicines are affecting appetite or digestion
Ask for urgent medical advice if you are becoming dehydrated, vomiting repeatedly, unable to keep food or fluids down, losing weight rapidly or developing difficulty swallowing.
Related information
- Diet and Aspergillosis – common diet myths and what the evidence shows.
- Airways mucus and aspergillosis – why mucus becomes thick or difficult to clear.
- Loosen and clear mucus – practical airway-clearance advice.
References and further reading
- Carter C, Muldoon EG, Kosmidis C. Chronic pulmonary aspergillosis – a guide for the general physician. PubMed
- Roboubi A, et al. Allergic bronchopulmonary aspergillosis. PubMed
- British Dietetic Association. Spotting and treating malnutrition. BDA resource
- BAPEN. Food first and food enrichment. BAPEN resource
- NHS. Heartburn and acid reflux. NHS advice
- Manchester University NHS Foundation Trust, National Aspergillosis Centre. Patient information: Itraconazole. NAC information
- Manchester University NHS Foundation Trust, National Aspergillosis Centre. Patient information: Voriconazole. NAC information
- Balfour-Lynn IM. Milk, mucus and myths. Archives of Disease in Childhood

Diet and Aspergillosis: What Helps, What Doesn’t, and What Matters Most
Last reviewed: 22 Sept 2026
Many people living with aspergillosis ask whether diet can help “fight” the fungus, reduce symptoms, or improve recovery. This is completely understandable, particularly given the large amount of advice online suggesting that certain foods, supplements, or diets can control fungal disease.
This article explains what current evidence shows, what diet can and cannot do, and where it genuinely matters for people living with aspergillosis.
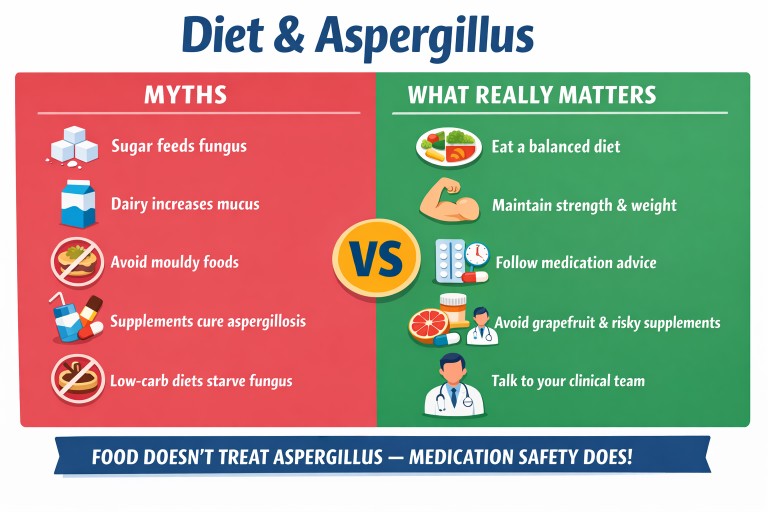
Core principle: Aspergillus-related disease is driven by what we breathe in and how the body responds — not by what we eat.
Contents
- Key points
- What do we mean by “no evidence”?
- How Aspergillus disease develops
- The role of airways, mucus and lung structure
- Immune response and inflammation
- Can food treat Aspergillus?
- Diet and ABPA (allergic disease)
- Allergy vs infection: why diet is often misunderstood
- Diet and CPA (chronic infection)
- Why nutrition still matters
- Steroids and diet
- Diet and antifungal medication
- Checking food–drug interactions
- Common diet myths (and why they persist)
- A practical, evidence-based approach
- When to seek help
- References
Key points
- There is no diet that treats aspergillosis.
- Aspergillus-related disease develops through inhalation of spores, changes in the lungs, and immune responses.
- Diet does not control Aspergillus growth in the lungs.
- Diet still matters for strength, weight, recovery, and treatment safety.
- Food can affect how medicines are absorbed and metabolised.
- Many popular online diet claims are based on misunderstood science, oversimplification, or marketing.
What do we mean by “no evidence”?
When this article says there is “no evidence” or “no strong evidence”, this does not mean that we are simply waiting for proof to arrive.
In most cases, it means one of two things:
- the idea has been studied and has not been shown to help real patients, or
- there is only laboratory or theoretical evidence, which does not translate into benefit in real-world disease
For example, fungi can grow in sugar-rich laboratory conditions. That does not mean eating sugar feeds Aspergillus in the lungs. The body tightly regulates blood glucose, and lung disease is far more complex than a laboratory culture dish.
Key message: when clinicians say there is “no evidence”, they usually mean an approach is unlikely to work in practice, not that it is a promising treatment that just has not been tested yet.
How Aspergillus disease develops
Aspergillus is a common environmental mould. People are exposed by breathing in microscopic spores from the air. Most people clear these spores without any problem.
Whether disease develops depends on the interaction between:
- the condition of the lungs
- how well mucus is cleared
- the immune response
In healthy lungs, inhaled spores are trapped in mucus, moved out of the airways, and removed by immune cells. When this system is disrupted, Aspergillus may persist or trigger inflammation. This is described in clinical reviews of pulmonary aspergillosis such as Kosmidis & Denning, 2015.
This process takes place in the respiratory system and is driven by inhalation — not diet.
The role of airways, mucus and lung structure
The lungs have several important defence systems. These include mucus, cilia (tiny hair-like structures that move mucus), and immune cells. Together, they help remove inhaled particles and organisms.
In conditions such as asthma, bronchiectasis, chronic obstructive pulmonary disease (COPD), or other chronic lung diseases:
- mucus may become thicker or harder to clear
- airways may be damaged or widened
- normal clearance may be less effective
This can make it easier for Aspergillus to remain in the lungs. In some people this contributes to allergic disease. In others, especially where there is structural damage, it can contribute to chronic infection.
These airway and lung-structure problems are not altered by avoiding particular foods.
Immune response and inflammation
In many people, particularly those with allergic forms of Aspergillus disease, symptoms are driven more by the immune system than by direct tissue invasion from the fungus.
For example, in allergic bronchopulmonary aspergillosis (ABPA), the body mounts an exaggerated allergic response to Aspergillus. This typically involves:
- raised IgE antibodies
- eosinophilic inflammation
- airway swelling and mucus production
Reviews of ABPA describe these immune processes in more detail, including the overlap with asthma and cystic fibrosis-related airway disease, for example Knutsen & Slavin, ABPA review.
These immune pathways are complex and are not controlled by specific foods.
Can food treat Aspergillus?
No specific food has been shown to treat Aspergillus-related lung disease.
You may come across claims about garlic, turmeric, coconut oil, probiotics, herbs, or “anti-fungal” foods. Some of these have shown antifungal effects in laboratory settings, but there is no reliable clinical evidence that eating them improves aspergillosis outcomes.
This is because:
- food is processed in the digestive system, not the lungs
- active compounds may not reach the lungs in useful amounts
- the biology of lung disease is much more complex than simple fungal growth in a dish
Diet can support the body, but it is not a treatment for Aspergillus disease.
Diet and ABPA (allergic disease)
In ABPA, the main problem is an allergic or immune reaction to Aspergillus. Diet does not switch that reaction on or off.
That means:
- food does not “feed” ABPA
- there is no evidence that an “anti-fungal diet” controls ABPA
- restrictive diets do not treat the underlying immune process
However, diet can become more important because many patients with ABPA are treated with prednisolone or other corticosteroids. These medicines can affect appetite, weight, blood sugar, and bone health. NHS information on prednisolone describes common effects such as weight gain, increased appetite, and longer-term bone risks: NHS Prednisolone guidance.
So in ABPA, diet often matters more in relation to treatment effects than in relation to the fungal trigger itself.
Allergy vs infection: why diet is often misunderstood
Many patients understandably ask whether a certain food might be “triggering” symptoms. This can be confusing because aspergillosis includes both allergic and infectious forms.
What matters here is the route of exposure:
- Aspergillus-related lung disease is driven by inhaled spores
- food enters the body through the digestive tract
Symptoms that seem to occur after eating may actually relate to:
- acid reflux
- throat irritation
- airway sensitivity
- coincidental fluctuation in symptoms
These may be real and troublesome, but they are not the same thing as diet directly driving Aspergillus disease.
Key message: Aspergillus-related lung symptoms are driven by what you breathe in and how your immune system responds — not by what you eat.
Diet and CPA (chronic infection)
Chronic pulmonary aspergillosis (CPA) is different from ABPA. CPA tends to occur in lungs that are already damaged or structurally abnormal, for example after tuberculosis, with bronchiectasis, or with COPD.
In CPA, the key issue is not food intake but the presence of abnormal lung tissue where Aspergillus can persist. This broader clinical picture is outlined in reviews such as Kosmidis & Denning, 2015.
Diet does not alter fungal growth directly, but it can matter because some people with CPA experience:
- weight loss
- fatigue
- low appetite
- reduced physical strength
In CPA, diet is therefore mainly about maintaining strength, resilience, and recovery — not about “starving” the fungus.
Why nutrition still matters
Although diet does not treat Aspergillus directly, nutrition still matters a great deal. Good nutrition supports the whole body, including the respiratory system.
Good nutrition can help support:
- muscle strength, including the muscles used for breathing
- energy levels
- general immune function
- recovery from illness and treatment
Poor nutrition, by contrast, can contribute to:
- tiredness
- lower resilience
- reduced strength
- slower recovery
This is one reason why very restrictive diets can be unhelpful, especially for patients already coping with chronic disease, breathlessness, or weight loss.
Steroids and diet
For patients taking corticosteroids such as prednisolone, diet becomes particularly relevant.
Important issues can include:
- increased appetite
- weight gain
- raised blood sugar
- fluid retention
- longer-term bone health
From a practical point of view, this is one of the strongest reasons to think carefully about diet in aspergillosis care. Here, diet is not being used to treat the fungus; it is helping patients cope with the effects of treatment and maintain overall health.
For longer-term steroid use, adequate calcium intake and attention to bone health may also be important. This is particularly relevant for people already at risk of osteoporosis.
Diet and antifungal medication
The clearest and most important direct link between diet and aspergillosis care is through medication.
Food can affect how medicines are absorbed, broken down, or cleared from the body.
Food–drug interactions
Some foods and drinks affect enzymes in the liver that metabolise drugs. A well-known example is grapefruit, which can interfere with CYP3A4 and change drug levels in the body.
Taking antifungals correctly
Some antifungal medicines are affected by food. For example, voriconazole is usually taken on an empty stomach so that absorption is more reliable. This is described in professional guidance such as the British National Formulary (BNF).
Supplements and herbal products
Supplements are often marketed as “natural”, but they can still interact with prescription medicines. Some herbal products may alter drug metabolism and therefore affect antifungal treatment.
Key message: diet rarely affects Aspergillus directly, but it can be very important in how your medicines work.
Checking food–drug interactions
Reliable sources for checking medicine and food interactions include:
- British National Formulary (BNF)
- patient information leaflets supplied with medicines
- Patient.info interaction checker
It is also important to understand the limits of specialist tools. Drug-interaction tools designed specifically for antifungals are very useful for drug–drug interactions, but they do not usually include food interactions in a comprehensive way.
The safest source of advice remains your pharmacist or clinical team.
Common diet myths (and why they persist)
Many people with aspergillosis come across strong claims online about diet and fungal disease. These often sound convincing, especially when symptoms are difficult to control and people understandably want something practical they can do.
However, most of these claims are based on misunderstandings of biology, laboratory research taken out of context, or commercial promotion.
Below are some of the most common myths, along with what current evidence suggests.
“Sugar feeds fungus”
This is one of the most common claims.
It comes from the fact that fungi can grow in sugar-rich laboratory conditions. However, this does not reflect what happens in the human body.
- blood sugar is tightly regulated
- Aspergillus in the lungs is not directly exposed to dietary sugar in the way people often imagine
- there are no clinical studies showing that reducing dietary sugar improves aspergillosis outcomes
Why it persists: it sounds intuitive, it is easy to repeat, and it fits with heavily marketed “anti-fungal” diet programmes.
“Milk and dairy increase mucus”
This is a very common concern in respiratory disease generally.
Research does not show that dairy increases mucus production in the lungs. Some people notice a thicker or coated feeling in the mouth and throat after milk, but that is different from producing more mucus in the airways.
- no good evidence of increased lung mucus
- no evidence that dairy worsens Aspergillus disease itself
Why it persists: the mouth and throat sensation after dairy can easily be mistaken for a lung effect.
“Yeast in food causes fungal infection”
Foods such as bread or fermented products may contain yeast, but yeast used in food is not the same thing as Aspergillus.
- food yeast and Aspergillus are different organisms
- Aspergillus-related lung disease is linked to inhalation of environmental spores, not eating yeast-containing foods
Why it persists: the word “fungus” is used broadly, which can blur important differences between very different organisms.
“Avoid foods made with mould”
Some patients are advised online to avoid blue cheese, mushrooms, or other foods associated with moulds.
There is no good evidence that eating these foods changes Aspergillosis in the lungs.
- the digestive and respiratory systems are separate
- food moulds are not the same thing as inhaled environmental Aspergillus exposure
Why it persists: when a disease involves mould, it feels logical to avoid all mould-associated foods, even though the biology does not support that approach.
“Low-carb or ketogenic diets can starve the fungus”
This idea grows out of the “sugar feeds fungus” claim.
However:
- the body keeps glucose within a narrow range
- lung infections are not directly altered by short-term dietary carbohydrate restriction
- there is no clinical evidence that low-carb or ketogenic diets improve aspergillosis outcomes
Why it persists: it sounds more scientific than it is, and it is frequently promoted in wellness and biohacking communities.
“Anti-fungal foods such as garlic, turmeric or coconut oil can treat aspergillosis”
Some of these substances show antifungal activity in laboratory experiments.
That is not the same as treating disease in people. The concentrations used in experiments are often very different from what is achievable through normal eating, and human lung disease is far more complex than a petri dish.
Why it persists: laboratory findings are often presented online as though they were proven clinical treatments.
“Detox diets or cleanses remove fungal infection”
There is no biological mechanism by which detox diets or juice cleanses remove Aspergillus from the lungs.
- the lungs are not “cleansed” through the digestive tract
- there is no clinical evidence supporting detox approaches in aspergillosis
Why it persists: detox language is emotionally appealing, especially when people feel unwell and want a sense of control.
“Candida overgrowth” diets apply to aspergillosis
Many patients come across “anti-Candida” diets and wonder whether the same advice applies to Aspergillus.
These diets often recommend:
- cutting out sugar
- avoiding carbohydrates
- removing yeast-containing foods
- following restrictive “anti-fungal” eating plans
However, these ideas are based on a different organism and a different part of the body.
Candida vs Aspergillus: important differences
- Candida is a yeast commonly found on the skin and in the gut
- Aspergillus is a mould in the environment that is inhaled into the lungs
Aspergillus-related disease such as ABPA or CPA affects the lungs and is driven by inhaled spores, not by changes in the gut.
Do “anti-Candida diets” affect Aspergillus?
There is no clinical evidence that diets designed to reduce Candida:
- affect Aspergillus in the lungs
- reduce allergic responses to Aspergillus
- improve outcomes in aspergillosis
These diets often rely on the same assumptions as other myths, especially the idea that “sugar feeds fungus”. Those assumptions do not fit how Aspergillus lung disease works.
What about the gut microbiome?
There is real scientific interest in the gut microbiome and its role in health. However, there is currently no evidence that changing diet to target gut fungi alters aspergillosis outcomes.
This is an area of research interest, but it is not a basis for dietary treatment at present.
Why these diets can be unhelpful
Restrictive anti-Candida or “anti-fungal” diets can sometimes lead to:
- reduced calorie intake
- weight loss
- nutritional imbalance
- anxiety around food
This can be particularly unhelpful in people with chronic lung disease who need to maintain strength and energy.
Key message: diets designed for “Candida overgrowth” are not relevant to aspergillosis and are not supported by evidence in this context.
“If symptoms improve after changing diet, the diet must be working”
This is a very understandable conclusion, but it can be misleading.
Symptoms in aspergillosis often fluctuate because of:
- natural variation in disease activity
- environmental exposure
- allergy activity
- medication changes
An improvement may happen at the same time as a dietary change without being caused by that change.
Advice from non-mainstream or alternative sources
Many people with long-term or difficult-to-control conditions look beyond standard medical care for additional answers. This is entirely understandable, especially when symptoms are persistent or uncertain.
You may come across advice from practitioners or online sources who describe themselves as offering “functional”, “integrative”, or “alternative” approaches. These often include:
- strict or highly restrictive diets
- “anti-fungal” or “detox” protocols
- long lists of supplements
- tests or diagnoses that are not widely used in NHS practice
Some of this advice may sound detailed or scientific. However, it is important to understand that:
- many of these approaches are not supported by clinical evidence in aspergillosis
- they may be based on theories that do not reflect how lung disease develops
- they are often not part of standard respiratory or infectious disease care
In some cases, following this advice can lead to:
- unnecessary dietary restriction
- weight loss or nutritional problems
- delays in receiving appropriate medical treatment
- confusion about symptoms and diagnosis
This does not mean that all non-mainstream approaches are harmful, but it does mean they should be approached with care.
Key message: if you are considering advice outside standard medical guidance, it is usually helpful to discuss it with your clinical team or pharmacist so it can be considered safely alongside your current treatment.
Overall message: many diet claims are based on ideas that sound plausible but do not reflect how aspergillosis works in the body.
A practical, evidence-based approach
For most people with aspergillosis, the most sensible and evidence-based approach is:
- eat a balanced diet
- maintain weight and strength
- include regular sources of protein
- avoid unnecessarily restrictive diets
- follow medicine-specific instructions carefully
- check food–drug interactions rather than relying on social media advice
Focus on supporting your body and treatment — not trying to treat Aspergillus through diet.
When to seek help
It may be worth asking for extra support if you are experiencing:
- unintentional weight loss
- poor appetite
- difficulty managing steroid-related appetite or weight changes
- concerns about blood sugar or bone health
- questions about food–drug interactions
Pharmacists, GPs, specialist teams, and where appropriate dietitians can all help with these issues.
Related information
- Airways mucus and aspergillosis – why mucus can become thick, sticky or difficult to clear.
- Loosen and clear mucus – practical advice about hydration, airway clearance and symptom monitoring.
- Aspergillosis and diet – help with poor appetite, weight loss, food avoidance and stomach symptoms.
References
- Kosmidis C, Denning DW. The clinical spectrum of pulmonary aspergillosis. Thorax. 2015.
- Warris A, Bercusson A, Armstrong-James D. Aspergillus colonization and antifungal immunity in cystic fibrosis patients. Med Mycol. 2019.
- Knutsen AP, Slavin RG. Reviews on allergic bronchopulmonary aspergillosis.
- NHS. Prednisolone guidance.
- British National Formulary (BNF).
- Patient.info interaction checker.
This article is for general information and should not replace advice from your own clinical team.
Diet, mucus and aspergillosis: updated information
We have updated and consolidated our advice about diet, mucus and aspergillosis.
For evidence-based information about food, dairy products, sugar, restrictive diets and nutrition, please read:
Diet and Aspergillosis: What Helps, What Doesn’t, and What Matters Most
If your main concern is thick or difficult-to-clear mucus, see:
Airways mucus and aspergillosis
For practical airway-clearance advice, see:
If you are losing weight, struggling with appetite or avoiding many foods, read:
Aspergillosis and diet: coping with weight loss, poor appetite, food avoidance and stomach symptoms
Airways mucus and aspergillosis
For: patients, carers, general practitioners, specialist nurses and other non-specialists
Last reviewed: 22 September 2026
Important: This page provides general information and does not replace advice from your own clinical team.
What is airway mucus?
Mucus is normal, healthy and essential. Everyone produces it continuously, although most people do not notice it.
Mucus helps to:
- trap dust, pollution, bacteria and fungal spores
- protect the airway lining from drying and irritation
- support local immune defences
- carry trapped material towards the throat, where it can be swallowed or coughed out
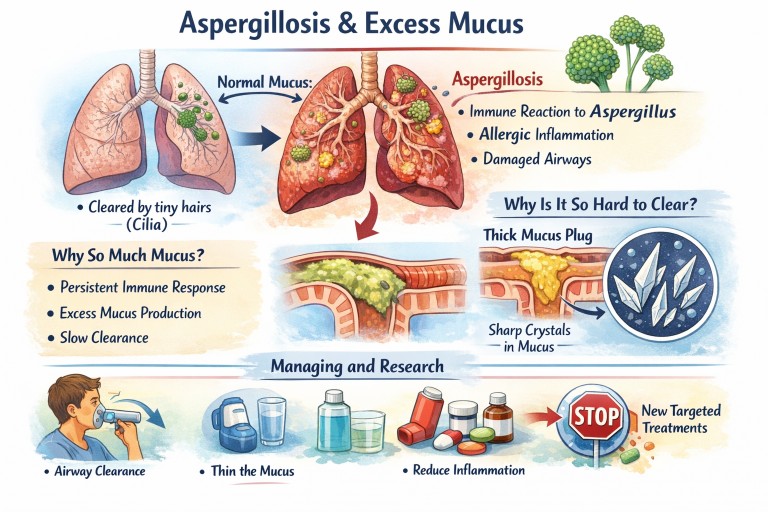
Tiny moving hairs called cilia help move mucus upwards. This process is sometimes called the mucociliary escalator.
In healthy lungs, mucus is usually thin, produced in small amounts and cleared without you noticing it.
Why can aspergillosis cause thick or excessive mucus?
Several processes may contribute, and the balance is different for each person.
Inflammation
Aspergillosis can involve inflammation in the airways. In ABPA, for example, the immune system reacts strongly to Aspergillus and may stimulate the airways to produce more mucus.
Inflammation may continue even when there is no active fungal infection. This is one reason why symptoms do not always change immediately when antifungal treatment is started or stopped.
Airway damage
Bronchiectasis, long-standing asthma, previous infections and other lung conditions can damage or widen the airways. Mucus may then collect in pockets and become harder to move.
Reduced clearance
Inflammation, infection, dehydration and reduced activity can all make mucus clearance less effective. Mucus may remain in the airways for longer, becoming thicker and more difficult to cough up.
What begins as a protective response can therefore become a continuing problem.
What symptoms can thick mucus cause?
Abnormal or excessive mucus may:
- trigger coughing, particularly overnight or on waking
- make breathing feel more difficult
- contribute to wheezing or chest tightness
- interfere with sleep and daily activities
- trap bacteria and contribute to repeated chest infections
- form plugs that partly block an airway
People describe thick sputum in different ways, including “glue-like”, “stringy”, “rubbery” or “impossible to move”.
Mucus plugs and allergic airway disease
Very thick mucus can form a plug within an airway. A mucus plug may cause a sudden increase in breathlessness or wheezing and may sometimes be seen on a CT scan.
In ABPA and other eosinophilic airway diseases, mucus can contain material produced during allergic inflammation. This may make it particularly sticky, rubbery or difficult to clear.
A mucus plug does not automatically prove that an infection is present. The cause needs to be considered alongside symptoms, blood tests, scans and sputum results.
Why mucus management matters
Managing mucus is an important part of day-to-day care for many people with aspergillosis, asthma and bronchiectasis.
Keeping mucus moving may help to:
- reduce the sensation of blockage
- make coughing more effective
- improve comfort and sleep
- reduce the chance of mucus remaining trapped
- help the clinical team recognise changes that may need assessment
Mucus management does not replace treatment for the underlying condition. Inflammation, infection, asthma, bronchiectasis and fungal disease may all need separate treatment.
What may help?
Keep adequately hydrated
Dehydration can make mucus thicker. Drinking regularly may help keep secretions easier to move. The amount that is appropriate depends on your health, medicines and any advice you have been given about fluid intake.
People with heart, kidney or other conditions should ask their clinical team how much fluid is suitable for them.
Use your airway-clearance plan
A respiratory physiotherapist can recommend techniques suited to your condition. These may include:
- active cycle of breathing techniques
- huffing techniques
- postural drainage where appropriate
- oscillating devices such as Flutter, Acapella or Aerobika
- gentle physical activity
Not every technique is suitable for every person. If you cough up blood, have severe breathlessness or have recently had a procedure, ask your clinical team which techniques are safe.
Nebulised saline
Nebulised saline can help some people loosen mucus. Normal saline and hypertonic saline are used in different circumstances.
Use nebulised saline only as advised by your respiratory team. Hypertonic saline can irritate the airways and may cause coughing, wheezing or chest tightness in some people. A bronchodilator may be recommended before it in certain circumstances.
Medicines
Some people are prescribed medicines intended to make mucus easier to clear. Others need treatment aimed at the inflammation, infection, asthma or fungal disease that is driving the mucus problem.
Do not start, stop or change inhalers, steroids, antifungals or mucus-thinning medicines without discussing this with your clinical team.
Keep moving where possible
Gentle, regular movement can help maintain muscle strength and support breathing. Walking, pulmonary rehabilitation or other activity should be adapted to your abilities and medical advice.
What about food and dairy products?
Food does not usually cause the lungs to produce more mucus. Dairy products may leave some people with a temporary coated feeling in the mouth or throat, but this is different from increased mucus production in the lungs.
For more information, read Diet and Aspergillosis: What Helps, What Doesn’t, and What Matters Most.
When should mucus changes be checked?
Contact your doctor or specialist team if you notice:
- more sputum than usual
- a persistent change in sputum colour, smell or thickness
- increasing breathlessness or wheezing
- fever or feeling acutely unwell
- chest pain
- a sustained reduction in exercise tolerance
- more frequent or severe coughing
These changes may be caused by infection, an asthma or ABPA flare, worsening bronchiectasis, medication changes or another problem. They should not automatically be blamed on diet or dehydration.
Seek urgent help if:
- you cough up a large or increasing amount of blood
- you become severely breathless
- you feel faint or extremely unwell
- you think a mucus plug is seriously obstructing your breathing
What research is exploring
Research is investigating better ways to understand and treat abnormal mucus. Areas of interest include:
- reducing excessive mucus production while preserving protective mucus
- changing the structure of very dense mucus
- improving mucus clearance from damaged airways
- treating the allergic and inflammatory pathways that drive mucus production
- developing more personalised treatments based on the individual’s type of lung disease
These approaches are still developing. For now, the most reliable strategies remain treating the underlying disease, following an appropriate airway-clearance plan and seeking advice when symptoms change.
Related information
- Loosen and clear mucus – practical advice about hydration, airway clearance and activity.
- Diet and aspergillosis – whether dairy, sugar or other foods affect mucus and fungal lung disease.
- Aspergillosis and diet – help with poor appetite, weight loss and food avoidance.