

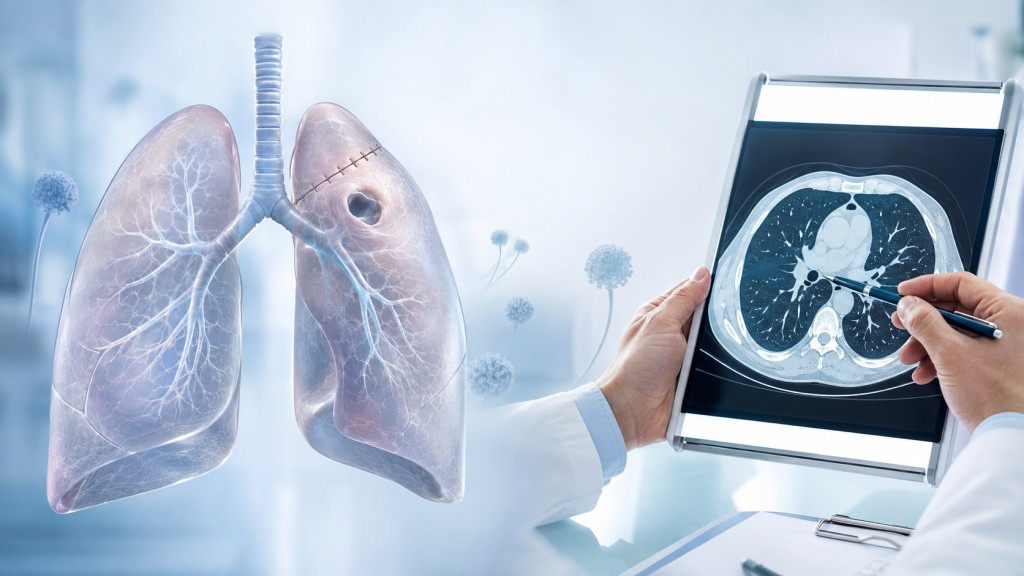
Lung Surgery and Aspergillosis: When Previous Lung Damage Matters
Recovering from lung surgery can take time. It is normal to have some breathlessness, discomfort, tiredness or changes on a chest scan while the lung and chest heal.
For a small number of people, however, previous surgery or other damage to the lungs can create conditions in which Aspergillus causes a longer-term lung problem. This does not mean that everyone who has had lung surgery is at risk. It means that persistent or unexplained symptoms deserve careful assessment, particularly when scans show a cavity or other structural change in the lung.
Why previous lung surgery can matter
Most people breathe in Aspergillus spores every day without becoming ill. The lungs usually clear them before they cause a problem.
After surgery, part of the lung may have been removed or the lung may heal with scarring, altered airways or, occasionally, an air-filled space. These changes can reduce normal mucus clearance. If there is already lung damage from another condition, the effect can be greater.
Aspergillus can sometimes grow in these altered areas of lung. This may lead to chronic pulmonary aspergillosis (CPA), or to an aspergilloma (a fungal ball) within an existing cavity.
Which operations or conditions are relevant?
Aspergillosis is still uncommon after lung surgery, but the possibility may be considered after:
- Surgery to remove part or all of a lung
- Previous treatment for lung cancer, including surgery or radiotherapy
- Surgery for collapsed lung (pneumothorax), bullae or severe emphysema
- Operations following serious infection, tuberculosis or other destructive lung disease
The risk depends on the condition that led to surgery, the amount of underlying lung damage, other treatments and overall lung health. It is not caused by poor hygiene, and CPA is not contagious.
What symptoms should be checked?
Symptoms of CPA can develop gradually over months and may overlap with the effects of the original lung condition or surgery. They can include:
- Persistent or worsening cough
- Increasing breathlessness
- Ongoing tiredness, low energy or weight loss
- Repeated chest infections or symptoms that do not settle as expected
- Chest discomfort
- Coughing up blood (haemoptysis)
A small streak of blood in sputum can have several causes, but should be reported to a healthcare professional. Seek urgent medical help for significant, repeated or rapidly increasing bleeding.
What might be seen on a scan?
Chest X-rays and CT scans are important because they show the structure of the lungs. After surgery, scans may show expected scarring and post-operative change. In CPA, doctors may look for a cavity, thickening around a cavity, a fungal ball, nodules or changes that progress over time.
These findings are not specific to aspergillosis. Cancer recurrence, bacterial infection, inflammation and post-operative change can sometimes look similar. This is why scan findings need to be considered alongside symptoms and laboratory tests.
How is aspergillosis diagnosed after surgery?
There is no single test that can diagnose CPA on its own. Assessment may include:
- A review of symptoms and previous lung history
- Chest X-ray and, usually, a CT scan
- Blood tests, including Aspergillus IgG antibodies
- Sputum testing, where a sample can be produced
- Other tests or specialist review when the diagnosis remains unclear
For CPA, doctors look for a consistent picture of symptoms or progressive scan changes lasting at least three months, evidence that Aspergillus is involved, and exclusion of other likely causes.
What treatment is available?
Treatment depends on the type and extent of aspergillosis, symptoms, lung function and the reason for the original surgery.
Some people with stable findings need regular monitoring rather than immediate treatment. Others need antifungal medication, often for many months or longer. These medicines need careful monitoring because they can interact with other treatments and may cause side effects.
If there is a single aspergilloma causing significant bleeding or other problems, surgery or a procedure to block the bleeding blood vessels may be considered. These decisions are individual and are usually made with a respiratory, thoracic surgical and specialist fungal infection team.
What you can do
Keep attending your planned follow-up appointments after lung surgery and report symptoms that persist, worsen or do not fit with the recovery you expected.
If you have previously had lung surgery and are experiencing ongoing cough, fatigue, weight loss, worsening breathlessness or coughing up blood, ask your respiratory team whether your scans and symptoms need further investigation. A history of surgery does not prove aspergillosis, but it is an important part of the wider lung history.
Related information
- Understanding chronic pulmonary aspergillosis (CPA)
- Aspergilloma (fungal ball)
- How aspergillosis is diagnosed
- Treatment for aspergillosis
- Coughing up blood (haemoptysis)
- Common associated conditions
Sources: ERS/ESCMID clinical guidelines for chronic pulmonary aspergillosis; National Aspergillosis Centre information on CPA.

Cystic Fibrosis and Aspergillus: When Does It Matter?
Cystic fibrosis (CF) affects the way mucus is made and cleared from the lungs. Thick, sticky mucus can make it easier for bacteria and fungi to remain in the airways, including Aspergillus fumigatus.
An Aspergillus result in sputum is therefore not unusual in CF. But it does not automatically mean that the fungus is causing lung disease or that antifungal treatment is needed. The key question is whether it is contributing to a change in symptoms, inflammation or lung damage.
Why Aspergillus is more common in cystic fibrosis
Healthy airways clear inhaled particles and fungal spores through mucus and tiny hairs called cilia. In CF, mucus is harder to move and can collect in the airways. Repeated infection and inflammation may also lead to bronchiectasis, where airways become widened and further mucus can build up.
These conditions can allow Aspergillus to be found repeatedly in respiratory samples. This may be described as colonisation: the fungus is present, but there is no clear evidence that it is causing an active Aspergillus-related illness.
Do highly effective CF medicines change this?
Highly effective CFTR modulator medicines, especially the triple treatment elexacaftor/tezacaftor/ivacaftor (Kaftrio), improve CFTR function and mucus clearance. Recent studies suggest that, after starting this treatment, Aspergillus fumigatus is found less often and in smaller amounts in respiratory samples from people with CF.
This may also reduce the chance of Aspergillus-related inflammation and ABPA. However, it does not mean that every existing Aspergillus problem disappears: ABPA and other lung complications can still need assessment, monitoring and treatment.
Aspergillus can mean different things
In CF, clinicians consider several possible explanations.
Colonisation
Aspergillus is detected in sputum or another respiratory sample, but there is no clear associated deterioration or allergic reaction. It may be monitored rather than treated.
Aspergillus sensitisation
The immune system shows an allergic response to Aspergillus, often on blood or skin testing, without enough features to diagnose ABPA. This can be relevant when reviewing ongoing symptoms, but it is not the same as ABPA.
Allergic bronchopulmonary aspergillosis (ABPA)
ABPA is an excessive allergic immune reaction to Aspergillus growing in the airways. It is a recognised complication of CF, and can cause wheeze, cough, thick mucus plugs, worsening breathlessness, changes on chest imaging and a fall in lung function.
Symptoms often overlap with a CF pulmonary exacerbation, so ABPA can be difficult to recognise.
Other Aspergillus-related lung disease
Less commonly, clinicians may consider other forms of Aspergillus-related disease. The interpretation depends on the whole picture: symptoms, CT scans, sputum results, blood tests, previous lung damage and response to usual CF treatment.
When should ABPA be considered?
ABPA may be considered when someone with CF develops a deterioration that is not fully explained by a usual bacterial infection, particularly if antibiotics are not helping as expected.
Possible clues include:
- New or increased wheeze, cough or breathlessness
- Thick mucus plugs or a change in sputum
- A fall in lung function
- New shadows, mucus impaction or other changes on chest imaging
- Raised total IgE and evidence of allergy to Aspergillus
- Repeated growth of Aspergillus in respiratory samples
No single test gives the answer. The diagnosis is usually based on a combination of symptoms, blood tests, sputum or other respiratory samples, lung function and imaging. This is important because CF, bacterial infection, bronchiectasis and ABPA can all produce similar symptoms and scan appearances.
Why the distinction matters
ABPA causes inflammation that can lead to further airway damage if it is not recognised and treated. On the other hand, treating every positive sputum culture for Aspergillus would expose people to medicines and potential side effects without clear benefit.
Treatment for ABPA is planned by the CF and respiratory teams. It commonly aims to control the allergic inflammation, sometimes alongside antifungal treatment to reduce the amount of fungus in the airways. The best approach varies between individuals and needs to take account of other CF medicines, possible drug interactions and monitoring requirements.
What you can do
Tell your CF team if your symptoms change, especially if you have more wheeze, persistent deterioration, new mucus plugging or a flare that is not improving as expected. Ask what a positive Aspergillus result means in your particular situation, and whether further testing is needed.
Do not assume that a positive culture means you have ABPA—or that it can be ignored. In CF, Aspergillus findings need to be interpreted alongside the full clinical picture.
Related information
- Allergic bronchopulmonary aspergillosis (ABPA)
- Understanding bronchiectasis
- How aspergillosis is diagnosed
- Treatment for aspergillosis
- Common associated conditions
Source: Cystic Fibrosis Foundation ABPA clinical care guidance.
ERS Vision Live
ERS Vision Live is a continuing video collection covering developments across respiratory medicine.
Recent programmes have explored COPD and biologic treatments, pleural infection, antimicrobial resistance, pulmonary toxicity, tuberculosis guidance, pulmonary embolism, vaping and tobacco use, interstitial pneumonia classification, and partnership between patients, clinicians and researchers.
Although the collection is not specific to aspergillosis, several topics are relevant to people living with chronic respiratory disease, including fungal infection, treatment development, antimicrobial resistance and patient involvement in research and care.
Explore the ERS Vision Live collection
The channel states that these programmes are provided by industry partners and are not contributed to or endorsed by the European Respiratory Society.
Amphotericin B resistance in Aspergillus: protecting an important treatment for the future
Amphotericin B is one of the oldest antifungal medicines still used in specialist care. It remains important because it works differently from azole antifungals such as itraconazole, voriconazole, posaconazole and isavuconazole.
Resistance to azole antifungals is an increasing clinical concern in aspergillosis. Amphotericin B resistance can occur, but it is much less commonly encountered in routine patient care.
For most people with aspergillosis, this research is not a reason to worry that amphotericin B will fail if it is needed. Instead, recent research is helping scientists understand how amphotericin B resistance develops and how this valuable treatment might be protected or improved for the future.
What is amphotericin B?
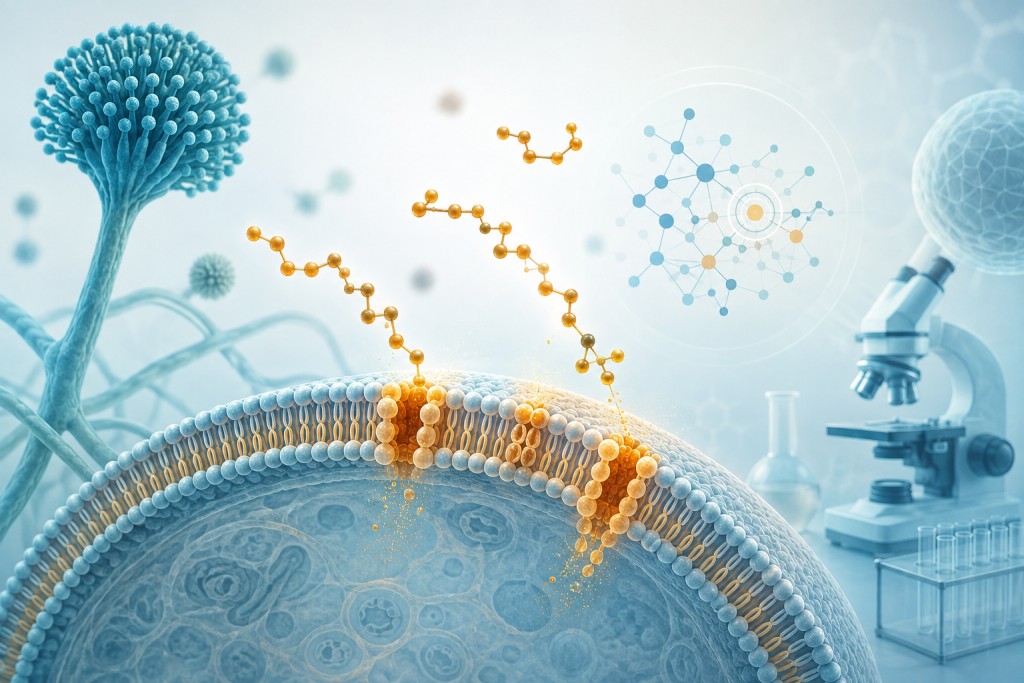
Amphotericin B is an antifungal medicine that damages the fungal cell membrane. It binds to ergosterol, an important component of that membrane, causing damage that can lead to fungal cell death.
It is available in different formulations, including liposomal amphotericin B. It may be used for serious or invasive fungal infections, particularly when azole treatment is unsuitable, ineffective or affected by resistance.
Amphotericin B is valuable partly because it attacks fungi in a different way from the azoles. More information about antifungal treatment is available in our guide to the management of aspergillosis.
What did the original study find?
The original article on this website described a 2019 study from Brazil. Researchers tested 228 Aspergillus isolates and found that 27% of the Aspergillus fumigatus isolates tested showed reduced susceptibility or resistance to amphotericin B.
This was an important warning, but the figure needs careful interpretation. It did not mean that 27% of patients with aspergillosis had amphotericin B-resistant infections. The isolates came from a particular study population and cannot be used to estimate the risk for all patients.
Laboratory resistance results also do not always translate directly into treatment failure. The species of Aspergillus, the type of infection, the patient’s immune system, the drug formulation and the laboratory method used for susceptibility testing all matter.
How is this different from azole resistance?
Azole resistance is currently the more important resistance problem in clinical aspergillosis.
Azole resistance may develop during long-term treatment, but resistant Aspergillus strains can also be acquired from the environment. When resistance is suspected, it can make treatment more difficult because azoles are commonly used for several forms of aspergillosis.
Amphotericin B resistance is less commonly encountered in clinical practice. It remains an important alternative in some situations because it has a different mechanism of action.
That difference is valuable. If resistance to one antifungal class develops, another class may still be effective. Treatment decisions are made by specialist teams using the patient’s clinical condition, laboratory results and response to treatment.
New research is explaining how resistance works
Recent laboratory research is beginning to identify possible mechanisms behind amphotericin B resistance.
A 2024 study of A. fumigatus found that exposure to amphotericin B affected proteins involved in membrane transport, lipid handling and fungal metabolism. One protein, called RtaA, appeared to influence the movement or organisation of sterols within the fungal cell. Changes involving RtaA altered the fungus’s sensitivity to amphotericin B.
This does not mean that RtaA testing is currently available for patients. The finding is experimental. Its importance is that it gives researchers a possible biological pathway to investigate when developing new treatments or resistance tests.
Read the study on RtaA and amphotericin B resistance.
A separate 2025 study examined Aspergillus terreus. This species is already known to have naturally reduced susceptibility to amphotericin B. The researchers found that changes in fungal growth and genetic activity could alter amphotericin B susceptibility, highlighting how complicated resistance can be within a single species.
Read the study of Aspergillus terreus and amphotericin B susceptibility.
Why does species identification matter?
Not all Aspergillus species respond to antifungal medicines in the same way.
Some non-fumigatus Aspergillus species may have higher amphotericin B minimum inhibitory concentrations in laboratory testing. However, interpreting these results is difficult because clinical breakpoints are not available for every species, and studies may use different laboratory methods.
This is one reason specialist laboratories and clinical teams need to interpret susceptibility results in context. A laboratory result is not, by itself, a prediction of what will happen to an individual patient.
Could newer medicines preserve the benefits of amphotericin B?
Researchers are also developing newer polyene antifungals. Polyenes are the drug family that includes amphotericin B.
One example is SF001, an experimental next-generation polyene. Laboratory studies suggest that it may retain broad antifungal activity, including activity against some amphotericin B-resistant isolates, while potentially causing less toxicity.
SF001 is not yet a routine treatment and requires further development and clinical testing. However, this research illustrates how understanding resistance mechanisms may help scientists develop safer and more effective medicines for the future.
Read the study of SF001 and amphotericin B.
What does this mean for patients?
For most people living with aspergillosis:
- amphotericin B resistance is not a common everyday concern;
- azole resistance is currently the more important clinical resistance problem;
- a laboratory finding of reduced susceptibility does not automatically mean treatment will fail;
- species identification and specialist interpretation are important;
- treatment decisions depend on the type of aspergillosis, the patient’s health, drug levels, side effects and laboratory results.
Patients receiving long-term azole treatment may need regular monitoring of symptoms, blood tests, liver function and antifungal drug levels. This is known as therapeutic drug monitoring and can help clinicians judge whether treatment exposure is adequate and whether side effects are developing. See our information about antifungal monitoring and therapeutic drug monitoring.
Protecting an important treatment for the future
Recent research is moving beyond simply detecting resistance. Scientists are beginning to understand the biology behind amphotericin B resistance and are using that knowledge to explore new and potentially safer antifungal medicines.
Amphotericin B resistance is not currently the same kind of widespread clinical problem as azole resistance. For most patients, this research is not a reason to expect treatment failure.
Its importance is that amphotericin B remains a valuable antifungal option, and research into resistance may help preserve or improve the polyene medicines available to patients with serious fungal infections in the future.
References
- Abou-Kandil et al. The proteomic response of Aspergillus fumigatus to amphotericin B reveals the involvement of the RTA-like protein RtaA in AmB resistance. MicroLife.
- Eisele et al. Aspergillus terreus sectorization: a morphological phenomenon shedding light on amphotericin B resistance mechanism. mBio. 2025.
- Vahedi-Shahandashti and Lass-Flörl. In vitro activity of SF001: a next-generation polyene versus amphotericin B. Antimicrobial Agents and Chemotherapy. 2025.
NTM Lung Disease and Aspergillosis: Why They Can Overlap
Nontuberculous mycobacteria (NTM) and aspergillosis are different types of lung disease, but they can sometimes occur together. Both may develop in lungs that have already been damaged by bronchiectasis, COPD, previous tuberculosis or other chronic conditions.
When NTM and aspergillosis overlap, symptoms and CT scan changes can be difficult to interpret. It may not be immediately clear whether deterioration is caused by NTM, chronic pulmonary aspergillosis (CPA), another infection, or more than one condition at the same time.
What is NTM lung disease?
Nontuberculous mycobacteria are environmental bacteria related to the organism that causes tuberculosis. They are found naturally in soil, water, dust and plumbing systems.
There are many species of NTM. Those most commonly associated with lung disease include:
- Mycobacterium avium complex (MAC)
- Mycobacterium abscessus complex
- Mycobacterium kansasii
NTM are not the same as tuberculosis and, in general, NTM lung disease is not spread from person to person.
Many people encounter NTM without becoming ill. Infection is more likely when the lungs are already damaged or when the immune system cannot clear the bacteria effectively.
How does NTM affect the lungs?
NTM can cause a long-term inflammatory infection in the lungs. It may produce nodules, bronchiectasis, cavities or areas of lung inflammation.
Symptoms may include:
- persistent cough
- increasing sputum
- breathlessness
- fatigue
- weight loss
- low-grade fever or night sweats
- recurrent chest infections
- coughing up blood
Some people have NTM detected in a respiratory sample without clear evidence of active lung disease. This may be described as NTM isolation or colonisation. Active NTM pulmonary disease requires the clinical, radiological and microbiological findings to fit together.
Why can NTM and aspergillosis occur together?
Both conditions are more likely when the lungs have structural damage. Bronchiectasis and cavities can make it easier for NTM and Aspergillus to remain in the lungs.
Several factors may contribute:
- damaged or widened airways
- cavities within the lungs
- impaired mucus clearance
- persistent inflammation
- repeated antibiotic or steroid treatment
- low body weight or poor nutritional status
- reduced immune protection
NTM infection may further damage lung tissue, creating conditions in which Aspergillus can grow. Conversely, existing Aspergillus-related disease may make the lungs more vulnerable to NTM.
What forms of aspergillosis may occur?
Several different Aspergillus-related conditions can occur in people with NTM lung disease.
- Chronic pulmonary aspergillosis (CPA), a long-term fungal infection
- chronic cavitary pulmonary aspergillosis
- chronic fibrosing pulmonary aspergillosis
- Aspergillus nodules
- an aspergilloma or fungal ball within a cavity
- less commonly, subacute invasive pulmonary aspergillosis
A positive Aspergillus culture or blood test does not automatically mean that active CPA is present. Aspergillus may sometimes be detected in damaged airways without causing progressive disease.
Why can the diagnosis be difficult?
NTM and CPA can cause similar symptoms and similar changes on CT scans. Both may produce:
- cavities
- nodules
- bronchiectasis
- lung inflammation
- progressive scarring
- persistent cough and sputum
- weight loss and fatigue
This means that a new cavity or worsening scan does not always identify which infection is responsible.
Doctors may need to compare scans over time and look for clues such as:
- a new or enlarging cavity
- a fungal ball within a cavity
- progressive fibrosis around a cavity
- increasing pleural thickening
- new nodules or areas of consolidation
- symptoms that continue despite treatment for NTM
CT findings can suggest CPA, but they need to be interpreted alongside blood tests, sputum results and the clinical course.
What does recent research show?
A 2026 multicentre prospective study followed 365 people with respiratory samples positive for NTM, including MAC, M. kansasii and M. abscessus complex.
Approximately one-third had raised Aspergillus-specific IgG, while 9% developed CPA during the study period. CPA was more common in people with active NTM pulmonary disease than in those with NTM detected without clear evidence of active disease.
The risk of CPA increased over time. Among people with active NTM pulmonary disease, the cumulative incidence of CPA was approximately 2.7% at one year, 8.3% at two years and 14.7% at three years.
People who developed CPA had a higher risk of radiological progression and poorer overall survival. The study also found that some people who initially had a negative Aspergillus IgG test later became positive, suggesting that the result can change during follow-up.
These findings do not mean that everyone with NTM needs antifungal treatment. They do suggest that new or worsening symptoms and CT changes should prompt consideration of CPA, particularly in people with cavities, active NTM disease or repeated steroid treatment.
How is NTM lung disease diagnosed?
Diagnosis usually requires three types of evidence:
- symptoms or other clinical evidence of lung disease
- compatible changes on chest imaging
- repeated or otherwise convincing microbiological evidence of NTM
A single positive sputum sample does not always prove active NTM lung disease. NTM can sometimes be present in the airways without causing progressive infection.
Testing may include:
- sputum cultures for mycobacteria
- chest X-rays and CT scans
- bronchoscopy and bronchoalveolar lavage
- lung-function tests
- blood tests and inflammatory markers
How is CPA investigated?
Assessment for CPA may include:
- symptoms and how they have changed
- comparison of serial CT scans
- Aspergillus-specific IgG
- sputum culture or PCR for Aspergillus
- galactomannan testing in selected circumstances
- bronchoscopy or tissue sampling when necessary
Read more about how aspergillosis is diagnosed.
A raised Aspergillus IgG supports the possibility of CPA but does not prove it on its own. People with structural lung disease may have raised antibody levels without active CPA, so the result must be interpreted with the CT findings and clinical progression.
Can treatment for one condition affect the other?
Yes. Treatment can be complicated when NTM and CPA occur together.
NTM treatment often involves several antibiotics over many months. CPA may require a prolonged course of an oral azole antifungal. These medicines can interact with one another and may affect liver function, heart rhythm or the blood levels of other medicines.
It is therefore important that treatment is coordinated between respiratory, infectious-disease and fungal-disease specialists where appropriate.
Corticosteroids may also require careful consideration. They can be essential for some people with asthma, ABPA or other inflammatory conditions, but they may reduce the immune response that helps control NTM and Aspergillus.
Medicines should never be stopped or changed without advice from the treating team.
What does this mean for someone with NTM?
Having NTM detected in a respiratory sample does not mean that you will develop aspergillosis. Many people with NTM do not develop CPA.
Further assessment may be particularly important if you develop:
- new or worsening breathlessness
- persistent cough or sputum despite NTM treatment
- unexplained weight loss or fatigue
- new or enlarging cavities on CT
- new haemoptysis
- progressive changes despite apparently successful treatment
- repeated courses of steroids
These symptoms can have many causes. They do not automatically mean that CPA is present, but they deserve review rather than being attributed to NTM alone.
Key message: NTM and aspergillosis are different diseases, but they can coexist in structurally damaged lungs. Because symptoms and CT findings overlap, diagnosis may require repeated assessment, Aspergillus IgG testing, sputum microbiology and comparison of scans over time.
Reducing exposure to NTM
NTM are environmental organisms and cannot be avoided completely. They are commonly found in soil, dust, natural water and household plumbing.
People with chronic lung disease may choose to reduce exposure to heavily aerosolised water or soil by:
- avoiding breathing in steam from hot tubs or spa pools
- using care around dusty soil, compost and potting mix
- wearing a well-fitting mask when gardening or working with dusty materials
- maintaining nebulisers and humidifiers carefully
- following local advice about water and plumbing hygiene
These measures cannot guarantee prevention and should not become a source of anxiety. Discuss personal precautions with your healthcare team.
Related information
- Understanding chronic pulmonary aspergillosis
- Bronchiectasis and aspergillosis
- COPD and aspergillosis
- How aspergillosis is diagnosed
- Mucus clearance techniques
- Staying safe from NTM
- Diseases associated with aspergillosis
Further reading
Lee M-R, Shao P-L, Wu C-W, et al.
Clinical impact of chronic pulmonary aspergillosis in patients with pulmonary nontuberculous mycobacterial disease and colonization: a multicentre prospective cohort study.
Annals of Medicine. 2026.
Read the study on PubMed
Clinical impact of chronic pulmonary aspergillosis in patients with nontuberculous mycobacterial pulmonary disease and role of computed tomography in the diagnosis.
Internal Medicine. 2023.
Read the study on PubMed
This information is for education and should not replace advice from your own healthcare team.
Aspergillosis Weekly Research Update: New Clues About Diagnosis, Treatment and Resistance
Research published this week has explored several different aspects of aspergillosis, including complications of chronic pulmonary aspergillosis, CT findings in ABPA, antifungal resistance and the challenges of adjusting voriconazole treatment.
There were no findings likely to change treatment immediately, but several papers provide useful insights into how these conditions are diagnosed and monitored.
Paper of the week: treating an abscess inside a CPA cavity
A case report describes a person with chronic pulmonary aspergillosis who developed a lung abscess inside an existing pulmonary cavity.
The abscess was successfully treated using percutaneous drainage, a procedure in which a catheter is passed through the chest wall into the infected area to allow the contents to drain. This was used alongside antifungal treatment.
Most people with CPA do not develop this complication. However, the report illustrates how the appearance of a cavity can change over time and why new symptoms or changes on scans may require further investigation.
A worsening cavity does not always mean that antifungal treatment has simply failed. There may be an additional problem, such as an abscess, bacterial infection or obstruction, requiring a different treatment approach.
This was a single case report, so it cannot tell us how often this approach will be useful. It does, however, show that drainage may occasionally provide an additional treatment option when infection becomes trapped within a cavity.
Read the case report on PubMed
Dense mucus on CT may help identify ABPA
A radiology report has highlighted the importance of high-attenuation mucus in allergic bronchopulmonary aspergillosis.
In ABPA, thick mucus can collect inside widened airways. On a CT scan, some mucus appears unusually dense or bright. This is called high-attenuation mucus.
Although it is not present in every person with ABPA, this finding can be a useful clue, particularly when someone has difficult-to-control asthma, bronchiectasis, eosinophilia or evidence of sensitisation to Aspergillus.
The finding is important because mucus plugging can contribute to:
- worsening cough and wheeze;
- repeated chest infections;
- blocked airways;
- temporary or permanent changes in lung function; and
- the development or progression of bronchiectasis.
A CT scan is only one part of the diagnostic process. High-attenuation mucus does not diagnose ABPA on its own, and its absence does not exclude ABPA. Doctors also consider symptoms, asthma or bronchiectasis, blood tests and the overall pattern on imaging.
Read the radiology report on PubMed
Genetic variants did not predict viral-associated aspergillosis
A multicentre study investigated whether common genetic variants in two immune-related genes—PTX3 and CLEC7A, also known as Dectin-1—were associated with invasive pulmonary aspergillosis following severe influenza or COVID-19.
The study did not find an association between these genetic variants and either the occurrence or outcome of invasive pulmonary aspergillosis.
This is useful information, but it does not mean that genetics are irrelevant to aspergillosis. The immune system involves many genes, and susceptibility may depend on combinations of genetic variants, the type of underlying illness, immune treatments and the particular form of aspergillosis.
It does show that testing one or two common genetic variants is unlikely to provide a simple way of predicting who will develop viral-associated aspergillosis.
Early signs of resistance to olorofim
Olorofim is a newer antifungal drug being developed for difficult-to-treat fungal infections. Laboratory researchers have identified amino-acid changes in Aspergillus flavus that can reduce susceptibility to olorofim.
This is laboratory research rather than evidence that olorofim resistance is already widespread in patients. Nevertheless, it is important because antifungal resistance can reduce the effectiveness of treatment.
Whenever a new antifungal becomes available, doctors and laboratories need to monitor:
- whether resistant strains are already present;
- whether resistance develops during treatment;
- how resistance is detected; and
- whether a different antifungal is needed.
The study involved Aspergillus flavus, whereas many chronic lung infections are caused by Aspergillus fumigatus. The findings therefore cannot be applied directly to every person with aspergillosis. They are an early warning that resistance testing will remain important as new treatments are introduced.
Why voriconazole blood tests remain important
Voriconazole is affected by genetic differences in an enzyme called CYP2C19. Some people process the drug quickly, while others process it more slowly.
A case report describes a patient with a CYP2C19 result expected to indicate normal metabolism. Despite this, she required a much higher-than-usual dose of voriconazole to achieve therapeutic blood concentrations.
The authors also noted that increased C-reactive protein, or CRP, appeared to be associated with reduced CYP2C19 activity. Inflammation may therefore alter how the body processes voriconazole, even when genetic testing suggests that metabolism should be normal.
This is one reason why a genetic result cannot replace therapeutic drug monitoring. Blood tests can show whether enough voriconazole is present to be effective without reaching unnecessarily high concentrations.
The report does not mean that people with inflammation should automatically receive higher doses. It describes one patient, and dose changes must be guided by clinical review and blood-level monitoring.
Read the case report on PubMed
What does this mean for patients?
The papers published this week reinforce several practical points:
- New or worsening symptoms during CPA may need investigation for complications rather than being assumed to represent simple treatment failure.
- CT findings can provide important clues in ABPA, especially when thick mucus blocks widened airways.
- Genetic testing is unlikely to give a complete answer about susceptibility to aspergillosis.
- Resistance to new antifungals must be monitored as these drugs enter clinical use.
- Voriconazole doses cannot always be predicted accurately from genetics alone, which is why therapeutic drug monitoring is so valuable.
As usual, these studies add to our understanding but do not replace individual medical assessment. Decisions about antifungal treatment, drainage procedures or drug doses should be made by the clinical team caring for the patient.
COPD, Bronchiectasis and Aspergillosis: Understanding Overlapping Lung Conditions
Bronchiectasis and chronic obstructive pulmonary disease (COPD) are different lung conditions, but they can cause many of the same symptoms. Some people also have both conditions at the same time.
This overlap can make diagnosis difficult. It is one reason why doctors may review or refine a diagnosis when symptoms persist, test results change or treatment does not have the expected effect.
Aspergillosis can add another layer of complexity. COPD and bronchiectasis may create the damaged-lung environment in which chronic pulmonary aspergillosis develops, while Aspergillus can also cause allergic or airway disease such as ABPA and Aspergillus bronchitis.
These conditions may share symptoms such as cough, sputum, breathlessness, fatigue, recurrent infections and changes on CT scans. A person may have one condition, two overlapping conditions or several contributing problems at the same time.
The key difference
The simplest distinction is:
COPD mainly causes persistent airflow obstruction, while bronchiectasis is permanent structural damage and widening of the airways.
However, this is an oversimplification. Both conditions can involve airway inflammation, mucus, infection, reduced lung function and progressive lung damage.
What is COPD?
Chronic obstructive pulmonary disease (COPD) is a long-term condition in which airflow through the lungs becomes restricted.
COPD mainly includes two overlapping types of lung damage:
- Chronic bronchitis: long-term inflammation of the airways, often with increased mucus production and a persistent cough.
- Emphysema: damage to the small air sacs in the lungs, reducing the area available for oxygen to pass into the blood.
COPD can also cause narrowing of the smaller airways, trapping of air and difficulty breathing out fully.
Symptoms may include:
- breathlessness, especially during activity
- a persistent cough
- regular production of sputum
- wheezing or chest tightness
- repeated chest infections
- reduced exercise tolerance
- fatigue
COPD is often associated with smoking, but it can also result from long-term exposure to air pollution, occupational dusts and fumes, previous infections, childhood lung problems or genetic conditions such as alpha-1 antitrypsin deficiency.
What is bronchiectasis?
Bronchiectasis is a long-term condition in which one or more airways become permanently widened, thickened or scarred.
Healthy airways use mucus and tiny hair-like structures called cilia to remove dust, microbes and other particles. In bronchiectasis, damaged airways often clear mucus less effectively. Mucus can collect in widened parts of the airway, allowing bacteria and fungi to remain in the lungs for longer.
Bronchiectasis may develop after:
- severe or repeated chest infections
- tuberculosis or other lung infections
- immune-system problems
- asthma or allergic bronchopulmonary aspergillosis
- cystic fibrosis or primary ciliary dyskinesia
- autoimmune or inflammatory conditions
- airway blockage or inhaled foreign material
Sometimes no clear cause is found.
Common symptoms include:
- a long-term cough
- regular production of sputum
- repeated chest infections
- breathlessness
- wheezing
- fatigue
- coughing up blood
Find out more about mucus clearance and airway-clearance techniques.
Why are widened airways a problem?
It may seem that wider airways should make breathing easier. In bronchiectasis, however, widening is a sign that the airway walls have been damaged and weakened.
The widened airways may become floppy and lose their normal ability to move mucus upwards. Mucus can pool in the enlarged sections, where bacteria and fungi may remain and multiply.
This creates a self-reinforcing cycle:
airway damage → widening → mucus retention → infection and inflammation → further airway damage
So, although COPD is often associated with airways that are too narrow, bronchiectasis involves airways that are too damaged and inefficient to clear mucus properly.
How are the conditions diagnosed?
Respiratory diagnoses are not usually based on symptoms or lung function alone. Doctors combine:
- symptoms and medical history
- spirometry and other lung-function tests
- CT imaging
- sputum and blood tests
- examination findings
- response to treatment
A useful way to think about this is:
Lung function measures what the lungs can do; imaging shows what has happened to their structure.
Diagnosing COPD
COPD is mainly identified by persistent airflow obstruction. Spirometry measures how much air a person can breathe out and how quickly they can do so.
Current COPD guidance uses post-bronchodilator spirometry to confirm persistent airflow obstruction. Other information, including symptoms, smoking history, CT scans and exacerbations, helps assess the wider disease.
Diagnosing bronchiectasis
Bronchiectasis is fundamentally an anatomical diagnosis. A thin-section or high-resolution CT scan is usually needed to show that the airways are permanently widened or distorted.
Lung function in bronchiectasis may be:
- normal
- obstructive
- restrictive
- mixed
A normal spirometry result therefore does not exclude bronchiectasis.
Can someone have both COPD and bronchiectasis?
Yes. COPD and bronchiectasis can coexist, particularly in people with more advanced lung disease, frequent exacerbations or persistent sputum production.
When both conditions are present, a person may have:
- greater breathlessness
- more frequent exacerbations
- greater sputum production
- more persistent airway infection
- more complex treatment needs
The correct conclusion may not be that someone has COPD instead of bronchiectasis. They may have COPD and bronchiectasis, with each condition contributing to their symptoms.
Where does aspergillosis fit?
People with COPD or bronchiectasis may be more vulnerable to Aspergillus-related disease because their lungs or airways are already damaged.
Possible conditions include:
- chronic pulmonary aspergillosis
- Aspergillus bronchitis
- allergic bronchopulmonary aspergillosis
- Aspergillus sensitisation
- Aspergillus colonisation without active disease
These conditions are different. A positive sputum culture or blood test does not automatically mean that active aspergillosis is present.
Assessment may involve:
- symptoms and their pattern over time
- CT imaging
- Aspergillus-specific IgG or IgE
- total IgE and eosinophils
- sputum culture or PCR
- lung-function testing
- occasionally bronchoscopy
Read more about how aspergillosis is diagnosed.
What about asthma and other lung diseases?
Asthma can also cause wheeze, cough and variable airflow obstruction. Some people have features of both asthma and COPD, particularly later in life. Asthma may also coexist with bronchiectasis.
Other conditions can produce similar symptoms, including:
- interstitial lung disease
- previous tuberculosis
- heart failure
- lung cancer
- pulmonary hypertension
- non-tuberculous mycobacterial infection
- chronic pulmonary aspergillosis
This is why a diagnosis may need to be reconsidered when symptoms, scans or test results do not fit the original explanation.
Why might doctors change the diagnosis?
Doctors sometimes appear to switch between diagnoses such as COPD, asthma, bronchiectasis and aspergillosis. This can happen because the conditions share many symptoms, and because more than one condition may be present at the same time.
Early in an assessment, a doctor may use a working diagnosis based on the information available. That diagnosis may be refined when spirometry, CT scans, sputum tests or blood tests provide more evidence.
For example:
- a person initially thought to have COPD may later be found to have bronchiectasis on CT
- someone diagnosed with asthma may later develop persistent airflow obstruction or emphysema
- a person with bronchiectasis may be found to have an underlying immune problem or previous infection
- Aspergillus-related disease may become apparent when symptoms persist despite usual treatment
A changing diagnosis does not necessarily mean that earlier care was misguided. It may mean that the clinical picture has become clearer.
Can poor treatment response suggest another diagnosis?
Sometimes. If symptoms do not improve as expected, doctors may ask:
- Was the original diagnosis correct?
- Is another condition present as well?
- Is there an infection or complication?
- Is the treatment being taken correctly and tolerated?
- Has the disease changed over time?
For example, someone repeatedly treated for COPD exacerbations who continues to produce large amounts of sputum may need assessment for bronchiectasis, chronic infection or Aspergillus-related disease.
However, lack of improvement does not prove that the diagnosis was wrong. Treatment may have been insufficient, difficult to take, affected by another medicine or aimed at only one part of a complex condition.
The most useful response is usually reassessment rather than an automatic change of label.
Why identifying the full picture matters
Different diagnoses lead clinicians to look for different problems and choose different treatments.
- COPD may require bronchodilators, pulmonary rehabilitation and exacerbation prevention.
- Bronchiectasis may require airway clearance, sputum monitoring and investigation of its cause.
- Asthma may require treatment aimed at variable airway inflammation.
- Aspergillus-related disease may require specific blood tests, microbiology or antifungal treatment.
Recognising one diagnosis does not exclude another. The aim is to understand all the factors contributing to a person’s symptoms.
Key message: COPD, bronchiectasis, asthma and aspergillosis can overlap, but they are not interchangeable diagnoses. Lung function shows how well the lungs work, while CT scans show structural damage. When symptoms persist or treatment is not working as expected, reassessing the diagnosis may reveal another condition—or several conditions acting together.
Related information
- COPD and aspergillosis
- Bronchiectasis and aspergillosis
- Understanding chronic pulmonary aspergillosis
- How aspergillosis is diagnosed
- Mucus clearance techniques
- Diseases associated with aspergillosis
Further reading
British Thoracic Society guideline for bronchiectasis in adults
Global Initiative for Chronic Obstructive Lung Disease: 2025 report
European Respiratory Society guideline for the management of adult bronchiectasis
This information is for education and should not replace advice from your own healthcare team.
Bronchiectasis and Aspergillosis: Understanding the Connection
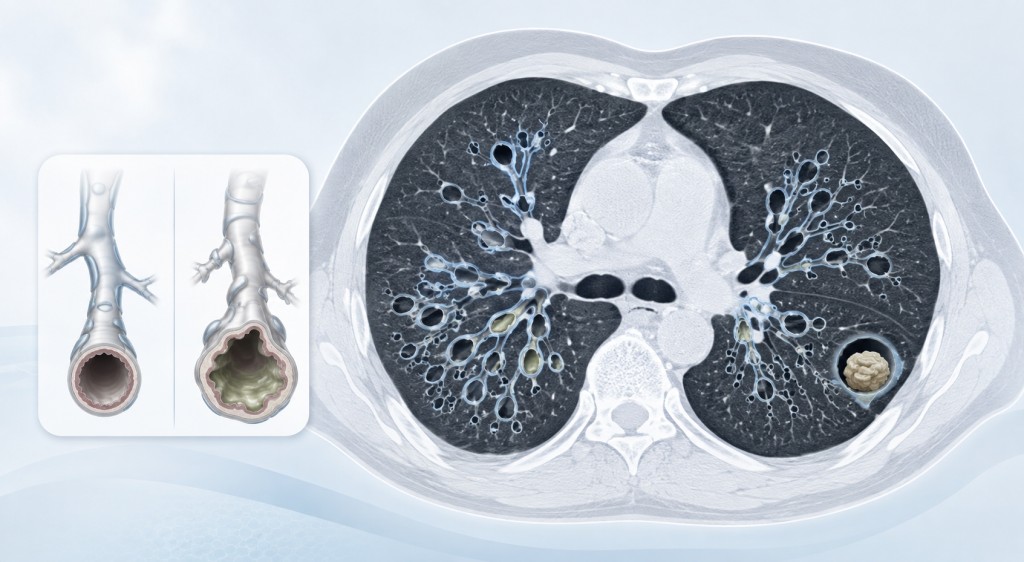
Bronchiectasis and aspergillosis are separate conditions, but they can sometimes occur together. Bronchiectasis damages and widens the airways, making it more difficult to clear mucus and inhaled particles such as Aspergillus spores.
Most people with bronchiectasis will not develop aspergillosis. However, Aspergillus-related disease may be overlooked because its symptoms can resemble bronchiectasis itself, a bacterial chest infection or a flare-up.
What is bronchiectasis?
Bronchiectasis is a long-term lung condition in which one or more airways become permanently widened, thickened or scarred.
Healthy airways use a thin layer of mucus and tiny hair-like structures called cilia to remove dust, microbes and other particles. In bronchiectasis, damaged airways often clear mucus less effectively. Mucus can collect in widened parts of the airway, allowing bacteria and fungi to remain in the lungs for longer.
Bronchiectasis may develop after:
- severe or repeated chest infections
- tuberculosis or other lung infections
- immune-system problems
- asthma or allergic bronchopulmonary aspergillosis
- cystic fibrosis or primary ciliary dyskinesia
- autoimmune or inflammatory conditions
- airway blockage or inhaled foreign material
Sometimes no clear cause is found.
Common symptoms include:
- a long-term cough
- regular production of sputum
- repeated chest infections
- breathlessness
- wheezing
- fatigue
- coughing up blood
Find out more about mucus clearance and airway-clearance techniques.
Why can bronchiectasis increase the risk of aspergillosis?
Bronchiectasis changes the structure of the airways and makes it harder to remove mucus. This may allow Aspergillus spores to remain in the airways and interact with the immune system.
The risk of Aspergillus-related disease may be influenced by:
- the extent and location of bronchiectasis
- how much mucus is retained
- the number and severity of chest infections
- underlying asthma or allergy
- previous tuberculosis or other structural lung disease
- corticosteroid or other immunosuppressive treatment
- the individual immune response to Aspergillus
Aspergillus may be present in sputum without causing active disease. This is sometimes described as colonisation or airway carriage. Other people develop an exaggerated allergic response, Aspergillus bronchitis or a chronic fungal infection.
Different Aspergillus-related conditions
Several different Aspergillus-related conditions can occur in people with bronchiectasis. They should not be treated as if they are all the same.
Aspergillus sensitisation
Aspergillus sensitisation means that the immune system has developed an allergic response to Aspergillus. It may be associated with wheezing, airway inflammation or more frequent exacerbations, but it is not the same as an active fungal infection.
Allergic bronchopulmonary aspergillosis
Allergic bronchopulmonary aspergillosis (ABPA) occurs when the immune system reacts strongly to Aspergillus in the airways. It is traditionally associated with asthma and cystic fibrosis, but it can also occur in people with bronchiectasis who do not have either condition.
ABPA may cause:
- worsening wheeze or breathlessness
- thick or difficult-to-clear mucus
- recurrent chest symptoms
- increased eosinophils or IgE
- fleeting or changing shadows on chest imaging
- central bronchiectasis or high-attenuation mucus on CT
Read more about allergic bronchopulmonary aspergillosis.
Aspergillus bronchitis
Aspergillus bronchitis is a condition in which Aspergillus is repeatedly detected in the airways and is associated with a persistent productive cough, sputum and airway inflammation.
It is more likely to be considered when a person has:
- a chronic productive cough
- repeated detection of Aspergillus in sputum or bronchoscopy samples
- an increased Aspergillus IgG level
- no clear evidence of ABPA or CPA
Learn more in our guide to Aspergillus bronchitis.
Chronic pulmonary aspergillosis
Chronic pulmonary aspergillosis (CPA) is a long-term fungal infection that usually develops in structurally abnormal lungs. It may cause cavities, nodules, thickening around cavities or progressive changes over time.
Symptoms may include:
- persistent cough
- increasing breathlessness
- weight loss
- fatigue
- night sweats or a low-grade fever
- persistent sputum
- coughing up blood
Read more about the different types of CPA.
What does recent research show?
A 2025 review examined ABPA and other Aspergillus-related airway diseases in bronchiectasis. It concluded that ABPA, Aspergillus sensitisation, chronic Aspergillus infection and Aspergillus bronchitis may form a spectrum of disease influenced by both airway damage and the immune response.
The review estimated that ABPA affects approximately 4% of people with bronchiectasis, although estimates vary substantially between studies and populations. It also reported that Aspergillus sensitisation and chronic Aspergillus infection may collectively affect up to 30% of people with bronchiectasis.
These figures should be interpreted cautiously. They do not mean that one in three people with bronchiectasis has an active fungal infection. Sensitisation, colonisation and active disease are different findings, and not everyone with a positive test requires antifungal treatment.
The review argued that Aspergillus-related disease may be associated with more severe bronchiectasis and more frequent exacerbations. It also noted that ABPA may sometimes contribute to bronchiectasis, rather than simply occurring as a result of already damaged airways.
A separate 2026 international study found that sensitisation to particular Aspergillus allergens was associated with markers of higher-risk bronchiectasis, including exacerbations, hospital admissions and Pseudomonas aeruginosa infection. The study does not prove that sensitisation causes bronchiectasis, but it suggests that fungal sensitisation may identify a subgroup needing closer assessment.
Can ABPA cause bronchiectasis?
The relationship between ABPA and bronchiectasis is complex.
Bronchiectasis may make it easier for Aspergillus to remain in the airways, increasing the opportunity for an allergic immune response. However, repeated Aspergillus-driven inflammation in ABPA may also damage the airways and contribute to bronchiectasis.
Recent research suggests that ABPA may contribute to bronchiectasis in some susceptible people, particularly when there is prolonged allergic inflammation and mucus plugging. However, not every person with ABPA develops bronchiectasis, and not every person with bronchiectasis has ABPA.
Symptoms can overlap
Bronchiectasis and Aspergillus-related disease may all cause:
- cough
- breathlessness
- wheeze
- fatigue
- increased sputum
- repeated chest infections
- reduced exercise tolerance
This overlap can make it difficult to know whether symptoms represent a usual fluctuation, a bacterial infection, ABPA, Aspergillus bronchitis, CPA or a combination of conditions.
Further assessment may be useful when symptoms are unusually persistent, severe or different from previous exacerbations.
How might doctors investigate Aspergillus-related disease?
Assessment usually combines several types of information:
- symptoms and their pattern over time
- the frequency and severity of exacerbations
- chest X-rays and CT scans
- sputum cultures and other microbiology
- Aspergillus-specific IgE and IgG blood tests
- total IgE and eosinophil counts
- lung-function testing
- occasionally bronchoscopy
Read more about how aspergillosis is diagnosed.
Aspergillus-specific IgG may support a diagnosis of CPA or Aspergillus bronchitis. Aspergillus-specific IgE and total IgE are more relevant when ABPA is suspected.
A positive blood test does not automatically prove active disease. Test results need to be interpreted with symptoms, imaging and sputum findings.
Why CT scans are important
CT scans can show the pattern and extent of bronchiectasis and may identify additional findings such as:
- mucus plugging
- high-attenuation mucus
- nodules
- cavities
- thickening around cavities
- changes suggesting a fungal ball
A CT scan may help distinguish established bronchiectasis from new changes that require further investigation. Read more about CT scans and aspergillosis.
When should someone with bronchiectasis seek further assessment?
Speak to your healthcare team if you have bronchiectasis and develop:
- a clear change in your usual cough or sputum
- repeated exacerbations or chest infections
- symptoms that do not respond as expected to antibiotics
- new or worsening wheeze
- unexplained weight loss or fatigue
- new changes on a chest X-ray or CT scan
- repeated courses of steroids
- coughing up blood
These symptoms do not necessarily mean that you have aspergillosis. They may be caused by bronchiectasis, bacteria, viruses, asthma or other conditions. The purpose of further assessment is to identify the cause accurately.
How is treatment decided?
Treatment depends on which Aspergillus-related condition is present.
- Aspergillus sensitisation may require monitoring and treatment of associated airway disease rather than antifungal medication.
- ABPA may require corticosteroids, antifungal treatment or other specialist therapies.
- Aspergillus bronchitis may be considered for antifungal treatment when symptoms and microbiology support the diagnosis.
- CPA may require prolonged antifungal treatment and careful monitoring.
Airway clearance, vaccination, treatment of bacterial infections and management of the underlying bronchiectasis remain important regardless of whether Aspergillus is detected.
Antifungal medicines can interact with inhalers, corticosteroids and other medicines, so they should only be started under appropriate medical supervision.
Key message: Bronchiectasis makes it harder to clear mucus and inhaled particles, which may increase vulnerability to several Aspergillus-related conditions. Most people with bronchiectasis will not develop active aspergillosis, but persistent or unusually severe symptoms may justify assessment for Aspergillus sensitisation, ABPA, Aspergillus bronchitis or CPA.
Related information
- Understanding chronic pulmonary aspergillosis
- Aspergillus bronchitis
- Allergic bronchopulmonary aspergillosis
- How aspergillosis is diagnosed
- Understanding Aspergillus blood tests
- Mucus clearance techniques
- Diseases associated with aspergillosis
Further reading
Recent review: Agarwal R, Chotirmall SH, Chalmers JD.
Allergic bronchopulmonary aspergillosis and Aspergillus-related airway diseases in bronchiectasis: a narrative review.
Journal of Thoracic Disease. 2025;17:11501–11519.
Read the review on PubMed
Recent research: Tiew PY, Narayana JK, Jaggi TK, et al.
Aspergillus fumigatus sensitization is associated with high-risk bronchiectasis.
Chest. 2026;169:932–946.
Further discussion: Agarwal R, Sehgal IS, Muthu V, Bardin P.
Does ABPA contribute to bronchiectasis? A structured evaluation of competing hypotheses.
Clinical & Experimental Allergy. 2026;56:498–505.
Read the paper
This information is for education and should not replace advice from your own healthcare team.
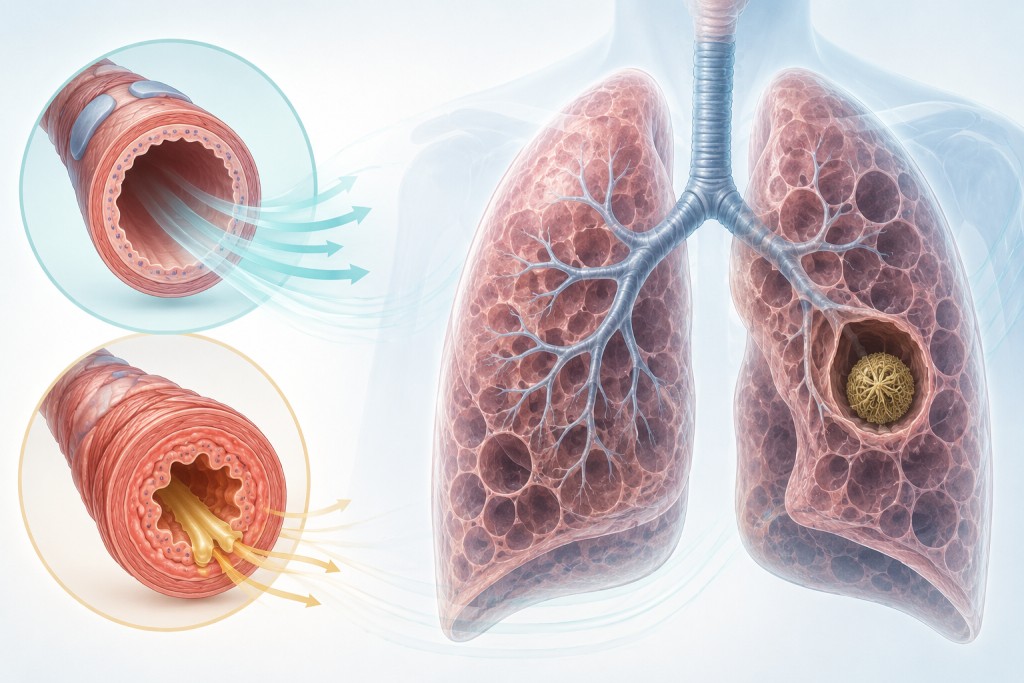
COPD and Aspergillosis: Understanding the Connection
Chronic obstructive pulmonary disease (COPD) and aspergillosis are separate conditions, but they can sometimes occur together. COPD can damage the airways and lung tissue, making it more difficult to clear inhaled Aspergillus spores.
Most people with COPD will not develop aspergillosis. However, Aspergillus-related disease may be overlooked because its symptoms can resemble a COPD flare-up or a chest infection.
What is COPD?
Chronic obstructive pulmonary disease (COPD) is a long-term condition in which airflow through the lungs becomes restricted. The obstruction usually develops gradually and may become more noticeable over time.
COPD mainly includes two overlapping types of lung damage:
- Chronic bronchitis: long-term inflammation of the airways, often with increased mucus production and a persistent cough.
- Emphysema: damage to the small air sacs in the lungs, reducing the area available for oxygen to pass into the blood.
Many people have features of both. COPD can also cause narrowing of the smaller airways, trapping of air and difficulty clearing mucus from the lungs.
Symptoms may include:
- breathlessness, especially during activity
- a persistent cough
- regular production of sputum
- wheezing or chest tightness
- repeated chest infections
- reduced exercise tolerance
- fatigue
Symptoms may remain fairly stable for long periods, but can suddenly worsen during an exacerbation. An exacerbation may be triggered by a viral or bacterial infection, air pollution, smoke, cold weather or other factors.
COPD is often associated with smoking, but it can also result from long-term exposure to air pollution, occupational dusts and fumes, previous infections, childhood lung problems or genetic conditions such as alpha-1 antitrypsin deficiency.
COPD is not contagious. It is also not simply an inevitable part of getting older. Diagnosis usually involves a medical history, examination and breathing tests such as spirometry.
What is aspergillosis?
Aspergillosis describes several different conditions caused by Aspergillus, a common mould found in soil, dust, compost and the air.
Most people breathe in Aspergillus spores without becoming ill. Problems are more likely when a person has damaged lungs, an altered immune response or treatment that suppresses immunity.
Relevant forms of disease include:
- chronic pulmonary aspergillosis (CPA)
- aspergilloma, sometimes called a fungal ball
- Aspergillus bronchitis
- allergic bronchopulmonary aspergillosis (ABPA)
- invasive pulmonary aspergillosis
These conditions are different and require different investigations and treatments.
Why can COPD increase the risk of aspergillosis?
COPD can affect the lungs in several ways that may increase vulnerability to Aspergillus:
- damaged airways may clear mucus and inhaled particles less effectively
- emphysema can create areas of structurally abnormal lung
- previous infections may leave scars or cavities
- repeated exacerbations can increase inflammation and lung damage
- corticosteroid treatment can alter the immune response
The risk is not caused by COPD alone. It depends on the severity and type of lung damage, previous infections, smoking history, immune function, steroid exposure and other health conditions.
New research: Aspergillus allergy and sensitisation in COPD
A 2026 systematic review and meta-analysis examined allergic bronchopulmonary aspergillosis (ABPA) and Aspergillus sensitisation in people with COPD. The researchers combined evidence from 23 studies involving more than 5,000 people.
They estimated that:
- approximately 2.1% of people with COPD had ABPA
- approximately 10.4% had evidence of sensitisation to Aspergillus
These findings suggest that Aspergillus-related allergy may occur in COPD more often than previously recognised. However, sensitisation is not the same as active infection or ABPA. A positive allergy or blood test does not automatically mean that treatment is needed.
The findings support a more careful assessment of people with COPD who have unexplained wheezing, difficult-to-control symptoms, recurrent exacerbations or features suggesting an allergic fungal response.
Read our summary of the 2026 COPD and Aspergillus review.
Chronic pulmonary aspergillosis and COPD
CPA is a long-term fungal lung infection that usually develops in areas of existing lung damage. It may cause cavities, thickening around cavities, nodules or progressive changes in the lungs.
Symptoms of CPA can include:
- persistent cough
- increasing breathlessness
- fatigue
- weight loss
- night sweats or a low-grade fever
- persistent or increasing sputum
- coughing up blood
These symptoms can also occur during COPD exacerbations, which makes diagnosis difficult. Symptoms that continue after the usual treatment for a COPD flare-up may need further investigation.
Could Aspergillus be contributing to repeated COPD flare-ups?
Not every COPD exacerbation is caused by Aspergillus. Bacteria, viruses, pollution, smoking, weather changes and other factors can all trigger worsening symptoms.
However, Aspergillus may sometimes be involved when a person has:
- frequent or unusually severe exacerbations
- symptoms that do not respond as expected to antibiotics or inhalers
- persistent chest symptoms between exacerbations
- unexplained weight loss or fatigue
- new cavities, nodules or other changes on a CT scan
- recurrent haemoptysis
- a history of tuberculosis or another condition causing structural lung damage
Research has also found Aspergillus in the airways of some people with COPD without proving that it is causing active disease. Detection of Aspergillus therefore needs to be interpreted alongside symptoms, imaging and other test results.
Why steroids need careful balancing
Corticosteroids may be prescribed during COPD exacerbations and, in some people, as part of regular inhaled treatment. They can reduce airway inflammation and improve symptoms.
However, corticosteroids can also affect the immune response that helps control Aspergillus. Recent research has reported an association between corticosteroid exposure and pulmonary aspergillosis, with higher exposure associated with greater risk.
This does not mean that people with COPD should stop their inhalers or avoid steroids when they are medically necessary. Treatment should only be changed with advice from a healthcare professional.
The important point is that repeated or prolonged steroid treatment, particularly when symptoms are not improving as expected, may be one reason to review the diagnosis and consider whether fungal disease or another infection is contributing. Read more about steroids, aspergillosis and the immune system.
How might doctors investigate aspergillosis?
There is no single test that diagnoses every form of aspergillosis. Assessment may include:
- symptoms and how long they have been present
- previous chest imaging and a current CT scan
- lung-function testing
- Aspergillus-specific IgG blood testing
- total IgE and Aspergillus-specific IgE when ABPA is suspected
- sputum culture, PCR or other microbiology
- occasionally bronchoscopy
Read more about how aspergillosis is diagnosed.
An Aspergillus IgG blood test can provide evidence of a longer-term immune response to Aspergillus and is often useful when CPA is being considered. However, a positive result does not prove active CPA by itself.
CT scans may help identify cavities, nodules, fibrosis, emphysema, mucus plugging or other changes that are difficult to see on a chest X-ray. Read more about why CT scans are used in aspergillosis.
When should someone with COPD seek further assessment?
Speak to your healthcare team if you have COPD and develop:
- breathlessness that is worsening or different from usual
- a cough that does not settle after an exacerbation
- persistent or increasing sputum
- unexplained weight loss or fatigue
- repeated courses of antibiotics or steroids
- new abnormalities on a chest X-ray or CT scan
- coughing up blood
These symptoms do not necessarily mean that you have aspergillosis. They may result from COPD itself, infection, heart disease, medication effects or other causes. The purpose of further assessment is to identify the cause accurately so that treatment can be chosen appropriately.
Key message: Most people with COPD will not develop aspergillosis. However, COPD-related lung damage, repeated exacerbations and corticosteroid exposure may increase susceptibility. If symptoms are unusually persistent, severe or difficult to explain, Aspergillus-related disease may need to be considered alongside the more common causes of COPD deterioration.
Related information
- Understanding chronic pulmonary aspergillosis
- How aspergillosis is diagnosed
- Understanding Aspergillus blood tests
- Steroids and the immune system
- Diseases associated with aspergillosis
Further reading
Recent systematic review: Ajayababu A, Antony A, Goyal B, Ray A.
Prevalence of allergic bronchopulmonary aspergillosis/Aspergillus sensitization in chronic obstructive pulmonary disease: A systematic review and meta-analysis.
Respiratory Investigation. 2026.
Read the paper on PubMed
Clinical overview: Otu A, et al.
The clinical spectrum of aspergillosis in chronic obstructive pulmonary disease.
Infection. 2023;51:813–829.
Clinical guidance: The British Thoracic Society has published a clinical statement on
Aspergillus-related chronic lung disease
This information is for education and should not replace advice from your own healthcare team.
Sarcoidosis and Aspergillosis: Understanding an Important Connection
Sarcoidosis and aspergillosis are different conditions, but they can sometimes occur in the same person. The relationship is most important when sarcoidosis has caused lasting damage to the lungs, including scarring, fibrosis or cavities.
This does not mean that everyone with sarcoidosis will develop aspergillosis. Most people with sarcoidosis do not. However, when symptoms or lung changes worsen, it is important not to assume automatically that sarcoidosis is becoming more active.
What is sarcoidosis?
Sarcoidosis is an inflammatory condition in which groups of immune cells form small areas of inflammation called granulomas. It can affect several parts of the body, but the lungs and lymph nodes in the chest are most commonly involved.
Some people have few or no symptoms. Others may experience:
- breathlessness
- a persistent cough
- chest discomfort
- fatigue
- reduced exercise tolerance
- weight loss or a general feeling of being unwell
In some people, inflammation settles without causing permanent damage. In others, long-term inflammation can lead to scarring and changes in the structure of the lungs.
Why can sarcoidosis increase the risk of aspergillosis?
Chronic pulmonary aspergillosis (CPA) is a long-term lung infection caused by Aspergillus, a mould that is commonly found in the environment and is breathed in regularly by most people. You can read more about the different forms of CPA.
Healthy lungs usually clear inhaled Aspergillus spores without difficulty. However, damaged or scarred lung tissue can make it easier for Aspergillus to persist and grow.
Advanced pulmonary sarcoidosis may cause:
- fibrosis and scarring
- distortion of the airways
- areas of poorly functioning lung
- cavities or spaces within the lungs
These changes may create conditions in which chronic pulmonary aspergillosis or an aspergilloma can develop. An aspergilloma, sometimes called a fungal ball, is a collection of fungal material that grows within an existing lung cavity.
The risk is not caused by sarcoidosis alone. It reflects a combination of factors, including the amount and type of lung damage, the immune response, exposure to Aspergillus and treatments such as corticosteroids or other immunosuppressive medicines.
How common is the association?
The relationship between sarcoidosis and chronic pulmonary aspergillosis is clinically important, but it remains relatively understudied. A 2026 review reported that approximately 2% of people with sarcoidosis developed CPA in some recent tertiary-care cohorts.
Older studies involving people with more advanced fibrocystic sarcoidosis reported higher estimates, between 3% and 12%. These figures are not directly comparable because specialist centres tend to see more people with severe and complicated disease.
The available evidence does not suggest that sarcoidosis commonly or inevitably leads to aspergillosis. Instead, risk appears to result from several factors acting together:
- fibrosis, cavities or other structural lung damage
- changes in local and general immune function
- regular exposure to Aspergillus in the environment
- corticosteroid or other immunosuppressive treatment
Symptoms can overlap
One of the difficulties is that sarcoidosis and chronic pulmonary aspergillosis can cause similar symptoms. These may include:
- increasing breathlessness
- persistent or worsening cough
- fatigue
- weight loss
- reduced lung function
- declining ability to exercise
- changes visible on chest X-rays or CT scans
This overlap can make it difficult to tell whether symptoms are caused by active sarcoidosis, permanent lung damage, chronic infection, or more than one condition at the same time.
Blood in the sputum, known as haemoptysis, can occur with several lung conditions. It may also occur when an aspergilloma or CPA affects blood vessels in damaged lung tissue. Any new or significant haemoptysis should be discussed promptly with a healthcare professional.
Why scans may need careful interpretation
Chest imaging is an important part of assessing both sarcoidosis and aspergillosis. A CT scan may show fibrosis, nodules, cavities, thickening around cavities or changes in existing areas of lung damage.
Some of these findings can be seen in advanced sarcoidosis as well as CPA. A single scan does not always provide the complete answer. Doctors may need to compare scans over time and consider:
- whether existing cavities or scars are changing
- whether new cavities or nodules have appeared
- whether there is thickening around a cavity
- whether a fungal ball is present
- how scan findings relate to symptoms and lung-function results
The overall pattern, and how it changes over time, is often more useful than one isolated scan finding. Read more about why CT scans are used in aspergillosis.
The challenge of steroid treatment
Corticosteroids are often used to control inflammation caused by sarcoidosis. Other immunosuppressive medicines may also be used when sarcoidosis affects the lungs or other organs.
These treatments can be very important and should not be stopped suddenly or changed without medical advice. However, corticosteroids and some other immunosuppressive medicines can reduce the body's ability to control infection.
If chronic pulmonary aspergillosis is present but not recognised, increasing immunosuppression may allow the infection to become more active. This is one reason why unexpected deterioration, new radiological changes or symptoms that do not respond as expected should be assessed carefully before assuming that sarcoidosis is the only cause.
This does not mean that steroids are always unsafe for people with sarcoidosis. The decision is individual and may involve balancing inflammation, infection risk, lung damage and other health needs. Read more about steroids, aspergillosis and the immune system.
What does recent research show?
A 2026 review concluded that CPA occurs mainly when sarcoidosis has caused substantial structural lung damage, particularly fibrosis or cavities. The authors described the association as clinically important but relatively understudied.
In a study of 65 people with CPA complicating sarcoidosis, almost all had advanced fibrocystic pulmonary disease. Chronic cavitary pulmonary aspergillosis was the most common form of CPA. The factors most strongly associated with outcome were the extent of fibrosis, reduced overall lung function and pulmonary hypertension.
The study also found that poor outcomes were more often related to advanced sarcoidosis and the resulting loss of lung function than to aspergillosis alone. This is important because it shows that CPA is part of a complex picture rather than necessarily being the only cause of deterioration.
These findings help explain why assessment needs to consider the whole clinical picture. A change in symptoms or a scan may reflect active sarcoidosis, permanent lung damage, CPA or a combination of these conditions.
How might doctors investigate aspergillosis?
There is no single test that diagnoses every form of aspergillosis. Doctors usually combine several types of information, including:
- symptoms and how they have changed
- previous CT scans and current imaging
- lung-function tests
- blood tests for Aspergillus-specific antibodies, particularly Aspergillus IgG
- sputum testing for Aspergillus and other organisms
- occasionally bronchoscopy or other specialised tests
Blood tests for Aspergillus-specific IgG may support the diagnosis of CPA. However, a positive result does not prove by itself that active infection is present. It must be interpreted alongside symptoms, imaging and other test results.
Doctors may also use sputum testing, lung-function tests and, occasionally, bronchoscopy. Read more about how aspergillosis is diagnosed.
The 2026 review emphasised that diagnosis usually depends on combining imaging, Aspergillus-specific IgG and microbiological evidence with evidence of clinical progression.
Why specialist review may be helpful
Managing sarcoidosis and CPA together can be complicated. Treatment for sarcoidosis may involve corticosteroids or other medicines that suppress inflammation, while CPA may require prolonged antifungal treatment.
These medicines can interact with each other, and antifungal treatment may require monitoring for side effects, liver problems and drug levels. Some patients may need long-term antifungal treatment, particularly if disease is progressive or returns after treatment is stopped.
For this reason, unexpected deterioration, new cavities, progressive changes on CT, persistent systemic symptoms or haemoptysis may require discussion between respiratory, sarcoidosis and fungal-disease specialists.
What does this mean for someone with sarcoidosis?
Having sarcoidosis does not mean that you will develop aspergillosis. The association is most relevant in people with significant structural lung damage, particularly fibrosis or cavities.
It is worth telling your healthcare team if you develop:
- new or worsening breathlessness
- a persistent change in your cough
- unexplained weight loss or worsening fatigue
- repeated chest infections
- new changes on a chest X-ray or CT scan
- coughing up blood
- symptoms that continue despite treatment for sarcoidosis
These symptoms can have many causes, and they do not necessarily mean that you have aspergillosis. They simply deserve appropriate assessment rather than being automatically attributed to sarcoidosis.
Key message: Sarcoidosis and aspergillosis are separate conditions, but advanced sarcoidosis can sometimes cause lung changes in which chronic pulmonary aspergillosis develops. Most people with sarcoidosis will not develop CPA. When symptoms or scans change unexpectedly, considering both inflammation and infection can help doctors choose the safest treatment.
Related information
- Understanding chronic pulmonary aspergillosis
- How aspergillosis is diagnosed
- Understanding Aspergillus blood tests
- Diseases associated with aspergillosis
- Steroids and the immune system
Further reading
Recent review:
Jeny F, Brun S, Tran Ba S, Uzunhan Y.
Chronic pulmonary aspergillosis and sarcoidosis.
Current Opinion in Pulmonary Medicine, 2026.
Read the review on PubMed
.
Clinical study:
Uzunhan Y, Nunes H, Jeny F, et al.
Chronic pulmonary aspergillosis complicating sarcoidosis.
European Respiratory Journal. 2017;49:1602396.
Read the study on the ERS website
.
Earlier cohort and literature review:
Pena TA, Soubani AO, Samavati L.
Aspergillus lung disease in patients with sarcoidosis: a case series and review of the literature.
Lung. 2011;189:167–172.
Read the article information
.
This information is for education and should not replace advice from your own healthcare team.