

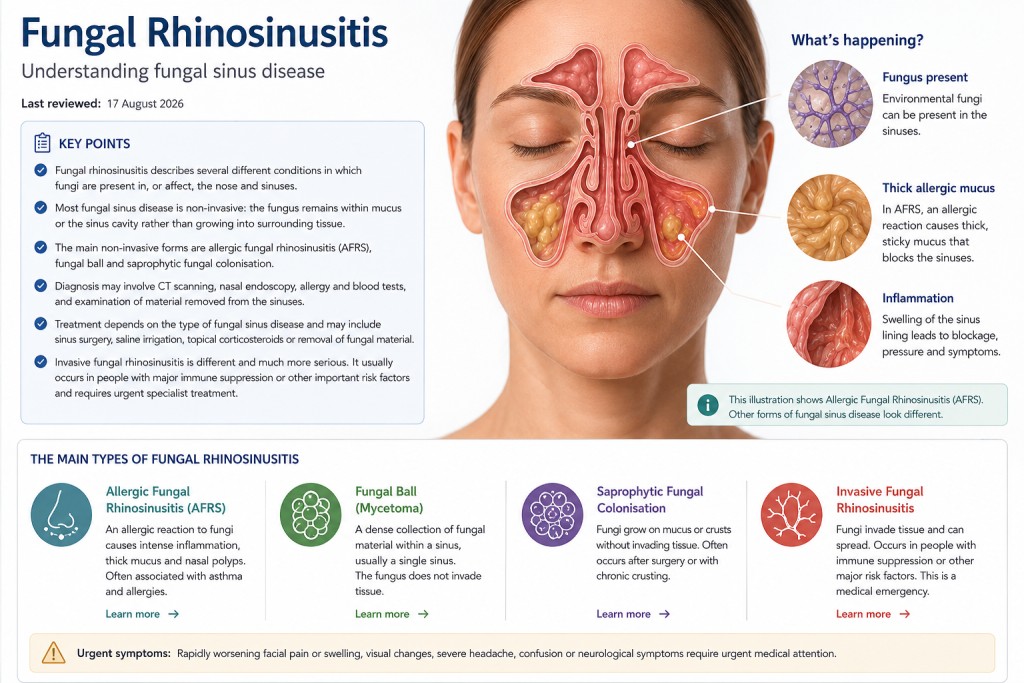
Fungal Rhinosinusitis
Last reviewed: 17 August 2026
Developed with patients
This information has been developed with patients and carers alongside clinical specialists. It is evidence based and regularly reviewed, and is intended to support—not replace—advice from your own healthcare team.
Key points
- Fungal rhinosinusitis describes several different conditions in which fungi are present in, or affect, the nose and sinuses.
- Most fungal sinus disease is non-invasive: the fungus remains within mucus or the sinus cavity rather than growing into surrounding tissue.
- The main non-invasive forms are allergic fungal rhinosinusitis (AFRS), fungal ball and saprophytic fungal colonisation.
- AFRS is an inflammatory and allergic condition associated with fungi and commonly occurs with nasal polyps, asthma and other allergic disease.
- Diagnosis may involve CT scanning, nasal endoscopy, allergy and blood tests, and examination of material removed from the sinuses.
- Treatment depends on the type of fungal sinus disease and may include sinus surgery, saline irrigation, topical corticosteroids or removal of fungal material.
- Invasive fungal rhinosinusitis is different and much more serious. It usually occurs in people with major immune suppression or other important risk factors and requires urgent specialist treatment.
Table of contents
- Overview
- Symptoms
- Diagnosis
- Types of fungal rhinosinusitis
- Allergic Fungal Rhinosinusitis (AFRS)
- Fungal Ball
- Saprophytic Fungal Colonisation
- Invasive Fungal Rhinosinusitis
- Outlook and recurrence
- Common questions
- When to seek medical advice
- Author and review information
- References and further reading
Overview
The sinuses are air-filled spaces in the skull around the nose, cheeks and forehead. They connect with the nasal passages and are lined with a thin layer of mucus-producing tissue.
Fungi are widespread in the environment, and everyone breathes in fungal spores. Usually this causes no problem. In some people, however, fungi can grow within mucus or debris in the sinuses, or contribute to an inflammatory or allergic response.
The term fungal rhinosinusitis describes a group of conditions rather than one single disease.
An important distinction is whether the fungus is non-invasive or invasive.
- Non-invasive fungal rhinosinusitis – fungi remain within mucus, crusts or the sinus cavity and do not invade healthy surrounding tissue.
- Invasive fungal rhinosinusitis – fungal hyphae grow into sinus tissue and may spread into surrounding structures. This is much less common but can be very serious.
The main non-invasive forms are:
- Allergic Fungal Rhinosinusitis (AFRS)
- Fungal ball
- Saprophytic fungal colonisation
These conditions behave differently and require different treatment, so identifying the type of fungal sinus disease is important.
Symptoms
Symptoms vary according to the type and severity of sinus disease. Non-invasive fungal rhinosinusitis can resemble ordinary chronic rhinosinusitis.
Symptoms may include:
- blocked or congested nose
- difficulty breathing through the nose
- thick nasal mucus
- post-nasal drip
- reduced or lost sense of smell
- facial pressure or discomfort
- headaches
- recurrent sinus problems
- fatigue or disturbed sleep
Some people with a fungal ball have surprisingly few symptoms, whereas AFRS can cause extensive sinus inflammation and nasal polyps.
Can I smell Aspergillus? Altered and phantom smells
Some people notice an unusual smell that seems to come from inside the nose—perhaps earthy, musty, herbal, smoky or like burning. It is understandable to wonder whether this means they can smell Aspergillus. Smell is not a reliable way to diagnose or monitor Aspergillus in the lungs.
Persistent sinus inflammation, blockage, mucus, crusting and nasal polyps can all affect the smell pathways. A person may have parosmia, where real smells seem different or unpleasant, or phantosmia, where they smell something that is not present. These changes can also occur after colds, flu or COVID-19, with allergies or sinusitis, and sometimes with medicines.
Fungal balls and other sinus conditions can be associated with altered smell, especially where a sinus is blocked or inflamed. If the fungal material is removed and normal drainage improves, the altered smell may improve too. We do not think the body is deliberately “compensating” by making a smell; rather, inflammation or disruption of the smell pathways can distort the signals reaching the brain.
Tell your GP or ENT team if a new smell persists, recurs, is mainly on one side, or occurs with nasal blockage, discharge, facial pressure or headaches. If someone close to you repeatedly notices a change in your breath around the time of a respiratory flare, it can be recorded as a personal early-warning sign, but should always be considered alongside your other symptoms and clinical tests.
Diagnosis
Persistent or complicated sinus disease is usually assessed by an ear, nose and throat (ENT) specialist.
Depending on the suspected condition, investigations may include:
- CT scanning – to identify blocked or expanded sinuses, accumulated mucus and characteristic dense material within the sinuses
- nasal endoscopy – allowing an ENT specialist to examine the nasal cavity and sinus openings
- blood tests – including total IgE, fungal-specific IgE and eosinophil levels where AFRS is suspected
- allergy testing – using blood tests or skin-prick testing to look for sensitisation to fungi and other allergens
- laboratory examination of sinus material or tissue – particularly when material is removed during surgery
There is no single blood test that can diagnose all forms of fungal rhinosinusitis. Results have to be interpreted alongside symptoms, endoscopic findings and imaging.
Types of fungal rhinosinusitis
Allergic Fungal Rhinosinusitis (AFRS)
What is AFRS?
Allergic fungal rhinosinusitis (AFRS) is a form of chronic rhinosinusitis with nasal polyps in which fungi are associated with a strong allergic and type 2 inflammatory response.
The sinuses may contain very thick, eosinophil-rich mucus containing fungal hyphae. Importantly, however, the fungi do not normally invade the surrounding healthy tissue.
Aspergillus species can be involved, but AFRS may also be associated with other environmental fungi.
AFRS commonly occurs in people who:
- have nasal polyps
- have asthma or other allergic disease
- show sensitisation to fungi
- have a functioning immune system rather than severe immune suppression
How is AFRS diagnosed?
There is currently no single test that confirms AFRS. Diagnosis is based on a combination of clinical findings, imaging, evidence of allergic inflammation and, where available, examination of sinus material.
Doctors may use:
- nasal endoscopy to identify polyps and thick allergic mucus
- CT imaging to identify characteristic changes within affected sinuses
- total IgE and fungal-specific IgE
- eosinophil measurements
- allergy testing
- microscopy, histology or other examination of material removed from the sinuses
Diagnostic criteria for AFRS have been used since the 1990s, but our understanding of the condition has changed substantially. Researchers are now reassessing these criteria and looking for more practical ways to recognise AFRS and distinguish it from other forms of chronic rhinosinusitis.
Read more in our update on how the diagnosis of allergic fungal rhinosinusitis is changing.
Treatment of AFRS
For many people with established AFRS, endoscopic sinus surgery followed by ongoing medical treatment remains the mainstay of management.
Surgery can:
- remove thick allergic mucus and fungal material
- remove obstructing nasal polyps
- open blocked sinus cavities
- allow saline irrigation and topical medicines to reach the affected sinuses more effectively
- provide material for laboratory and pathological examination
Long-term treatment after surgery commonly includes saline irrigation and topical corticosteroids to control inflammation and reduce recurrence.
Systemic corticosteroids, allergen immunotherapy, antifungal treatment and other therapies may be considered in selected patients, but their roles vary and treatment should be individualised.
Biologic treatments
There is growing interest in biologic medicines that target particular parts of type 2 inflammation. Medicines such as dupilumab, mepolizumab and omalizumab are already used in conditions including severe asthma and chronic rhinosinusitis with nasal polyps.
Studies in AFRS have so far been much smaller than those for chronic rhinosinusitis with nasal polyps more generally, but recent systematic reviews have found encouraging improvements in symptoms and measures of inflammation in people with difficult-to-treat AFRS.
Biologics may therefore become increasingly useful for selected people with recurrent or difficult-to-control disease, although more research is needed to establish exactly where they fit alongside surgery and other treatments.
AFRS and allergic bronchopulmonary aspergillosis (ABPA)
Some people with AFRS also have allergic bronchopulmonary aspergillosis (ABPA). Both conditions involve an exaggerated immune response to fungi and can occur in people with asthma or other allergic disease.
In AFRS, the inflammatory response mainly affects the nose and sinuses. In ABPA, it mainly affects the lungs and airways.
Having one condition does not mean that a person will develop the other. However, recognising the possible overlap is important, particularly when someone has both persistent sinus disease and respiratory symptoms.
If someone with AFRS also has asthma, bronchiectasis, recurrent chest symptoms or markedly raised IgE, clinicians may consider whether assessment for ABPA is appropriate.
For more information, visit our ABPA Knowledge Hub.
Fungal Ball
Overview
A fungal ball is a dense collection of fungal hyphae and debris that develops within a sinus. The older term mycetoma is sometimes used, although fungal ball is clearer because mycetoma also describes a different type of fungal disease affecting skin and deeper tissues.
The fungus remains within the sinus cavity and does not invade the surrounding tissue.
Fungal balls often affect a single sinus, particularly the maxillary sinus in the cheek or the sphenoid sinus deeper in the skull. Aspergillus species are frequently found.
Some people have few symptoms, while others experience nasal blockage, discharge, facial pressure, headaches or recurrent sinus problems.
Diagnosis
CT scanning may show characteristic dense or calcified material within the affected sinus. Diagnosis is usually confirmed when the fungal material is removed and examined.
Treatment
Treatment is usually surgical removal of the fungal material and opening of the affected sinus so that it can drain normally.
Antifungal medicines are not usually needed for an uncomplicated fungal ball because the fungus has not invaded the surrounding tissue.
Saprophytic Fungal Colonisation
Overview
Saprophytic fungal colonisation occurs when fungi grow on mucus or crusts within the nasal cavity or sinus openings without invading the underlying tissue.
It may occur after sinus surgery or where persistent crusting and retained mucus provide material on which fungi can grow.
This is generally a relatively minor form of fungal sinus disease.
Treatment
Treatment usually involves removing fungal crusts and debris and improving nasal hygiene with saline irrigation or other measures recommended by the ENT team.
Antifungal medicines are usually not required.
Invasive Fungal Rhinosinusitis
Invasive fungal rhinosinusitis is very different from AFRS, fungal ball and saprophytic colonisation. In invasive disease, fungal hyphae grow into the tissues of the nose and sinuses and can spread into surrounding structures.
Acute invasive fungal rhinosinusitis occurs mainly in people whose immune defences are severely impaired, for example because of some blood cancers, chemotherapy, transplantation, profound neutropenia or other significant immune suppression. Poorly controlled diabetes, particularly with ketoacidosis, is also an important risk factor for some invasive fungal infections.
Symptoms can progress rapidly and may include severe facial pain or swelling, fever, nasal or facial tissue changes, visual symptoms, severe headache or neurological symptoms.
Suspected invasive fungal rhinosinusitis is a medical emergency requiring urgent specialist assessment. Treatment may involve urgent surgery, systemic antifungal medication and treatment of the underlying condition that has increased susceptibility to infection.
Outlook and recurrence
The outlook varies considerably between the different types of fungal rhinosinusitis.
Fungal balls and saprophytic fungal colonisation can usually be treated successfully once the fungal material has been removed.
AFRS is different because the underlying inflammatory tendency remains. Recurrence after treatment is common, so long-term ENT follow-up, topical treatment and monitoring may be required even after successful surgery.
For many people, a combination of surgery and ongoing medical treatment substantially improves nasal obstruction, sinus drainage and other symptoms.
Common questions
Is fungal sinusitis contagious?
No. Fungal rhinosinusitis is not normally passed from one person to another. The fungi involved are generally organisms that are already widespread in the environment.
Does finding fungus mean I have a fungal infection?
Not necessarily. Fungi can be present in the nose and sinuses without invading tissue. In AFRS, much of the disease results from the immune and inflammatory response associated with fungi rather than invasive fungal growth.
Do antifungal medicines always treat fungal sinusitis?
No. Treatment depends on the type of fungal rhinosinusitis. Antifungal medication is generally not required for an uncomplicated fungal ball or saprophytic colonisation, while AFRS management primarily focuses on surgery where necessary and control of inflammation. Invasive fungal disease is different and requires systemic antifungal treatment.
Is fungal rhinosinusitis linked to asthma?
AFRS is strongly associated with allergic disease, and many people with AFRS also have asthma. A smaller number may also have ABPA, in which a related allergic response to fungi affects the lungs.
Can AFRS come back after surgery?
Yes. AFRS has a significant tendency to recur. Surgery removes accumulated material and opens the sinuses, but it does not remove the underlying tendency towards inflammation. Long-term topical treatment and follow-up are therefore important.
Are biologics replacing sinus surgery?
Not at present. Biologic medicines are promising for some people with severe or recurrent AFRS, particularly when there is associated type 2 inflammatory disease such as asthma or nasal polyposis. However, surgery remains an important part of treatment for many patients with established AFRS.
When to seek medical advice
Speak to a healthcare professional if you have:
- sinus symptoms persisting for more than 12 weeks
- persistent nasal blockage
- recurrent sinus problems despite treatment
- significant loss of smell
- persistent facial pressure or pain
- asthma that becomes more difficult to control alongside worsening sinus disease
Seek urgent medical assessment for rapidly worsening facial pain or swelling, visual disturbance, severe headache, neurological symptoms or rapidly progressive sinus symptoms, particularly if you are significantly immunocompromised.
Related information
Browse the Aspergillosis Knowledge Hub
Learn about ABPA
Visit the SAFS Hub
Learn about treatment for aspergillosis
Author and review information
Author: Aspergillosis Website Editorial Team
Audience: Patients, carers, GPs and non-specialists
Last reviewed: 17 August 2026
References and further reading
- Roland LT, Damask C, Luong AU, et al. Allergic Fungal Rhinosinusitis Diagnosis, Management, Associated Conditions, Pathophysiology, and Future Directions: Summary of a Multidisciplinary Workshop. International Forum of Allergy & Rhinology. 2025;15(6):626-641. PubMed PMID: 40310935.
- Allergic Fungal Rhinosinusitis: A Contemporary Update. 2025. PubMed PMID: 40491076.
- Im YH, Stybayeva G, Hwang SH. Short-Term Efficacy of Biologics in Recalcitrant Allergic Fungal Rhinosinusitis: A Systematic Review and Meta-analysis. Otolaryngology–Head and Neck Surgery. 2025;173(4):840-847. PubMed PMID: 40552669.
- Aljubran HJ, Bamalan OA, Alfayez AA, et al. The evaluation of therapeutic outcomes of biologics in allergic fungal rhinosinusitis: a systematic review and meta-analysis. Rhinology. 2025;63(1):118-120. PubMed PMID: 39484735.
- Fokkens WJ, Lund VJ, Hopkins C, et al. European Position Paper on Rhinosinusitis and Nasal Polyps 2020. Rhinology. 2020;58(Suppl S29):1-464. PubMed PMID: 32077450.
- deShazo RD, Swain RE. Diagnostic criteria for allergic fungal sinusitis. Journal of Allergy and Clinical Immunology. 1995;96(1):24-35. PubMed PMID: 7622760.


Sinusitis Hub
Fungal disease of the nose and sinuses can take several different forms. Some conditions are mainly allergic or inflammatory, while others involve fungal material growing within a sinus. Invasive fungal sinus disease is much less common but can be serious.
This hub brings together our main information about fungal rhinosinusitis, including allergic fungal rhinosinusitis (AFRS), fungal balls, invasive disease, nasal polyps, diagnosis and treatment.
Start here: fungal rhinosinusitis
If you are new to the subject, begin with our main guide. It explains the different types of fungal sinus disease, common symptoms, how they are investigated and how treatment differs between them.
- Fungal Rhinosinusitis: Types, Symptoms, Diagnosis and Treatment
Our main patient and carer guide to allergic fungal rhinosinusitis (AFRS), fungal ball, fungal colonisation and invasive fungal rhinosinusitis.
More detailed information
For expert patients and non-specialist clinicians
Some readers may want more clinical detail about diagnosis, imaging, tissue invasion, microbiology and treatment.
- Aspergillus Sinusitis for Expert Patients and non-Specialist Clinicians
A more detailed clinical guide covering non-invasive and invasive Aspergillus sinus disease, investigations and treatment.
Allergic fungal rhinosinusitis (AFRS)
AFRS is a form of chronic rhinosinusitis with nasal polyps in which fungi are associated with a strong allergic and inflammatory response. Diagnosis usually depends on a combination of symptoms, imaging, endoscopy, allergy testing and examination of sinus material rather than one single test.
- Allergic Fungal Rhinosinusitis: How Diagnosis Is Changing
A closer look at evolving diagnostic criteria, newer tests and research aimed at recognising AFRS more accurately.
Nasal polyps, asthma and biologic treatment
Nasal polyps and asthma often involve overlapping inflammatory pathways. Some people with recurrent polyps, severe asthma or ABPA may therefore be considered for biological treatments that target specific parts of the immune response.
- Could One Biologic Treat Nasal Polyps, Asthma and ABPA?
An explanation of recurrent nasal polyps, type 2 inflammation and how treatments such as dupilumab may sometimes benefit more than one part of the airway.
Understanding the different types
The term fungal rhinosinusitis describes several different conditions rather than one single disease.
- Allergic fungal rhinosinusitis (AFRS) — an allergic and inflammatory condition, usually associated with nasal polyps and fungal sensitisation.
- Fungal ball — a collection of fungal material within a sinus without invasion of surrounding tissue.
- Saprophytic fungal colonisation — fungal growth on mucus or crusts, sometimes following sinus surgery.
- Invasive fungal rhinosinusitis — fungal growth into sinus tissue. This is much less common but may be serious and requires specialist treatment.
Read the full guide to the different types of fungal rhinosinusitis.
Symptoms and diagnosis
Symptoms can overlap with ordinary chronic rhinosinusitis and may include nasal blockage, thick mucus, post-nasal drip, reduced sense of smell, facial pressure, headaches and recurrent sinus problems.
Assessment may involve an ENT examination, nasal endoscopy, CT scanning, blood and allergy tests and, in some cases, laboratory examination of sinus material or tissue.
There is no single test that diagnoses every form of fungal rhinosinusitis, so results need to be interpreted together.
Treatment
Treatment depends on the type of sinus disease. It may involve:
- saline irrigation and nasal treatments;
- topical corticosteroids to control inflammation;
- endoscopic sinus surgery to remove obstructing material or polyps and improve drainage;
- biological medicines in selected people with severe inflammatory disease; or
- systemic antifungal treatment and urgent specialist care for invasive fungal disease.
Antifungal medicines are not needed for every type of fungal sinus disease. Treatment should be matched to the diagnosis.
When to seek medical advice
Speak to a healthcare professional if you have persistent or recurrent sinus symptoms, significant loss of smell, ongoing nasal blockage or facial pressure, particularly when symptoms have lasted for several weeks or are not responding to usual treatment.
Seek urgent medical assessment for rapidly worsening facial pain or swelling, visual disturbance, severe headache, neurological symptoms or rapidly progressive sinus symptoms, especially if you are significantly immunocompromised.
Related hubs
- ABPA Knowledge Hub
- Severe Asthma with Fungal Sensitisation (SAFS) Hub
- Symptoms Hub
- Treatment for Aspergillosis
Support and community
Living with aspergillosis can feel isolating. There are several ways for patients, carers, families and supporters to find reliable information, meet others who understand and stay connected.
Online meetings
Join our weekly informal support meetings or the longer monthly NAC support meeting.
Online community
Connect with others through the aspergillosis Facebook support community and Telegram discussion group.
Support for carers
Information and practical support for family members, friends and carers.
Support that fits your needs
You do not need to take part in everything. Some people prefer a live meeting; others find written information, a Facebook group, Telegram discussion or support for carers more useful. You are welcome to use whichever options feel right for you.
Our meetings and online communities offer information, peer support and a chance to share experiences. They do not replace advice from your own healthcare team.
Find mental health and emotional wellbeing support
Other forms of aspergillosis: Aspergilloma (Fungal Ball in the Lung)
An aspergilloma is a ball of fungal material that grows inside an existing cavity in the lung. It is most often caused by Aspergillus, a common mould found in the environment.
It is not cancer, and it does not usually mean that fungus is invading healthy lung tissue. However, an aspergilloma can cause important problems, especially coughing up blood, and needs assessment by a respiratory specialist.
Developed with patients
This information has been developed with patients and carers alongside clinical specialists. It is evidence based and regularly reviewed, and is intended to support—not replace—advice from your own healthcare team.
Key points
- An aspergilloma is a fungal ball growing inside a pre-existing lung cavity.
- It most often occurs in lungs already affected by conditions such as previous tuberculosis, COPD, sarcoidosis, bronchiectasis or prior lung surgery.
- Some people have few or no symptoms; others have cough, breathlessness or coughing up blood.
- Any coughing up of blood should be reported to your healthcare team.
- Scans, blood tests and sometimes sputum tests help doctors confirm the diagnosis and look for associated chronic pulmonary aspergillosis (CPA).
- Treatment depends on symptoms, bleeding, lung function and the wider condition of the lungs.
What is an aspergilloma?
An aspergilloma forms when fungal threads, mucus and other material collect inside a space that is already present in the lung. The space is usually a cavity left by an earlier lung problem.
The fungal ball may move within the cavity when a person changes position. It is usually identified on a chest X-ray or, more clearly, on a CT scan.
Aspergilloma is often part of the wider spectrum of chronic pulmonary aspergillosis (CPA), but not everyone with a fungal ball has progressive CPA. Specialist assessment helps establish what is happening in each individual case.
Who is at risk?
An aspergilloma can develop when a lung cavity has formed because of an earlier illness or treatment. Conditions that may leave cavities or significant lung damage include:
- Previous tuberculosis (TB) or another serious lung infection
- Chronic pulmonary aspergillosis
- COPD or emphysema
- Sarcoidosis
- Bronchiectasis
- Previous lung surgery or radiotherapy
Most people who have one of these conditions will not develop an aspergilloma.
Symptoms
Some aspergillomas cause no symptoms and are found during a scan for another reason. Others may be associated with:
- Persistent cough
- Breathlessness
- Tiredness or reduced exercise tolerance
- Repeated chest infections
- Coughing up blood, known as haemoptysis
Symptoms can also be caused by the underlying lung condition, so it is important not to assume that every symptom is caused by the fungal ball itself.
Coughing up blood: when to get help
Coughing up blood is the most important potential complication of an aspergilloma. Even small streaks of blood in sputum should be reported promptly to your respiratory team or GP, particularly if this is new or becoming more frequent.
Call 999 or go to A&E immediately if bleeding is heavy, ongoing, increasing quickly, or occurs with severe breathlessness, chest pain, faintness or a rapid deterioration in how you feel.
Do not stop or change prescribed medicines, including blood-thinning medicines, without medical advice. Tell the emergency or respiratory team about all medicines you take.
How is an aspergilloma diagnosed?
Doctors combine symptoms, scans and laboratory tests. An aspergilloma can sometimes resemble another lung problem on an X-ray or CT scan, so careful assessment is important.
Tests may include:
- A chest X-ray and CT scan
- Blood tests, including Aspergillus IgG antibodies
- Sputum culture or PCR testing where a sample can be produced
- Comparison with previous scans
- Further tests where cancer, tuberculosis, non-tuberculous mycobacterial infection or another cause needs to be excluded
Your local respiratory team may seek specialist advice when the diagnosis is uncertain, bleeding is recurrent, or treatment options are complex.
Treatment and monitoring
Treatment is tailored to the individual. Decisions depend on whether there is bleeding, the severity of symptoms, whether the fungal ball is stable on scans, lung function and whether there is associated CPA.
Monitoring
If an aspergilloma is stable and not causing significant symptoms or bleeding, regular clinical and scan follow-up may be the safest approach. Your team will advise how often this is needed.
Antifungal medicines
Antifungal treatment is not automatically needed for every simple aspergilloma. It may be considered when there is associated CPA or another reason to treat active Aspergillus-related disease.
Antifungal medicines can interact with many other drugs and often need blood tests and monitoring. The choice of medicine should be made with your specialist team.
Controlling bleeding
If bleeding is significant, doctors may use medicines and urgent procedures to control it. Bronchial artery embolisation is a procedure that blocks abnormal blood vessels supplying the area of bleeding. It can be very effective, although bleeding can sometimes recur.
Surgery
For carefully selected people, surgery to remove the cavity and fungal ball can offer the best chance of a long-term cure. It is only suitable when the likely benefit outweighs the risks, including the effect of surgery on remaining lung function.
Living with an aspergilloma
Looking after the underlying lung condition remains important. This may include taking medicines as prescribed, attending follow-up appointments, keeping up with airway-clearance treatment where relevant, and seeking help promptly for changing symptoms.
It is sensible to reduce exposure to obvious dust, damp and mould where practical, but you do not need to avoid ordinary life or outdoor activities altogether. Aspergillus spores are widespread in the environment and most people encounter them every day.
Related information
Visit the Aspergilloma (Fungal Ball) Hub
Learn about chronic pulmonary aspergillosis (CPA)
Learn about treatment for aspergillosis
Browse the Aspergillosis Knowledge Hub
References
- Brown JS, Armstrong-James D, Ayling-Smith J, et al. British Thoracic Society Clinical Statement on Aspergillus-related chronic lung disease. Thorax. 2025;80(Suppl 1):3–21.
- Patterson TF, Thompson GR, Denning DW, et al. Practice guidelines for the diagnosis and management of aspergillosis. Clinical Infectious Diseases. 2016;63:e1–e60.
Last reviewed: September 2026

Severe Asthma with Fungal Sensitisation (SAFS)
Severe asthma with fungal sensitisation (SAFS) is a form of difficult-to-control asthma in which the immune system reacts to fungi in the environment, including Aspergillus.
People with SAFS have severe asthma and evidence of fungal allergy, but do not have the fuller pattern of allergic lung disease seen in allergic bronchopulmonary aspergillosis (ABPA).
Developed with patients
This information has been developed with patients and carers alongside clinical specialists. It is evidence based and regularly reviewed, and is intended to support—not replace—advice from your own healthcare team.
Key points
- SAFS means severe asthma alongside sensitivity or allergy to one or more fungi.
- It is different from ABPA, although the conditions can overlap and share some features.
- Symptoms are those of severe, poorly controlled asthma: wheeze, cough, breathlessness, chest tightness and frequent flare-ups.
- There is no single test for SAFS. Diagnosis involves confirming fungal sensitisation and carefully excluding ABPA and other causes.
- Treatment focuses first on the best possible severe-asthma care.
- Antifungal medicines may help selected people, but are not suitable or necessary for everyone.
What is SAFS?
Fungal spores are a normal part of the air around us, indoors and outdoors. Most people breathe them in without becoming ill. In some people with asthma, however, the immune system recognises proteins from fungi as allergens. This can add to airway inflammation and make asthma harder to control.
SAFS is usually considered when someone has severe asthma, evidence of fungal sensitisation and no clear evidence of ABPA. Fungi linked with airway allergy can include Aspergillus, Alternaria, Cladosporium and Penicillium.
SAFS is an area of active research. It is useful as a clinical description, but it does not mean that every person with fungal allergy has a fungal infection or needs antifungal treatment.
How is SAFS different from ABPA?
Both SAFS and ABPA involve an immune reaction to fungi, often Aspergillus. The difference is in the overall pattern of illness and test results.
- SAFS involves severe asthma and fungal sensitisation, without the full diagnostic features of ABPA.
- ABPA is a more specific allergic lung condition. It can involve very high total IgE, mucus plugging, characteristic scan changes and bronchiectasis.
These conditions are sometimes described as being on a spectrum. That does not mean that everyone with SAFS will develop ABPA. Many people remain stable with SAFS, particularly when their asthma is well managed.
Who may be affected?
SAFS is considered in people whose asthma remains difficult to control despite appropriate treatment. It may be more likely when a person has:
- Frequent asthma flare-ups or courses of oral steroids
- Ongoing symptoms despite high-dose inhaled treatment
- Evidence of fungal allergy on a skin-prick or blood test
- A history suggesting that symptoms worsen at particular times of year or in certain environments
Environmental damp or obvious mould may worsen symptoms for some people, but it is often impossible to prove exactly how much fungal exposure contributes in one individual. Trying to avoid all fungi is neither realistic nor necessary.
Symptoms
The symptoms of SAFS are usually those of severe, difficult-to-control asthma. They can include:
- Wheeze
- Breathlessness
- Chest tightness
- Persistent cough
- Night-time asthma symptoms
- Frequent flare-ups or the need for rescue steroid courses
- Asthma that responds less well than expected to usual treatment
These symptoms are not specific to SAFS. Asthma can be worsened by infections, inhaler technique, smoking, reflux, rhinitis, anxiety, dysfunctional breathing and many other factors. A thorough severe-asthma assessment is important.
How is SAFS diagnosed?
There is no single test that proves SAFS. Diagnosis is based on the whole clinical picture and is usually made by a respiratory or severe-asthma specialist.
Assessment may include:
- A review of asthma symptoms, flare-ups and current treatment
- Checking inhaler technique and whether treatment is being taken regularly
- Skin-prick testing or blood tests for fungus-specific IgE
- Total IgE and eosinophil blood tests
- Lung-function testing
- A chest X-ray or CT scan if needed to look for mucus plugging, bronchiectasis or another diagnosis
- Assessment for ABPA and other Aspergillus-related conditions
Treatment
Treatment is individual and begins with the best possible management of severe asthma. The aim is to reduce symptoms and flare-ups, improve day-to-day life and minimise the need for oral steroids where possible.
Optimising asthma care
This may include reviewing inhaler technique, regular use of prescribed inhalers, trigger management and treatment of related problems such as allergic rhinitis, reflux or dysfunctional breathing.
Airway clearance may be useful for people who also have troublesome mucus or bronchiectasis, but it is not needed by everyone with SAFS.
Biologic medicines
Biologic medicines are now an important option for many people with severe asthma. The most suitable treatment depends on the individual asthma pattern, including allergy, eosinophil count, flare-up history and other health conditions.
Examples include omalizumab, mepolizumab, benralizumab, dupilumab and tezepelumab. A severe-asthma specialist can discuss whether a biologic is appropriate and what benefit to expect.
Oral steroids
Short courses of oral steroids may be needed for severe flare-ups. Long-term oral steroid treatment is generally avoided where possible because it can cause significant side effects. If regular steroid courses are needed, it is worth asking for a specialist review of the overall asthma plan.
Antifungal medicines
Antifungal medicines, such as itraconazole, may help some carefully selected people with SAFS. However, the benefit is variable and the evidence is less certain than for standard severe-asthma treatments.
Antifungals can interact with many other medicines and may need liver-function tests and drug-level monitoring. They should only be started after a specialist discussion of the likely benefits, risks and alternatives.
What can I do about mould and fungal exposure?
It is sensible to reduce avoidable exposure to obvious damp and mould in the home. Repairing leaks, improving ventilation and reducing condensation can all support respiratory health.
Some people notice symptoms when gardening or around compost, mulch or decaying plant material. If this happens to you, practical measures such as avoiding direct handling, asking someone else to do the task or wearing appropriate protection may help. There is no need to become fearful of ordinary outdoor life: fungi are naturally present everywhere.
When should I seek medical advice?
Speak to your GP, asthma nurse or respiratory team if your asthma remains poorly controlled, you are having repeated flare-ups, you need frequent courses of oral steroids, or you have questions about fungal allergy, ABPA or antifungal medicines.
Seek urgent help if you are severely breathless, cannot speak in full sentences, have blue lips, feel confused or drowsy, or your reliever inhaler is not helping as expected.
Related information
Visit the SAFS / Severe Asthma with Fungal Sensitisation Hub
Learn about ABPA
Learn about Aspergillus bronchitis
Learn about treatment for aspergillosis
Browse the Aspergillosis Knowledge Hub
References
- Brown JS, Armstrong-James D, Ayling-Smith J, et al. British Thoracic Society Clinical Statement on Aspergillus-related chronic lung disease. Thorax. 2025;80(Suppl 1):3–21.
- Moss RB. Severe fungal asthma: a role for biologics and inhaled antifungals. Journal of Fungi. 2023;9(1):85.
- Rapeport WG, Ito K, Denning DW. The role of antifungals in the management of patients with severe asthma. Clinical and Translational Allergy. 2020;10:46.
Last reviewed: September 2026
Medical review: specialist review recommended before publication

Aspergillus Bronchitis
Aspergillus bronchitis is a long-term infection of the larger airways (bronchi) caused by Aspergillus mould. It is most often seen in people who already have damaged or widened airways, particularly bronchiectasis or cystic fibrosis.
It can cause persistent cough, sputum, breathlessness and repeated chest symptoms. It is different from an allergic condition such as ABPA, and from chronic pulmonary aspergillosis (CPA), which affects the lung tissue rather than mainly the airways.
Developed with patients
This information has been developed with patients and carers alongside clinical specialists. It is evidence based and regularly reviewed, and is intended to support—not replace—advice from your own healthcare team.
Key points
- Aspergillus bronchitis is a chronic infection affecting the larger airways.
- It is most often associated with bronchiectasis, cystic fibrosis or other long-term airway damage.
- It is not the same as ABPA, which is an allergic reaction to Aspergillus.
- A single positive sputum result does not always mean that treatment is needed.
- Diagnosis depends on symptoms, repeated test results, scans and excluding other causes.
- Treatment may include antifungal medicine, airway clearance and management of the underlying lung condition.
What is Aspergillus bronchitis?
People breathe in Aspergillus spores every day. In most people, the lungs and immune system remove them without causing illness.
When the airways are already damaged or do not clear mucus well, Aspergillus can sometimes persist in the sputum and contribute to ongoing airway symptoms. This is called Aspergillus bronchitis.
The term is used by specialist teams for a pattern of persistent symptoms and repeated positive samples. It is not diagnosed from one sputum sample alone.
How does it differ from other Aspergillus-related conditions?
- Colonisation means Aspergillus has been found in a sample but may not be causing illness.
- Aspergillus bronchitis means the fungus is thought to be contributing to persistent airway symptoms or inflammation.
- ABPA is an allergic immune reaction to Aspergillus, usually associated with asthma or cystic fibrosis.
- CPA is a longer-term infection affecting the lung tissue, often with cavities or nodules on scans.
- Invasive aspergillosis is a serious infection that usually affects people with major immune suppression.
More than one lung condition can be present at the same time. This is one reason that specialist assessment is sometimes needed.
Who is most likely to be affected?
Aspergillus bronchitis is most often considered in people with long-term airway disease, including:
- Bronchiectasis
- Cystic fibrosis
- Chronic mucus production or difficulty clearing sputum
- Some forms of severe COPD or chronic airway inflammation
It is not contagious and cannot be passed from person to person.
Symptoms
Symptoms often overlap with bronchiectasis, asthma, COPD and bacterial chest infections. They may include:
- Persistent or worsening cough
- More sputum, or thicker and stickier sputum
- Breathlessness or wheeze
- Repeated chest symptoms that do not improve as expected with antibiotics
- Increasing difficulty clearing mucus
- Fatigue or feeling generally unwell during flare-ups
These symptoms do not prove Aspergillus bronchitis. They are a reason to discuss sputum results and ongoing symptoms with your respiratory team.
How is it diagnosed?
Diagnosis is based on the whole picture, rather than any one test. Doctors may consider:
- Persistent airway symptoms, especially when they have not improved as expected
- Repeated detection of Aspergillus in sputum culture or PCR testing
- Blood tests, including Aspergillus IgG antibodies where appropriate
- CT scans to assess bronchiectasis, mucus plugging and other changes in the lungs
- Whether ABPA, CPA, bacterial infection or another cause better explains the symptoms
A bronchoscopy is occasionally needed, but not for everyone. It may help when sputum cannot be produced or when the diagnosis remains unclear.
Treatment
Treatment is individual. Not everyone with a positive sputum sample needs an antifungal medicine. The aim is to improve symptoms, reduce the fungal burden where relevant and protect the airways.
Antifungal medicines
When treatment is appropriate, this may include an oral antifungal such as itraconazole. Other medicines, including voriconazole or posaconazole, may be considered when needed.
Antifungals can interact with other medicines and may affect the liver. Your team may arrange blood tests, drug-level monitoring and a review of all your current medicines. The length of treatment and whether it is helping should be reviewed with you regularly.
Airway clearance
Clearing mucus is an important part of care for many people with Aspergillus bronchitis and bronchiectasis. A respiratory physiotherapist can help identify techniques that suit you, such as breathing techniques, devices or nebulised treatment where appropriate.
Managing the underlying lung condition
Good bronchiectasis, asthma or COPD care remains essential. This may include inhaler review, vaccination, regular sputum testing, treatment of bacterial infections and support with airway clearance.
When should I speak to my healthcare team?
Contact your GP, respiratory team or specialist nurse if you have persistent or worsening cough, increasing sputum, repeated chest symptoms, or a sputum result showing Aspergillus that you do not understand.
Seek urgent medical advice for severe breathlessness, significant or repeated coughing up of blood, chest pain, or a rapid deterioration in how you feel.
Related information
Visit the Aspergillus Bronchitis Hub
Learn about ABPA
Learn about chronic pulmonary aspergillosis (CPA)
Learn about treatment for aspergillosis
Browse the Aspergillosis Knowledge Hub
References
- European Respiratory Society clinical practice guideline for the management of adult bronchiectasis
- Chotirmall SH, Al-Alawi M, Mirkovic B, et al. Aspergillus-associated airway disease, inflammation, and the innate immune response. BioMed Research International. 2013;2013:723129.
Last reviewed: September 2026

Invasive Aspergillosis
Invasive aspergillosis is a serious fungal infection caused by Aspergillus mould. It usually affects people whose immune system is severely weakened by illness or medical treatment.
It is very different from chronic pulmonary aspergillosis (CPA), ABPA and other long-term forms of aspergillosis. Most people with asthma, bronchiectasis, ABPA or CPA are not at risk of invasive aspergillosis unless they also have major immune suppression or are seriously unwell.
Invasive aspergillosis needs prompt specialist assessment and treatment, usually in hospital.
Developed with patients
This information has been developed with patients and carers alongside clinical specialists. It is evidence based and regularly reviewed, and is intended to support—not replace—advice from your own healthcare team.
Key points
- Invasive aspergillosis is uncommon but can be life-threatening.
- It mainly affects people with major immune suppression or critical illness.
- It usually starts in the lungs but can sometimes spread to other parts of the body.
- Fever, worsening breathlessness, chest pain or coughing up blood in someone at high risk need urgent medical advice.
- Diagnosis and treatment require a specialist hospital team.
Who is at risk?
Invasive aspergillosis is most likely to occur when the body cannot control fungal spores that are breathed in from the environment.
People at higher risk include those who have:
- Leukaemia, lymphoma or another blood cancer, particularly during intensive chemotherapy
- Very low neutrophil levels (neutropenia)
- A stem-cell or bone-marrow transplant
- A solid-organ transplant, especially a lung transplant
- High-dose steroids or other strong immune-suppressing medicines
- A severe immune deficiency
- A stay in intensive care, especially following severe influenza, COVID-19 or another serious viral pneumonia
Some people with very severe lung disease, particularly when they are acutely unwell or receiving substantial steroid treatment, may also be at increased risk.
What are the symptoms?
Symptoms vary and can be caused by many other illnesses. In someone at higher risk, clinicians may be particularly concerned about:
- Fever that persists or does not improve as expected
- New or worsening cough
- Increasing breathlessness
- Chest pain, especially when breathing in
- Coughing up blood
- Marked tiredness or weakness
If infection has spread beyond the lungs, it can sometimes cause symptoms such as severe headache, confusion, visual changes or unusual skin lesions.
When should I seek urgent help?
If you have a severely weakened immune system, are having chemotherapy, have recently had a transplant, or have been advised that you are at high risk, contact your hospital team urgently if you develop a persistent fever, worsening breathlessness, chest pain or cough up blood.
Seek emergency help if you are severely breathless, confused, faint, coughing up a significant amount of blood, or otherwise rapidly becoming more unwell.
For people who are not in a high-risk group, these symptoms are far more likely to have another cause. However, they should still be discussed with a healthcare professional if they are new, severe or worsening.
How is invasive aspergillosis diagnosed?
There is no single test that proves every case. Doctors combine information about a person’s immune system, symptoms, scans and laboratory results.
Tests may include:
- A CT scan of the chest
- Blood tests, including galactomannan or beta-D-glucan where appropriate
- Sputum testing
- A bronchoscopy sample, sometimes called bronchoalveolar lavage (BAL)
- Fungal culture, microscopy or PCR testing
- Occasionally, a tissue biopsy
Finding Aspergillus in a sample does not always mean it is causing invasive disease. Specialists consider the whole clinical picture before reaching a diagnosis.
How is it treated?
Treatment is usually started in hospital and is guided by infectious-disease, respiratory, haematology, transplant or intensive-care specialists.
Antifungal medicines may include:
- Voriconazole
- Isavuconazole
- Liposomal amphotericin B
The best treatment depends on the person’s condition, other medicines, kidney and liver function, possible resistance and the type of immune suppression involved. Drug levels and side effects often need careful monitoring.
Treatment also involves addressing the underlying reason the immune system is weakened where this can be done safely. This may mean treating neutropenia, reviewing immune-suppressing medicines or managing the illness that led to intensive-care admission.
Treatment often continues for several weeks or longer, depending on the response and recovery of the immune system.
Is invasive aspergillosis contagious?
No. It does not pass from person to person.
People develop invasive aspergillosis when they breathe in common Aspergillus spores at a time when their immune defences are too weak to clear them. Healthy people breathe in these spores every day without becoming ill.
How does it differ from other forms of aspergillosis?
- ABPA is an allergic reaction to Aspergillus, usually in people with asthma or cystic fibrosis.
- CPA is a long-term infection that develops over months in lungs that are already damaged.
- Invasive aspergillosis is a rapidly progressive infection, usually in people with major immune suppression.
Learn about ABPA
Learn about chronic pulmonary aspergillosis (CPA)
Learn about treatment for aspergillosis
More information
The Aspergillosis Knowledge Hub brings together reliable information on the different forms of aspergillosis, tests, treatments, symptoms and living with a long-term lung condition.
References
- Infectious Diseases Society of America: Clinical Practice Guideline for Aspergillosis
- ECMM guidance on invasive fungal infections
More information
Visit the Invasive & Acute Aspergillosis Hub
The Aspergillosis Knowledge Hub brings together reliable information on the different forms of aspergillosis, tests, treatments, symptoms and living with a long-term lung condition.
Last reviewed: September 2026

Allergic Bronchopulmonary Aspergillosis (ABPA)
Allergic bronchopulmonary aspergillosis (ABPA) is an allergic lung condition caused by an exaggerated immune response to Aspergillus mould. It most often affects people with asthma, bronchiectasis or cystic fibrosis. It is not the same as an invasive fungal infection.
People with ABPA may experience worsening asthma, cough, wheeze, breathlessness, fatigue and thick mucus or mucus plugs. Symptoms can fluctuate, with quieter periods and flare-ups.
Patient-centred information from the National Aspergillosis Centre. This guide combines specialist clinical knowledge with the questions, experiences and practical concerns raised by people living with ABPA and their carers.
Key points
- ABPA is an allergic reaction to Aspergillus in the airways.
- It is most commonly associated with asthma, bronchiectasis or cystic fibrosis.
- Diagnosis depends on several pieces of evidence; no single test gives the whole answer.
- Treatment is individual and may include anti-inflammatory treatment, antifungal medicine, asthma care and monitoring.
- Regular follow-up helps identify flare-ups, treatment side effects and lung changes early.
What happens in ABPA?
Aspergillus spores are common in the air and most people breathe them in without harm. In ABPA, the immune system reacts too strongly in the airways. This can cause inflammation, swelling and excess mucus. Over time, repeated inflammation can contribute to bronchiectasis or other lung changes.
Read: What is aspergillosis? →
Symptoms of ABPA
Symptoms vary between people and can overlap with asthma or bronchiectasis. They may include:
- worsening cough, wheeze, chest tightness or breathlessness;
- thick sputum, sometimes brown, or mucus plugs;
- fatigue, feverishness or generally feeling unwell;
- recurrent chest symptoms or asthma flare-ups; and
- coughing up blood in some cases.
Contact your clinical team if symptoms are new, worsening or different from your usual pattern. Seek urgent medical help for significant or repeated coughing up of blood, rapidly worsening breathlessness or severe illness.
How is ABPA diagnosed?
ABPA can be difficult to recognise because many symptoms are shared with asthma, bronchiectasis and other lung conditions. Clinicians consider the whole picture: symptoms and medical history, scans, blood tests and sometimes sputum results.
Current international guidance uses evidence of sensitisation to Aspergillus, total IgE and additional supporting evidence such as Aspergillus-specific IgG, eosinophils or characteristic imaging. These results must be interpreted together by the clinical team; a result above or below one threshold does not diagnose ABPA by itself.
Treatment and monitoring
The aim is to control inflammation, improve symptoms, prevent further lung damage and reduce the risk of flare-ups. Treatment depends on your symptoms, tests, scan findings, other lung conditions and previous response to treatment.
Depending on the individual, a plan may include asthma treatment, corticosteroids or other anti-inflammatory treatment, antifungal medicine, airway-clearance support and regular monitoring. Biologic medicines may be considered for selected people, particularly where asthma or allergic inflammation remains difficult to control. Decisions about treatment and any changes to prescribed medicine should be made with your clinical team.
Monitoring may include symptoms, total IgE and other blood tests, scans, lung function, sputum tests and drug-safety or drug-level checks where relevant.
Read more about treatment and management →
Living with ABPA
ABPA can bring practical as well as medical challenges: fatigue, uncertainty, treatment burden, anxiety about flare-ups and the work of managing asthma or bronchiectasis alongside it. Many people find that pacing, airway clearance where advised, keeping notes for appointments and support from others make a real difference.
Further ABPA information
- Asthma and aspergillosis
- Which type of aspergillosis do I have?
- Search the Knowledge Hub for more ABPA information
Common questions
Is ABPA contagious?
No. ABPA is not passed from person to person.
Is ABPA the same as a fungal infection?
No. ABPA is mainly an allergic immune response. It is different from chronic or invasive forms of aspergillosis, although antifungal medicine may be part of treatment for some people.
Can ABPA come back after treatment?
Some people have flare-ups or need treatment changes over time. This is why regular review and monitoring are important.
Last reviewed: September 2026

Chronic Pulmonary Aspergillosis (CPA)
Chronic pulmonary aspergillosis (CPA) is a long-term infection caused by Aspergillus mould in people whose lungs have usually been damaged by another condition. It develops gradually and can affect one or both lungs. CPA is different from allergic conditions such as ABPA and from invasive aspergillosis.
CPA can be difficult to recognise because its symptoms overlap with other lung conditions. Diagnosis and treatment usually need specialist input, careful interpretation of scans and tests, and follow-up over time.
Patient-centred information from the National Aspergillosis Centre. This guide combines specialist clinical knowledge with the questions, experiences and practical concerns raised by people living with CPA and their carers.
Key points
- CPA is a long-term lung infection, usually occurring in lungs already affected by disease or previous injury.
- Symptoms may include cough, fatigue, weight loss, breathlessness, chest discomfort and coughing up blood.
- Diagnosis relies on the whole picture: symptoms, scans, blood tests and sometimes sputum or tissue samples.
- Not everyone needs the same treatment. Antifungal medicines, monitoring and treatment of complications are tailored to the individual.
- Living with CPA often involves managing symptoms, treatment burden and uncertainty as well as the infection itself.
What is CPA?
CPA is an infection that persists or progresses slowly in the lungs. It most often affects people with an underlying lung condition or previous lung damage, although the immune system may otherwise be working normally.
Possible underlying conditions include bronchiectasis, chronic obstructive pulmonary disease (COPD), previous tuberculosis, sarcoidosis, emphysema, previous lung surgery and other causes of scarring or cavities in the lungs.
Read: What is aspergillosis? →
Different forms of CPA
CPA is an umbrella term. The names describe the pattern seen on scans and the way the condition behaves.
- Chronic cavitary pulmonary aspergillosis: cavities in the lungs which may change or enlarge over time.
- Chronic fibrosing pulmonary aspergillosis: more extensive scarring that can develop after long-standing cavitary disease.
- Aspergilloma: a fungal ball inside an existing lung cavity. It may cause few symptoms, but can be associated with coughing up blood.
- Aspergillus nodules: nodules which can sometimes resemble other conditions on a scan and may need further investigation.
Read more about aspergilloma and other forms of aspergillosis →
Symptoms of CPA
Symptoms often develop gradually and vary considerably. They may include:
- persistent cough, with or without sputum;
- fatigue, reduced energy or reduced stamina;
- breathlessness or chest discomfort;
- unintended weight loss or poor appetite;
- recurrent chest symptoms or infections; and
- coughing up blood.
Contact your clinical team if symptoms are new, worsening or different from your usual pattern. Seek urgent medical help for significant or repeated coughing up of blood, rapidly worsening breathlessness or severe illness.
Read more about symptoms of Aspergillus disease →
How is CPA diagnosed?
There is no single test for CPA. Clinicians bring together the history of symptoms, scan findings, evidence of Aspergillus infection or immune response, and other possible explanations for the lung changes.
Investigations may include CT scans or chest X-rays, blood tests for Aspergillus-specific antibodies, sputum testing and, in selected situations, bronchoscopy or tissue samples. The aim is to establish whether the scan changes and symptoms are due to CPA and to identify the form of disease.
Treatment and monitoring
Treatment is individual. It depends on the type and extent of CPA, symptoms, scan changes, other lung conditions, the risk of complications and the person’s general health.
Antifungal medicines are often important, but their duration and benefit vary. Treatment may also include airway clearance, management of other lung conditions, nutritional support, treatment for symptoms and procedures to manage significant bleeding. Surgery is considered only for selected situations, such as some single aspergillomas or nodules.
Regular monitoring helps the team understand whether treatment is helping and whether it is safe. This may include symptom review, blood tests, drug levels, liver tests, scans, lung function and sputum results.
Read more about treatment and management →
Living with CPA
CPA can affect daily life as much as it affects the lungs. Fatigue, breathlessness, repeated appointments, medication side effects and anxiety about scans or flare-ups can all take energy. Many people find that pacing, keeping a note of questions and symptoms, and using support from family, carers and other patients makes a real difference.
Common questions
Is CPA contagious?
No. CPA is not passed from person to person.
Does everyone with CPA need lifelong antifungal treatment?
No. Treatment is individual. Some people need long-term antifungal treatment or monitoring, while others may have different management needs. Your specialist team will review what is appropriate for you.
Can CPA be cured?
Some forms can be treated very effectively, but CPA is often managed as a long-term condition. The goals may include controlling infection, preventing progression, protecting lung function and improving quality of life.
Last reviewed: September 2026
Online Meeting Recordings

Our regular online meetings bring together people affected by aspergillosis, carers, families and members of the NAC CARES team. They are a chance to hear useful information, share experiences and feel less alone.
If you were unable to attend, or would like to revisit a subject, you can watch a growing collection of selected meeting recordings on our YouTube channel. We also bring together recent videos in short articles, making it easier to find information on a particular topic.
Watch recorded patient meetings on YouTube
Use the chapter timings
Many full meeting recordings include chapter timings in their YouTube descriptions. These let you jump directly to a subject that interests you, such as treatments, biologics, symptoms, research or practical support.
Look for the Chapters list below each video on YouTube. Select a time to start watching from that point.
Latest meeting recordings
Explore recent meeting articles and short video collections. New recordings will appear here as they are published.
- Thursday Sessions: Support beyond clinic—finding information and connection that feels right for you (9/10/2026)
- Making room for life alongside aspergillosis (8/28/2026)
- The Thursday Sessions: When Managing Treatment Becomes as Exhausting as Managing Illness (8/27/2026)
- The Thursday Sessions: Living with Aspergillosis Day to Day (8/21/2026)
- Finding Extra Support Beyond Aspergillosis: Groups for People with Lung Conditions (8/19/2026)
- The Future of Aspergillosis Care: Earlier Diagnosis, New Treatments and Personalised Support (8/19/2026)
- Electric Fans in Hot Weather: Helpful or Harmful? (8/19/2026)
What you can find
Recordings cover a range of subjects relevant to living with aspergillosis, including treatments, symptoms, associated lung conditions, self-management, research updates, and patient or carer experiences. Each YouTube video includes a description to help you decide whether it is relevant, with links to further information where available.
Join a future meeting
Live meetings are still the best way to ask questions, hear from others and take part in the conversation. You do not need to book to join.
Find out about upcoming online meetings
A note about the recordings
These recordings provide general information and shared experiences. They cannot replace advice from your own clinical team, who know your individual circumstances.
Some meetings are not recorded, and recordings may occasionally be edited or unavailable in order to protect privacy.