


Does when I eat cause fat gain if I have adrenal insufficiency?
Many people with adrenal insufficiency worry that eating at the “wrong time” — especially later in the day — will automatically cause weight gain or “steroid belly”.
This is understandable, but it’s important to separate myths from what actually happens in the body.
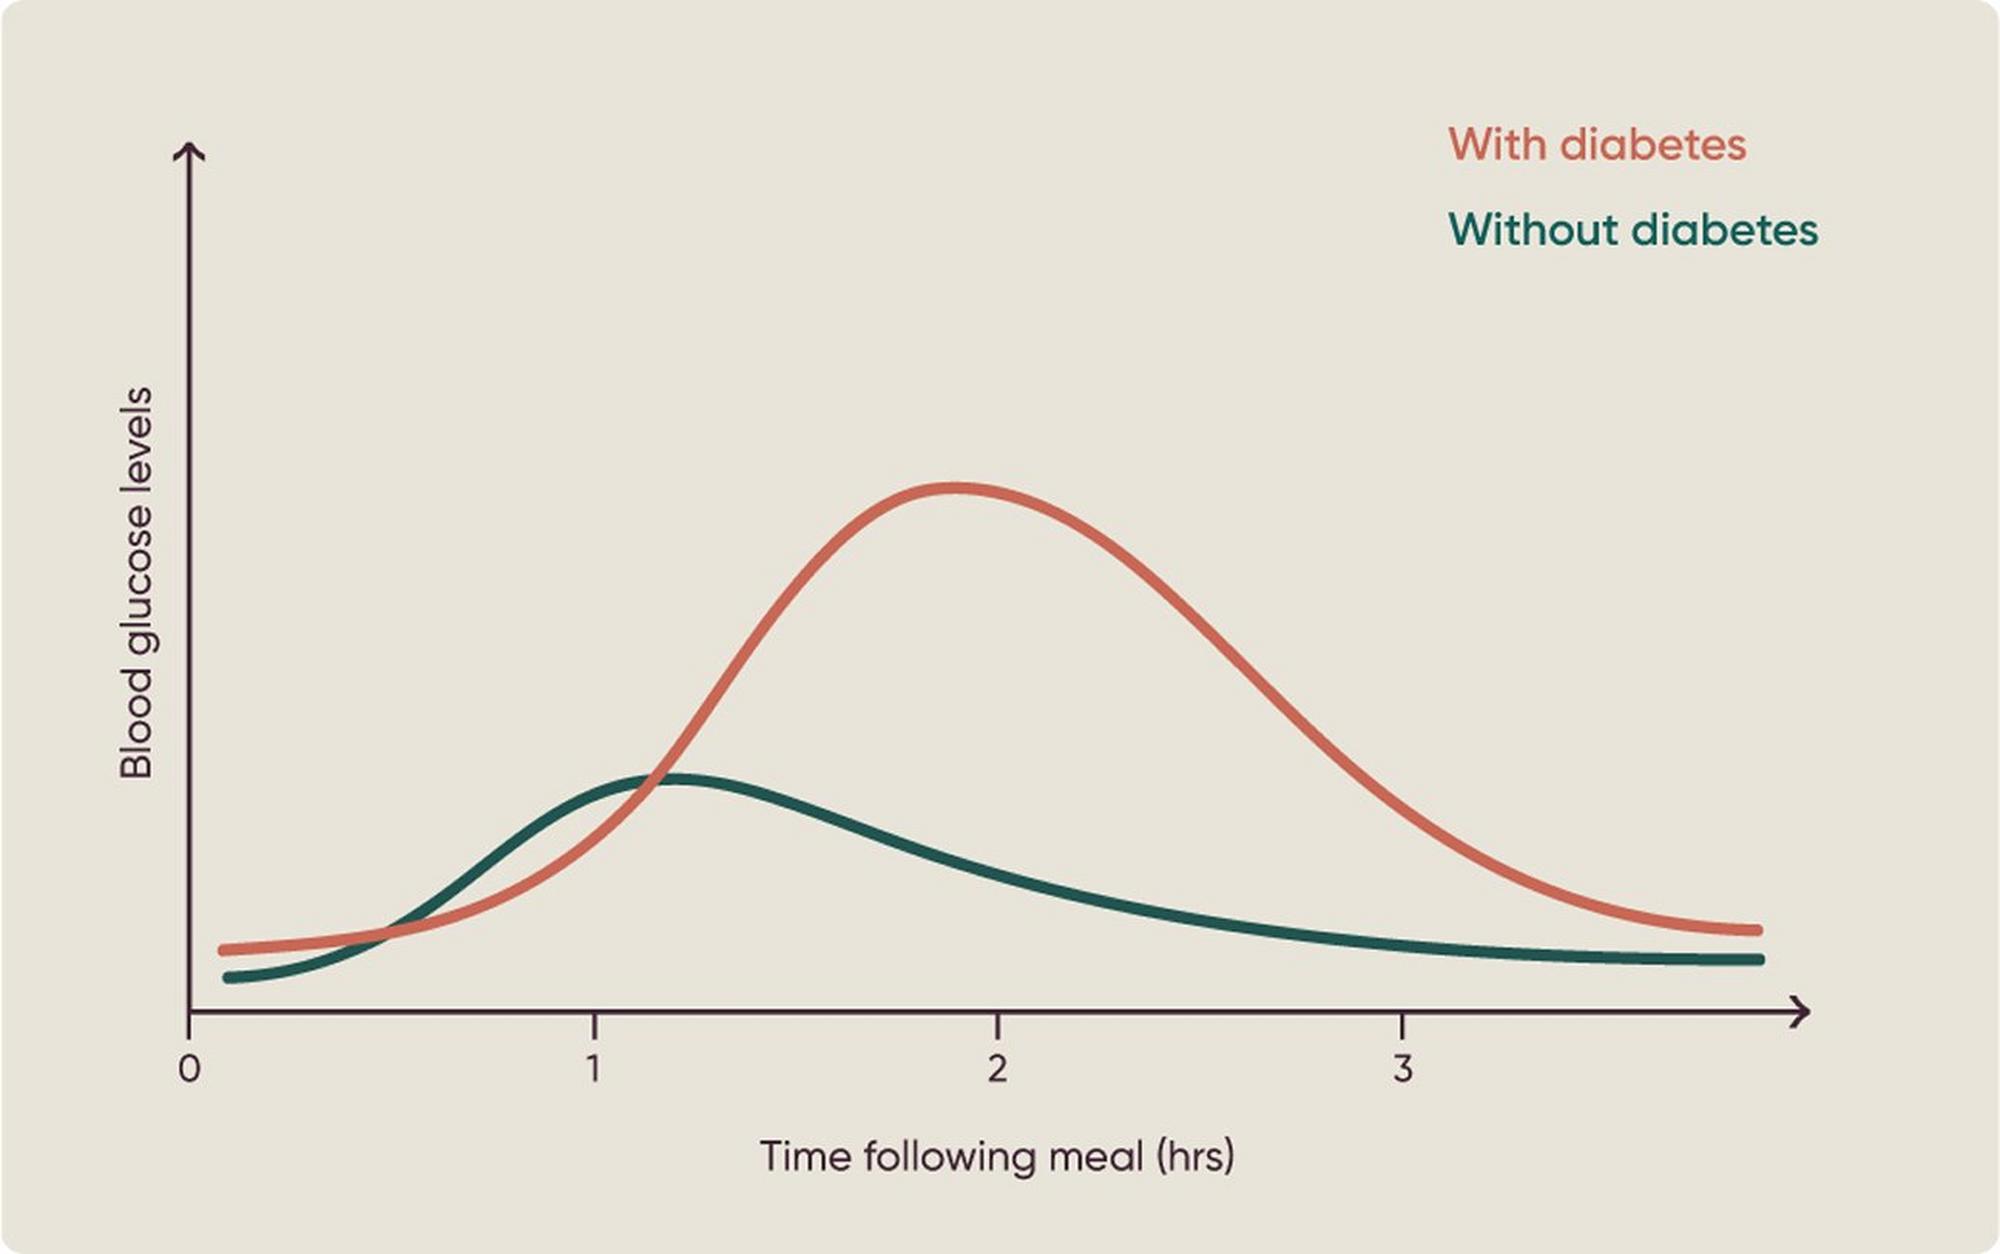

What doctors mean by “glucose response”
When clinicians or researchers talk about glucose response, they mean:
How your blood sugar rises and falls after eating
It does not mean that sugar is instantly being turned into fat.
A rise in blood glucose after eating is normal and happens in everyone.
Does eating later in the day automatically turn food into fat?
No.
Fat gain does not happen because of a single meal or snack — or because you ate at a particular time.
In most people:
-
Carbohydrates are first used for energy
-
Extra glucose is stored as glycogen in muscles and liver
-
Only repeated excess intake over time contributes to fat gain
Eating in the evening does not automatically cause fat storage.
Where insulin fits in (without the fear)
Eating raises blood glucose, which triggers insulin.
Insulin:
-
Helps move glucose into cells
-
Replenishes energy stores
-
Temporarily pauses fat burning
This pause is normal and reversible.
Insulin does not automatically create body fat.
Fat gain happens when:
-
Total calorie intake is consistently higher than needs
-
Steroid replacement is higher than required
-
This pattern continues over weeks or months
Why people with adrenal insufficiency feel confused about this
With adrenal insufficiency:
-
Cortisol replacement is taken in doses, not continuously
-
Symptoms, stress, poor sleep, or illness can affect appetite and energy
-
Some people are prone to low blood sugar, especially later in the day
Because of this:
-
Rigid food timing rules can make symptoms worse
-
Skipping meals or avoiding evening snacks can increase fatigue, dizziness, or night-time symptoms
A safer way to think about meal timing
Instead of strict rules, think in patterns:
-
Some people feel best with:
-
Larger meals earlier in the day
-
Lighter evenings
-
-
Others need:
-
A small evening snack
-
Protein or fat to keep blood sugar stable overnight
-
Both can be correct.
What matters most is:
-
How you feel
-
Whether your energy is stable
-
Whether sleep and symptoms improve
What usually matters more than timing
For people with adrenal insufficiency, weight changes are most often related to:
-
Total daily steroid dose
-
Repeated or prolonged stress dosing
-
Reduced activity due to illness or fatigue
-
Menopause, ageing, or other medical conditions
Food timing plays a much smaller role.
Key reassurance
If a food timing rule makes you feel worse, it is not the right rule for you.
-
A single glucose rise does not cause fat gain
-
Eating later does not automatically lead to weight gain
-
Safety, symptom control, and adequate steroid replacement come first
Please remember
Never change steroid dose or meal patterns intended to prevent hypoglycaemia without medical advice.
Underdosing steroids is far more dangerous than eating at the “wrong” time.
Take-home message
Focus on stability, nourishment, and feeling well — not fear of timing.


Hydrocortisone dosing in adrenal insufficiency
Why adrenal insufficiency can happen in people with aspergillosis
Many people with aspergillosis, particularly those with asthma-related conditions such as allergic bronchopulmonary aspergillosis (ABPA) or more severe chronic lung disease, need treatment with steroid medicines at some point. These treatments — often essential to control inflammation, protect the lungs, and improve breathing — may include repeated or long-term courses of steroids such as prednisolone.
When steroid treatment is used over time, it can reduce the body’s own production of cortisol by the adrenal glands. In some people, the adrenal glands do not fully recover, leading to adrenal insufficiency. Cortisol is a vital hormone that helps the body manage energy, illness, infection, and physical stress. When it cannot be made reliably, hydrocortisone replacement is needed to keep the body safe and functioning.
In this situation, hydrocortisone is prescribed to replace the cortisol your body can no longer make, usually after prednisolone has been reduced or stopped, or when prednisolone is no longer needed to control lung inflammation but adrenal support is still required.
Adrenal insufficiency in people with aspergillosis is not a failure and not something you have caused. It is a recognised consequence of necessary treatment for a serious, long-term condition. With the right information, a personalised dosing plan, and medical support, adrenal insufficiency can be managed safely alongside aspergillosis.
A patient guide to everyday (basal) dosing, higher-dose needs, and short-term stress dosing
If you take hydrocortisone because you have adrenal insufficiency, understanding how your dose works — both day to day and during illness or stress — is essential for your safety and wellbeing.
This guide explains:
-
What your basal (everyday) dose is for
-
Why some people need higher basal doses
-
When and how stress dosing is used — and why it is short term
-
Why some doctors may hesitate — and how to work safely with them
-
Where to find trusted patient and clinician resources
Very important first point ❗
Any changes to your hydrocortisone dose must be agreed in advance with a doctor or specialist nurse who knows your adrenal insufficiency.
This includes:
-
Your usual daily dose
-
Your stress-dosing (“sick day”) plan
-
Emergency injection instructions
This guide does not replace medical advice.
It is designed to help you understand your treatment and communicate clearly with healthcare professionals.
1) Your basal (everyday) hydrocortisone dose
What the basal dose is for
Your basal dose is the hydrocortisone you take on an ordinary day, when you are not ill or under unusual stress. Its purpose is to:
-
Replace the cortisol your body cannot make reliably
-
Support normal daily function (energy, blood pressure, mood)
-
Help your body feel stable and safe
-
Reduce the risk of chronic under-replacement
It is replacement, not treatment for inflammation.
A key point many patients are not told
Being consistently under-replaced does not help adrenal recovery.
Ongoing symptoms such as:
-
Constant exhaustion
-
Dizziness or nausea on standing
-
Brain fog or low mood
-
Poor tolerance of everyday stress
-
Frequent “crashes” or infections
can delay recovery, not speed it. Stability supports healing.
What doctors usually mean by a “physiological” dose
Most adults naturally produce the equivalent of about 15–25 mg of hydrocortisone per day.
Doctors aim for a dose in this range and adjust for:
-
Body size
-
Activity level
-
Other medical conditions
-
Individual response
This is replacement, not “high-dose steroids”.
How basal hydrocortisone is usually taken
To mimic the body’s natural rhythm, doses are often split:
-
A larger dose in the morning
-
Smaller doses later in the day
-
Avoiding late evening doses where possible
This supports:
-
Energy and blood pressure
-
Sleep
-
Mood and concentration
Signs your basal dose may be too low
Tell your doctor if you have persistent:
-
Severe fatigue despite rest
-
“Wired but empty” feeling
-
Dizziness, nausea, or salt craving
-
Poor concentration or memory
-
Low mood or anxiety
-
Frequent need for rescue or stress doses
These symptoms matter even if blood tests look reassuring.
Blood tests are only part of the picture
Cortisol and ACTH tests:
-
Help with diagnosis
-
Are less helpful for adjusting daily dose
-
Do not always reflect how well you function
Doctors experienced with adrenal insufficiency rely heavily on how you feel and cope day to day.
The right balance
Rather than “as low as possible,” a safer aim is:
Low enough to avoid overtreatment, but high enough to live a stable, functional life.
Living in constant deficit is not success.
2) When a higher basal dose may be appropriate
Some people with adrenal insufficiency — particularly those with chronic illness — may genuinely need a higher basal hydrocortisone dose (for example 25–30 mg/day).
This does not automatically mean overtreatment.
Well-recognised examples include:
Chronic inflammatory lung disease (including ABPA)
-
Ongoing airway inflammation and immune activation
-
Recurrent infective or inflammatory flares
-
The body may never be in a true “resting” state
-
Standard doses may leave patients under-replaced
-
A stable higher dose can reduce repeated stress dosing and improve daily function
Frequent infections or slow recovery
-
Repeated illness or prolonged recovery
-
Frequent “temporary” stress dosing just to cope with everyday life
Long-standing steroid-induced adrenal insufficiency
-
Years of prednisolone or similar treatment
-
Deep suppression of the adrenal system
Larger body size or higher metabolic demand
-
Cortisol needs vary with body size and activity
Autonomic symptoms or low blood pressure
-
Postural dizziness or faintness
-
Often benefit from a higher morning dose
Clinical clue:
If someone repeatedly needs stress dosing just to manage ordinary days, their basal dose may be too low for their current physiology.
Important reassurance
-
Higher basal doses can be appropriate, temporary, or longer-term
-
They do not automatically prevent recovery
-
Ongoing inflammation and repeated physiological stress suppress recovery more than adequate replacement
-
Doses should always be prescribed, documented, and reviewed
3) Stress dosing — when your body temporarily needs more
What stress dosing means
A healthy body automatically makes more cortisol during:
-
Illness or infection
-
Fever
-
Vomiting or diarrhoea
-
Injury or trauma
-
Severe pain
-
Surgery or medical procedures
-
Major physical stress
If you have adrenal insufficiency:
➡️ your body cannot do this, so doctors prescribe stress dosing in advance as part of your safety plan.
Stress dosing is essential — but it is short term
Stress dosing is meant to last only as long as the stress lasts.
It covers a temporary increase in need, not your everyday requirements.
What “short term” usually means
Stress dosing may last:
-
24–48 hours for minor illness or fever
-
Several days for infections or recovery from injury
-
During and immediately after surgery or procedures
Your doctor should advise:
-
When to increase
-
How much to increase
-
When and how to return to your usual dose
Why stress dosing should not continue indefinitely
If higher doses are needed for longer, something usually needs review:
-
Infection or inflammation has not settled
-
The basal dose may be too low
-
Another medical problem is present
If stress dosing is still needed after the original stress has passed, it’s time to talk to your doctor.
Stepping back down safely
-
Doctors usually advise returning to baseline
-
Sometimes a 1–2 day step-down is used
-
You should not remain on stress doses “just in case”
Stress dosing does NOT:
-
Stop adrenal recovery
-
Mean you are “failing”
-
Cause long-term harm when used correctly
Not stress dosing can:
-
Make you seriously unwell
-
Delay recovery
-
Lead to adrenal crisis


4) Why some doctors seem hesitant
Doctors outside endocrinology (GPs, A&E, ward teams):
-
Are trained to minimise steroid use
-
Often think of steroids only as anti-inflammatory drugs
-
May rarely manage adrenal insufficiency
What they may not realise immediately:
Your hydrocortisone is replacing a missing hormone — it is essential, not extra.
5) How to advocate safely (with medical backing)
It is appropriate to say:
“I have adrenal insufficiency. My doctor has advised stress dosing during illness to prevent adrenal crisis.”
If you have them, show:
-
Your Steroid Emergency Card
-
A written stress-dosing plan
-
A clinic letter or summary
6) Trusted resources & further support (with links)
The following organisations provide reliable, clinician-endorsed information on adrenal insufficiency, hydrocortisone replacement, stress dosing, and emergency care.
They are widely recognised by NHS endocrinology teams and safe to share with patients, families, and healthcare professionals.
UK patient and professional resources
Addison’s Disease Self-Help Group (ADSHG)
Website: https://www.addisonsdisease.org.uk
What it offers:
-
Clear explanations of basal vs stress dosing
-
Patient-friendly sick-day rules
-
Emergency hydrocortisone injection guidance
-
Downloadable patient leaflets used in NHS clinics
-
Webinars, helpline, and peer support
Why it’s useful:
ADSHG explicitly supports individualised dosing and crisis prevention.
Society for Endocrinology
Steroid Emergency Card & adrenal crisis guidance:
https://www.endocrinology.org/clinical-practice/steroid-emergency-card/
Why it’s useful:
-
Highly trusted by doctors, A&E, and ward teams
-
Clear professional wording that reassures non-specialists
-
Supports rapid decision-making in emergencies
NHS (England)
Steroid Emergency Card information:
https://www.nhs.uk/conditions/steroid-emergency-card/
Why it’s useful:
-
Official NHS backing
-
Useful for legitimacy in emergency or inpatient settings
International patient resources (useful supplements)
Endocrine Society
Patient information on adrenal insufficiency:
https://www.endocrine.org/patient-engagement/endocrine-library/adrenal-insufficiency
Why it’s useful:
-
Clear explanations of cortisol physiology
-
Conservative, authoritative tone
-
Helpful for patients seeking international consensus
National Adrenal Diseases Foundation (NADF)
Website: https://www.nadf.us
What it offers:
-
Practical sick-day rules
-
Emergency preparedness guidance
-
Injection training resources
Particularly helpful for patients with long-standing adrenal insufficiency or frequent illness.
Resources especially relevant for ABPA & chronic lung disease
National Aspergillosis Centre
Website: https://mft.nhs.uk/wythenshawe/services/infectious-diseases/national-aspergillosis-centre/
Why it’s relevant:
-
Specialist centre where ABPA and adrenal insufficiency often overlap
-
Supports personalised care plans in complex disease
Aspergillosis Trust
Website: https://www.aspergillosistrust.org
Why it’s useful:
-
Patient-focused education and advocacy
-
Helps explain the chronic physiological stress of ABPA
-
Supports conversations about higher basal hydrocortisone needs
Quick-access patient checklist (phone / wallet)
Patients are encouraged to keep:
-
Steroid Emergency Card
-
Sick-day rules (ADSHG)
-
Personal stress-dosing plan (agreed with doctor)
-
Clinic letter or summary
Many patients keep photos of these documents on their phone for emergencies.
Final reassurance
These resources support — not replace — medical advice.
They exist to help patients stay safe, informed, and confident when managing hydrocortisone and communicating with healthcare professionals.

Season’s Greeting
As the year draws to a close, we would like to send warm wishes to everyone in the aspergillosis community — patients, families, carers, clinicians, nurses, scientists, and all professionals working to improve care and understanding.
Living with aspergillosis, or supporting those who do, often requires resilience, patience, and compassion. Throughout this year, we have seen remarkable strength from patients, dedication from healthcare teams, and generosity of spirit across our wider community.
At this time of reflection and renewal — whether you mark Christmas, another festival, or simply the turning of the year — we hope you find moments of rest, comfort, and connection. May the days ahead bring steadier health where possible, renewed energy, and continued progress in care, research, and support.
Thank you for being part of this community.
With warmest wishes for peace, kindness, and hope — now and into the New Year.

New UK Best Practice Guidelines for Diagnosing Fungal Diseases – What Patients Need to Know
A major new set of UK guidelines has just been published on how doctors and laboratories should diagnose serious fungal diseases. These come from the British Society for Medical Mycology (BSMM) and aim to make diagnosis faster, more accurate, and more consistent across the country.
For patients and families, this is very good news.
Why does this matter?
Fungal diseases can be difficult to diagnose. Many symptoms overlap with other conditions, and traditional tests sometimes miss infections. This can lead to delays, uncertainty, or unnecessary treatments.
The new BSMM recommendations help make sure that:
-
The right tests are used at the right time
-
Results come back more quickly
-
Hospitals know which modern tests give the best answers
-
Doctors can decide sooner whether antifungal treatment is needed
-
Unnecessary or ineffective treatments can be avoided
Overall, this means quicker diagnoses, fewer missed cases, and better care.
What is new in these guidelines?
The guidance highlights several improvements that directly benefit patients:
1. More accurate tests
Doctors are encouraged to use modern tests such as PCR, antigen tests, and antibody tests—these can detect fungal infections earlier and more reliably than traditional culture alone.
2. Faster turnaround times
Hospitals are encouraged to report important results within hours, not days. Faster answers mean faster treatment.
3. Better testing for people with chronic lung conditions
People with asthma, bronchiectasis, COPD, cystic fibrosis, or other long-term lung problems are now recognised as groups who may need access to fungal testing sooner.
4. Clearer pathways for difficult-to-diagnose conditions
Conditions such as chronic pulmonary aspergillosis (CPA), allergic bronchopulmonary aspergillosis (ABPA), fungal bronchitis and invasive fungal infections now have clearer testing strategies.
5. Stronger links to antifungal stewardship
This means using antifungal medicines only when they are truly needed, helping prevent side-effects and resistance.
6. Guidance for hospitals with fewer resources
The document includes a step-by-step approach to help smaller or overseas hospitals improve gradually.
What does this mean for patients?
If you are living with, or being assessed for, a fungal condition, you should expect:
-
More consistent tests wherever you are treated in the UK
-
Better access to specialist testing when needed
-
Earlier and more confident diagnoses
-
More appropriate treatments, with less trial-and-error
-
Closer monitoring during treatment
These improvements could reduce anxiety, cut down on repeated appointments, and help your clinical team make clearer decisions.
Who should be following these guidelines?
-
Hospital laboratories
-
Doctors and nurses in respiratory, ICU, oncology, infectious diseases, and transplant services
-
GP practices referring patients for investigation
-
Healthcare commissioners
-
Hospitals outside the UK wanting to improve fungal care
Patients and carers can also play a part by asking:
“Does my hospital follow the latest BSMM recommendations for fungal testing?”
The bottom line
These new BSMM guidelines are a major step forward for anyone affected by fungal disease. They promote earlier diagnosis, better access to testing, safer treatment, and improved outcomes.
Putting these recommendations into everyday practice—across the UK and worldwide—has the potential to transform care and save lives.

Potential respiratory hazards of fungal exposure in the residential indoor environment: a systematic review (2025)
Summary of the 2025 Systematic Review for Non-Specialists & Patients
Read full paper here: Potential respiratory hazards of fungal exposure in the residential indoor environment: a systematic review - ScienceDirect
What was this review about?
This review looked at all the scientific evidence from 1990–2025 on how indoor fungi (moulds) in homes affect people’s breathing and general respiratory health. It examined 94 studies, mapping out where fungi come from, which species appear most often, and how they affect the lungs, nose, throat, and immune system.
Key Findings in Plain Language
1. The biggest sources of indoor mould are dampness and building damage
Homes with water leaks, damp walls, damaged materials and poor ventilation are the most common sources of fungi—especially Aspergillus and Penicillium. These thrive in wet building materials, bathrooms, kitchens, drains, air-conditioning systems and even water dispensers.
2. Indoor fungi are strongly linked to a wide range of respiratory symptoms
Across many countries, indoor fungal exposure was associated with:
-
Asthma and asthma flare-ups
-
Allergic rhinitis (blocked or runny nose)
-
Chronic cough and throat irritation
-
Adenoid enlargement in children
-
Hypersensitivity pneumonitis (allergic inflammation of the lungs)
-
Reduced lung function
-
Even pulmonary haemorrhage in rare cases
The review shows that even everyday exposure—not just visibly mouldy homes—can worsen respiratory health.
3. Some fungi are more strongly associated with illness
Important associations include:
-
Aspergillus → asthma symptoms, COPD exacerbations, throat irritation, hypersensitivity reactions
-
Penicillium → asthma, allergic rhinitis, hypersensitivity pneumonitis
-
Alternaria → childhood asthma risk
-
Candida & Fusarium → present in wet areas such as bathrooms and may affect vulnerable individuals
4. The geographic picture is uneven
Most research comes from high-income, temperate countries. There are major evidence gaps in tropical and subtropical regions, where humidity is high and fungal exposure is likely worse. This limits current global understanding of risk.
5. Prevention works — but public awareness is low
Simple actions (cleaning, improved ventilation, addressing leaks, correct humidity ranges) can radically reduce fungal burden. One study showed 80–90% reduction in airborne mould counts after residents were given basic remediation advice.
What’s New or Important in This 2025 Review?
1. A fully integrated “source → species → disease → location” map
The review is the first to link fungal sources, the exact fungi found, the diseases they cause, and where the evidence comes from, creating a multi-layered evidence map. This helps identify:
-
Which household features pose the highest risk
-
Which fungi are clinically most important
-
Where research gaps exist
2. Highlights the major global research imbalance
It emphasises that very little evidence exists from low-income and tropical areas—where exposure may be far more severe. This is a call for equity and better global surveillance.
3. Shows that fungi may affect more than the lungs
The review notes new evidence that fungal exposure may also influence neurological and immune-mediated symptoms, suggesting mould exposure could have broader health effects than traditionally recognised.
4. Identifies major gaps in identifying which fungal species cause harm
Many studies only measure “mould level” without identifying the fungus. The review argues for better fungal detection technologies, such as:
-
Portable real-time samplers
-
Multi-omics (DNA, RNA, metabolites)
-
Long-term cohort studies
These tools could finally clarify which fungi cause which illnesses.
5. Strong emphasis on emerging technologies for prevention
Including:
-
UV and photocatalytic TiO₂ devices
-
Improved antifungal cleaning agents
-
Building materials designed to resist mould growth
-
Volcanic minerals and clays that absorb harmful compounds
Why This Review Matters (for Patients, Carers, and Clinicians)
1. It shows mould is not “just an allergy problem”
Indoor fungi can worsen or trigger asthma, COPD, hypersensitivity pneumonitis, chronic sinus issues, and may even influence immune and neurological health. This validates patient experiences where damp homes worsen symptoms.
2. It provides strong evidence for housing-related health advocacy
Patients can use this to:
-
Request landlord repairs
-
Support home assessments
-
Advocate for rehousing if severe mould is present
-
Justify humidifier/dehumidifier use, and ventilation improvements
3. It highlights the importance of early remediation
Even simple cleaning and remediation steps can dramatically reduce mould burden and symptoms—important for families, vulnerable groups, and those with chronic lung disease.
4. It gives clinicians a clearer evidence base
Respiratory teams can use this to:
-
Recognise when housing contributes to disease flare-ups
-
Understand which conditions are most strongly linked to indoor fungi
-
Make better-informed referrals for environmental health assessments
5. It builds a scientific foundation for future guidelines
The authors point out that national building codes, indoor air quality policies, and public health guidance lag behind the evidence—and this review is intended to inform future regulation.
Who Does This Help Most?
Patients with:
-
Asthma
-
Allergic bronchopulmonary aspergillosis (ABPA)
-
Aspergillus bronchitis
-
COPD (especially those with fungal-associated exacerbations)
-
Hypersensitivity pneumonitis
-
Children with recurrent respiratory infections
-
Anyone living in damp, mouldy, water-damaged, or poorly ventilated homes
Clinicians:
Respiratory physicians, GPs, ENT specialists, allergists, immunologists.
Policy & Housing Professionals:
Public health teams, environmental health officers, social landlords, housing associations.
Researchers:
Those developing diagnostics, fungal exposure studies, indoor air quality monitoring, or patient-centred environmental interventions.

What to do if you think you’ve been given the wrong dose of a medication
Advice for people living with aspergillosis
Most of the time, prescriptions are correct and safe. However, people with aspergillosis often have complex medical needs, and it is not unusual for treatment to differ from standard “one-size-fits-all” dosing. This means that occasionally, a prescription may not match what you usually receive or what your specialist has recommended.
If something doesn’t look right, it is reasonable — and responsible — to pause and check.
Why this can happen
Prescribing in GP surgeries and hospitals is usually done using electronic systems with preset doses and durations. These defaults are designed for the average patient and for common infections.
People with aspergillosis may:
-
need longer or higher-dose treatment
-
be taking interacting medicines (for example antifungals or steroids)
-
have been advised by a specialist to follow a non-standard plan
If this information is not clearly visible at the time of prescribing, the prescriber may reasonably select a default option that is not quite right for you. This is a system issue, not a personal failure.
Signs that a prescription may need checking
You might want to query a prescription if:
-
the dose or duration is different from what you usually receive
-
it does not match what your specialist discussed
-
it seems very short for a significant infection
-
the pharmacist queries it
-
you feel significantly worse after starting it
You do not need to know what the “correct” dose should be to ask for a review.
What to do — step by step
1. Do not ignore your concern
If something feels wrong, it is appropriate to pause and ask for clarification.
2. Speak to the pharmacist
Pharmacists are trained to spot dosing and duration issues. Ask:
-
“Does this look right for someone with my condition?”
-
“Could you check this against my previous prescriptions or clinic letters?”
Pharmacists can often contact the prescriber directly.
3. Contact the prescriber for a check
You can say:
-
“I have a long-term lung condition and usually need non-standard dosing.”
-
“Could this be checked against my specialist advice?”
This is a safety check, not a complaint.
4. Use trusted information sources
In the UK, the British National Formulary (BNF) lists usual doses and important side effects. You are not expected to interpret this alone, but it can help you explain your concern clearly.
5. If you are unsure, do not start or continue without advice
If you are worried about dose, duration, or side effects, seek medical advice urgently rather than continuing in uncertainty.
Why this matters for aspergillosis patients
In people with chronic lung disease:
-
under-dosing can lead to treatment failure or relapse
-
short courses may increase the risk of resistance
-
symptoms may worsen and be misinterpreted as disease progression
From an antimicrobial stewardship (AMS) perspective, the right dose and duration are just as important as avoiding unnecessary antibiotics.
This is about partnership, not blame
Most prescribing issues happen because:
-
systems default to standard settings
-
clinicians work under extreme time pressure
-
complex information is not always easy to see
Good care depends on patients, prescribers and pharmacists working together.
If safety depends on the patient spotting an error, the system needs improving — not the patient.
Key take-home message
If a prescription doesn’t look right for you, it is reasonable to ask for it to be checked.
Asking for clarification protects you and supports safer care for everyone.

Aspergillosis Patient Conference 2025 – summary and recording

The Aspergillosis Patient Conference 2025 took place online on 29 November 2025. The event was co-organised and co-presented by the National Aspergillosis Centre (NAC) and The Aspergillosis Trust, in collaboration with the European Lung Foundation (ELF).
The free conference brought together people living with aspergillosis, carers, patient advocates, clinicians and researchers from across Europe and beyond. Its focus was firmly patient-centred, combining clinical expertise with lived experience to improve understanding, awareness and care.
🎥 The full conference recording is now available to watch online, enabling anyone who missed the live event to benefit from the sessions and discussions.
What the conference covered
Across the programme, speakers explored:
-
What aspergillosis is and the different forms it can take
-
Symptoms and diagnostic challenges, including delays in recognition
-
Current treatment and management approaches
-
Living with aspergillosis, shared directly by patients
-
What needs to improve, including awareness, education and access to specialist care
Live questions, polling and discussion ensured that patient priorities and real-world concerns shaped the conversation throughout.
Speakers and perspectives
The conference featured a broad range of patient advocates and clinical experts, including:
-
People with lived experience of chronic pulmonary aspergillosis (CPA) and allergic bronchopulmonary aspergillosis (ABPA)
-
Representatives from NAC, The Aspergillosis Trust and the ELF Aspergillosis Patient Advisory Group
-
Respiratory physicians, infectious disease specialists and researchers involved in European clinical guidelines and research
This mix ensured that sessions reflected both medical best practice and day-to-day patient realities.
Who the recording is useful for
The on-demand recording is particularly valuable for:
-
People living with aspergillosis and related lung conditions
-
Family members, carers and supporters
-
Healthcare professionals seeking a patient-focused overview
-
Patient organisations and advocates working in respiratory or fungal disease
Why this conference matters
Aspergillosis remains under-diagnosed and poorly understood, despite its significant impact on health and quality of life. This conference highlighted:
-
The importance of patient voices in education and guideline development
-
The need for earlier diagnosis and clearer care pathways
-
The value of collaboration between specialist centres, patient charities and European organisations
By making the recording freely available, NAC, The Aspergillosis Trust and ELF have ensured the conference continues to support patients, carers and professionals well beyond the live event.
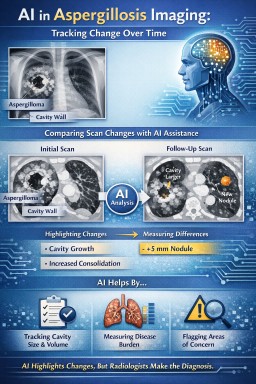
The role of AI in imaging follow-up for aspergillosis
Aspergillosis is not a single disease, but a spectrum of related conditions, including allergic bronchopulmonary aspergillosis (ABPA), chronic pulmonary aspergillosis (CPA), aspergilloma, subacute invasive aspergillosis, and Aspergillus bronchitis. Across this spectrum, imaging plays a central role in assessment, monitoring, and treatment planning.
Artificial intelligence (AI) is increasingly being explored in chest imaging as a supportive tool, particularly in the follow-up of chronic and complex lung disease. Its potential value in aspergillosis lies not in making diagnoses, but in consistent, data-driven image comparison.
Why aspergillosis is challenging for imaging interpretation
Imaging findings in aspergillosis are often:
-
Non-specific, overlapping with tuberculosis, non-tuberculous mycobacterial lung disease, lung cancer, vasculitis, and post-infectious scarring
-
Heterogeneous, even within the same patient
-
Slowly evolving, making change difficult to judge by eye
-
Mixed with other lung disease, such as bronchiectasis, asthma, fibrosis, or emphysema
For these reasons, imaging must always be interpreted in full clinical context and often benefits from specialist multidisciplinary discussion.
Where AI may add particular value
AI does not “know” that it is looking at aspergillosis. Instead, it compares imaging data directly, without assumptions about diagnosis. This can be helpful in several areas relevant to aspergillosis:
1. Consistent comparison of serial scans
AI can compare computed tomography (CT) scans over time using the same criteria each time, helping to:
-
Detect subtle interval change in cavities or nodules
-
Measure changes in cavity size, wall thickness, or internal content
-
Identify progression or stability that may be difficult to judge visually
This is particularly useful in chronic pulmonary aspergillosis, where progression may be slow and subtle.
2. Objective measurement of disease burden
AI can assist with:
-
Quantifying cavity volume or consolidation
-
Measuring extent of bronchiectasis or mucus plugging
-
Tracking changes following antifungal treatment or airway clearance
Objective measurements may help reduce subjectivity when monitoring response to treatment.
3. Highlighting areas for closer review
AI systems can flag areas of change or abnormality for radiologist attention. This may act as a “second set of eyes”, particularly in busy services, but does not replace expert review.
What AI cannot do in aspergillosis
It is important to be clear about the limitations:
-
AI cannot diagnose aspergillosis
-
AI cannot distinguish colonisation from active disease
-
AI cannot integrate symptoms, immune status, serology, or microbiology
-
AI cannot judge clinical significance or treatment need
For example, a change in cavity appearance may reflect active disease, treatment response, bacterial infection, bleeding, or simple movement of intracavitary material. Only expert clinical interpretation can determine significance.
Why radiologist expertise remains essential
In aspergillosis, small imaging changes can have very different meanings depending on context. Radiologists bring:
-
Experience in recognising mimics and artefacts
-
Understanding of treatment-related change
-
Ability to communicate uncertainty and recommend next steps
-
Integration of imaging with wider clinical information
AI may improve consistency and sensitivity, but responsibility for interpretation and reporting remains with the radiologist.
A balanced way to think about AI in aspergillosis imaging
In aspergillosis, artificial intelligence is best viewed as a tool that highlights and measures change, rather than one that explains or diagnoses it. Its strength lies in consistency; its limitation lies in lack of clinical understanding.
Used appropriately, AI may support safer and more consistent follow-up for people living with aspergillosis, while expert radiology and specialist clinical care remain central to diagnosis and management.

When treatment itself causes harm: an important message for people with aspergillosis
For most people, following medical advice is the safest and most appropriate course of action. However, for some people living with aspergillosis or other long-term lung conditions, treatment itself can occasionally cause harm — particularly when adverse drug reactions are not recognised early.
Aspergillosis often requires long-term or repeated courses of medication, sometimes alongside treatment for co-existing infections or other conditions. Because symptoms of aspergillosis can overlap with medication side effects, new or worsening problems may be assumed to be part of the illness rather than a reaction to treatment.
Why this can be difficult to recognise
People with aspergillosis may:
-
already experience fatigue, breathlessness, pain, or neurological symptoms
-
take multiple medicines at the same time
-
have fluctuating symptoms due to infection, inflammation, or treatment response
This makes it harder to distinguish disease activity from drug-related effects.
The importance of recognising adverse drug reactions
Some medicines commonly used in people with lung disease can, in a small number of individuals, cause serious or long-lasting side effects. These reactions may develop gradually or worsen with continued use.
Examples (not exhaustive) include:
-
Antibiotics – tendon, nerve, gastrointestinal, cardiac or immune-related effects
-
Antifungal medicines – liver toxicity, neurological symptoms, skin reactions, drug interactions
-
Steroids – bone loss, adrenal suppression, mood changes, infection risk
-
Immunosuppressive or biologic therapies – infection risk, immune dysregulation, inflammatory reactions
Not everyone experiences these effects, and many people take these medicines safely. However, when significant new symptoms appear after starting or changing treatment, they should be actively reassessed.
Why knowledge of medication side effects matters
Patients are not expected to diagnose themselves. However, having a basic awareness of known serious side effects can help patients recognise when something may not be right.
In the UK, trusted sources such as the British National Formulary (BNF) list both common and rare but serious adverse effects for prescribed medicines, and drug:drug interactions which are particularly significant for antifungal medications. Reviewing this information can support informed discussions with healthcare professionals, particularly if symptoms worsen rather than improve.
Checking authoritative sources is not about challenging clinical expertise or stopping treatment independently. It is about ensuring that potential drug reactions are considered alongside disease progression.
A balanced message for patients and clinicians
Safe care depends on partnership. This means:
-
patients feeling able to report side effects clearly and repeatedly if needed
-
clinicians remaining alert to drug reactions, especially when symptoms are atypical or progressive
-
being willing to pause, review, and reconsider treatment when outcomes are not as expected
Early recognition of adverse drug reactions can reduce the risk of long-term or permanent harm.
Take-home message
If treatment is making you feel significantly worse, and the symptoms do not feel right for you, it is reasonable to ask for reassessment — even if the treatment is commonly used or usually well tolerated.
Being informed, listened to, and reviewed promptly helps ensure safer care for people living with aspergillosis.

Using Radiopaedia and Online Imaging Resources Safely: What Expert Patients and Non-Specialist Clinicians Need to Know
Online radiology education platforms such as Radiopaedia (see aspergillosis images here) have transformed access to medical knowledge. They provide high-quality explanations of imaging findings, annotated examples, and differential diagnoses that are invaluable for learning, teaching, and patient empowerment.
For expert patients living with long-term conditions, and for non-specialist clinicians working outside radiology, these resources can greatly improve understanding of scan reports and discussions with healthcare teams. However, it is important to understand what these tools can – and cannot – do.
Radiopaedia is an educational resource, not a diagnostic service
Radiopaedia is designed to teach pattern recognition and radiological reasoning, not to provide individual diagnoses. The cases shown are curated examples, often with classic features, and are presented without the full clinical complexity that accompanies real patients.
Real-world imaging interpretation requires integration of:
-
Clinical history and symptoms
-
Laboratory results (for example inflammatory markers, microbiology, immunology)
-
Prior imaging and disease progression
-
Treatment history and response
-
Knowledge of common mimics and incidental findings
This clinical synthesis cannot be replicated by reviewing example images alone.
Why expert radiologist review still matters
For many diagnoses, there is no substitute for a radiologist formally reviewing and interpreting the imaging.
This is particularly true when:
-
Findings are subtle or evolving
-
Multiple conditions coexist (for example bronchiectasis, infection, scarring, and inflammation together)
-
Imaging appearances overlap between diseases
-
Treatment decisions depend on small but important changes over time
Radiologists are trained to recognise not only “textbook” appearances, but also atypical, incomplete, or misleading patterns, and to weigh uncertainty appropriately in their reports.
Imaging patterns are rarely diagnostic in isolation
Many imaging features are non-specific. For example:
-
Cavities can be caused by infection, inflammation, malignancy, or prior disease
-
Nodules may represent infection, scarring, inflammation, or benign change
-
Mucus plugging can occur in asthma, infection, allergic disease, or chronic airway disease
Educational resources often present differential diagnoses clearly, but deciding which diagnosis applies to a specific patient requires clinical judgment and experience.
A particular note for chronic lung and fungal disease
In complex conditions such as chronic lung disease, allergic lung disease, or fungal infections, imaging interpretation is especially nuanced. Appearances may change slowly, fluctuate with treatment, or overlap with other long-standing abnormalities.
Small changes that are significant to a specialist team may appear minor or ambiguous when viewed without context. Conversely, dramatic-looking findings may represent stable or inactive disease.
This is why specialist radiology input, often alongside multidisciplinary discussion, remains essential.
How expert patients and clinicians should use Radiopaedia
Used appropriately, Radiopaedia can:
-
Improve understanding of scan terminology
-
Help frame informed questions for clinicians
-
Support education and shared decision-making
-
Aid non-specialists in recognising when further advice is needed
It should not be used to:
-
Self-diagnose based on image similarity
-
Override formal radiology reports
-
Draw conclusions without clinical correlation
The key message
Radiopaedia and similar platforms are powerful educational tools. They enhance knowledge, confidence, and communication. But for many diagnoses, they complement rather than replace expert radiologist assessment.
The safest and most effective approach is to use educational resources alongside formal imaging reports, specialist input, and clinical discussion — not instead of them.