Originally published: 29 May 2020 | Last reviewed: 18 September 2026 | Next review: September 2028
Yes—although ABPA is most often diagnosed in people with asthma, it can occasionally be diagnosed in someone who has not previously been told that they have asthma.
Allergic bronchopulmonary aspergillosis (ABPA) is an allergic-type immune reaction to Aspergillus, usually Aspergillus fumigatus, in the airways. It is most commonly associated with asthma and cystic fibrosis, but clinicians may also consider it in people with bronchiectasis, COPD, or a pattern of symptoms and test results strongly suggestive of ABPA.
Why is ABPA usually linked with asthma?
ABPA develops when the immune system reacts strongly to Aspergillus in the airways. Asthma creates an airway environment in which this reaction is more likely to occur, which is why most people with ABPA have asthma or asthma-like symptoms such as wheeze, chest tightness and variable breathlessness.
However, asthma is not always recognised before ABPA is investigated. Some people have had mild or intermittent symptoms, have been given a different diagnosis, or have airway disease dominated by bronchiectasis rather than obvious asthma.
Can ABPA be diagnosed without asthma?
Yes, but it is uncommon. Current international guidance allows clinicians to diagnose ABPA in someone without a recognised pre-existing condition when their overall clinical picture is compatible with the disease.
This is important because a diagnosis should not be ruled out solely because a person does not have an asthma label. At the same time, ABPA is a specialist diagnosis: an elevated allergy test or a positive sputum culture alone does not prove that someone has it.
When might clinicians consider ABPA?
Your clinical team may investigate for ABPA when there is a combination of symptoms, imaging changes and allergy-test results that point towards it. Features can include:
- recurrent episodes of cough, wheeze, breathlessness or chest tightness;
- thick mucus, sometimes with brownish plugs;
- coughing up blood;
- repeated chest infections or areas of inflammation seen on a chest X-ray or CT scan;
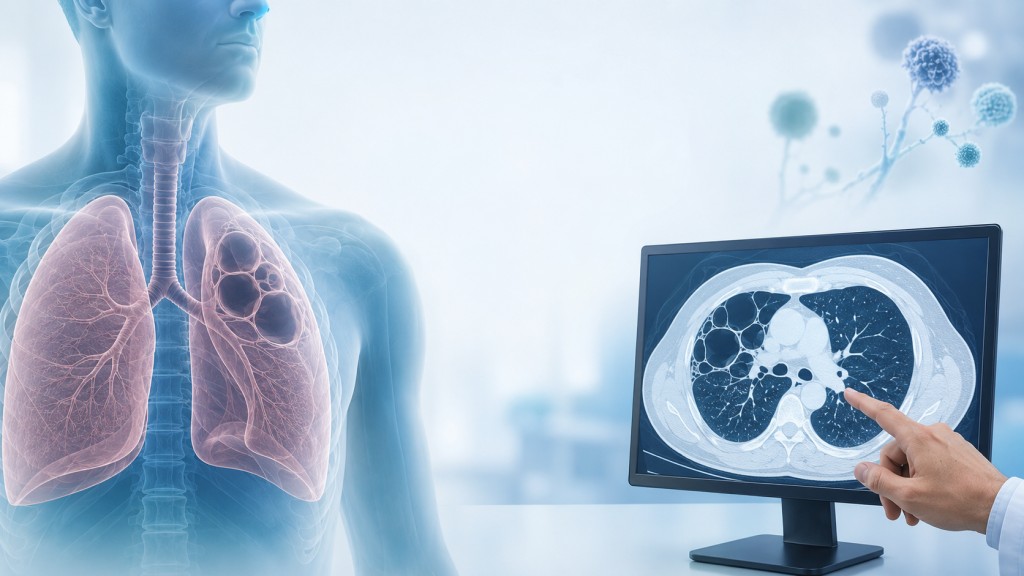
- bronchiectasis, particularly when the larger central airways are affected;
- evidence of sensitisation or allergy to Aspergillus; and
- raised total IgE and, in many cases, raised eosinophils.
Several other conditions can cause similar symptoms or test results. Your doctors will interpret the findings together, including your medical history, scans, lung-function tests and blood results.
How is ABPA diagnosed?
There is no single test that confirms ABPA. Diagnosis is based on a combination of findings. Blood tests can look for allergy to Aspergillus, total IgE and eosinophils. A CT scan can show changes such as bronchiectasis or mucus plugging. Sputum samples and lung-function tests may also help build the overall picture.
The 2024 international ISHAM guidelines lowered the total-IgE threshold used within the diagnostic criteria and recognised that a compatible clinical presentation can support diagnosis even where a usual predisposing condition is absent. These criteria are intended to guide specialist assessment; they are not a checklist for self-diagnosis.
What did earlier research find?
A 2019 retrospective study from a specialist centre reviewed 530 people with ABPA. Around 7% had no asthma diagnosis. In that group, bronchiectasis was more common, while lung function was generally better and ABPA flare-ups were less frequent than in participants who also had asthma.
This was an important study because it showed that ABPA without recognised asthma does occur. However, it was conducted at one specialist centre and cannot tell us exactly how common this presentation is in the wider population.
What should you do if you are concerned?
If you have bronchiectasis, recurrent respiratory symptoms or abnormal Aspergillus blood tests and are wondering whether ABPA could be relevant, discuss this with your GP, respiratory clinician or specialist team. Do not change inhalers, steroids or antifungal treatment without clinical advice.
For a broader introduction, visit our ABPA hub.
Further reading

Did this page help you?
Tell us in one minute