


Help Us Explore a New Treatment for Chronic Pulmonary Aspergillosis (CPA)
We’re Recruiting for a Clinical Trial of Interferon-Gamma (IFNγ)
We’re looking for people with chronic pulmonary aspergillosis (CPA) to take part in an exciting clinical trial testing a new treatment approach using interferon-gamma (IFNγ) — a substance that could help the immune system fight the Aspergillus infection more effectively.
What is CPA?
CPA is a long-term lung infection caused by the fungus Aspergillus. It usually affects people with chronic lung diseases like COPD or those who’ve had tuberculosis (TB) in the past. Over time, CPA can cause:
-
Enlarging cavities in the lungs
-
Recurrent chest infections
-
Persistent coughing and fatigue
-
Worsening breathlessness and reduced quality of life
It’s a progressive condition and can be hard to diagnose early. Around 3,600 people are living with CPA in the UK. Without effective treatment, CPA can be life-limiting — up to 4 in 10 people may die within five years of diagnosis.
Current Treatment Challenges
Treatment typically involves long-term antifungal medication, but:
-
Only about 60% of patients improve
-
Treatment can be lifelong, with relapses common
-
There is only one class of oral antifungals available
-
Side effects and high costs are frequent problems
This is why we urgently need better treatment options.
Why Interferon-Gamma?
Our research suggests that many CPA patients may have a weakened immune response, particularly a lower production of interferon-gamma (IFNγ) — a natural substance that helps the body fight fungal infections like Aspergillus.
In small studies, giving IFNγ to patients who didn’t respond to antifungals showed fewer lung flares, fewer hospital stays, and better quality of life. It’s already used safely in other NHS treatments — now we want to explore its role in CPA.
What This Trial Involves
We’re running a randomised clinical trial to test IFNγ in CPA. Here’s what to expect:
-
You must be starting antifungal treatment for CPA
-
You’ll be randomly placed in one of two groups:
-
One group receives IFNγ + antifungals for 12 weeks
-
The other group receives antifungals only
-
-
We’ll monitor:
-
Changes in lung CT scans
-
Quality-of-life scores
-
Any side effects or problems with tolerability
-
The trial will include 50 participants in total (25 in each group) and is expected to run until August 2026.
Why Your Participation Matters
By joining this study, you’ll help us find out whether IFNγ could:
-
Improve treatment outcomes
-
Shorten the duration of therapy
-
Prevent relapses
-
Potentially benefit others with chronic lung diseases
If successful, this could lead to a larger trial and possibly a new standard treatment for CPA.
Interested in Taking Part?
You may be eligible if you:
-
Have been diagnosed with CPA
-
Are about to start antifungal treatment
-
Are willing to attend follow-up appointments for 12 weeks
👉 Click here for full details and how to take part
Steroid-induced insomnia
Steroid-induced insomnia is a common and frustrating side effect of corticosteroid medications like prednisolone, dexamethasone, or hydrocortisone — especially when taken for conditions like aspergillosis, adrenal insufficiency, or inflammatory diseases.
🧠 Why it Happens
Corticosteroids affect the brain’s sleep-wake cycle and increase levels of cortisol-like hormones, which can make you feel:
-
Wired or overstimulated
-
Restless or anxious
-
Unable to fall asleep or stay asleep
Even low-to-moderate doses can affect sensitive sleepers, especially when taken in the afternoon or evening.
🕒 Tips to Manage It
1. Take Steroids in the Morning (if possible - discuss with your doctor)
Mimics the body’s natural cortisol rhythm and reduces sleep disruption.
2. Create a Wind-Down Routine
Try calming activities in the evening — reading, gentle music, warm bath, breathing exercises.
3. Avoid Stimulants After 2 PM
That includes caffeine, nicotine, and even long naps.
4. Sleep Hygiene Helps
Keep your room cool and dark
Avoid screens at least an hour before bed
Stick to a regular sleep schedule
5. Melatonin (with caution)
Some doctors may suggest melatonin to reset sleep patterns — but always ask first, especially if you're on multiple meds.
💊 Medical Support
If insomnia is severe or long-lasting:
-
Your doctor might adjust your steroid dose or timing
-
A short course of sleep aids may be prescribed if needed
-
Sometimes adding a mood stabilizer or sedating medication at night (like mirtazapine or a low-dose antihistamine) is helpful
Managing the stress of having a chronic disease, could it even be PTSD?
Let’s create a Personal Resilience Plan tailored to someone living with a chronic lung condition (like ABPA or CPA), with anxiety around lung bleeds and possible PTSD-like stress. This plan is meant to help you feel more grounded, supported, and in control, even when things feel overwhelming.
🛡️ Your Personal Resilience Plan
For Managing Chronic Illness, Lung Bleed Anxiety, and PTSD-Related Stress
🧭 1. Grounding Statement (Your “North Star”)
“I live with a serious condition, but I am not alone. I have tools, people, and plans that help me stay steady, even in scary moments.”
Use this when panic or flashbacks arise.
🧰 2. Emergency Action Plan
Having a clear plan for “what to do if…” takes the edge off the unknown.
✅ In case of a suspected lung bleed:
-
Stay calm, sit upright, lean slightly forward.
-
Call 999 (or your emergency contact) if bleeding is profuse or you feel faint.
-
Notify hospital/clinic (add number here:
__________) -
Use oxygen if prescribed. Avoid lying flat.
-
Bring your go bag with essentials (see below).
✅ Go Bag Checklist:
-
Hospital letters
-
Medication list
-
Emergency contact numbers
-
Water, charger, snacks, headphones
-
Comfort item (photo, small item that grounds you)
💬 3. People to Call/Text When You’re Struggling
| Name | Contact | Role |
|---|---|---|
| GP / Specialist Nurse | [Name] – [Number] | Medical support |
| Friend or Family Member | [Name] – [Number] | Emotional support |
| Therapist / Mental Health Contact | [Name] – [Number] | Grounding and talking it through |
| Crisis Line | 116 123 (Samaritans, 24/7 UK) | Non-judgmental emotional support |
🧠 4. PTSD & Anxiety Coping Tools
Choose 2–3 from each category that resonate with you:
🌬️ In-the-Moment Grounding Techniques:
-
Box breathing: In for 4, hold 4, out 4, hold 4
-
5-4-3-2-1 grounding: Name 5 things you see, 4 you feel, 3 you hear, 2 you smell, 1 you taste
-
Hold a cold item (ice cube or chilled bottle) — physical sensation brings you back to the present
✍️ Ongoing Processing Tools:
-
Keep a “bad day journal” just to vent — no need for polish
-
Write letters to your past self (“You got through that.”) or future self (“Here’s what helps next time.”)
📱 Helpful Apps:
-
Insight Timer (free guided breathing + trauma-sensitive meditations)
-
MindShift CBT (helps reframe anxious thoughts)
-
PTSD Coach (developed by clinicians, good for triggers + tracking)
🧘 5. Daily Resilience Routine (Small Wins Only)
Design this with chronic illness in mind — flexible and compassionate:
-
🌞 Wake up + check-in (1–10: how’s body/mind today?)
-
💊 Meds + hydration
-
👣 Gentle movement (walk to garden, stretch, or none if flaring)
-
📓 1 thing I’m grateful for, 1 thing I’m proud of
-
🌙 Wind-down: calm music, bath, story podcast
💡 6. Medical Empowerment
-
Keep a written copy of your diagnosis, meds, and hospital plan
-
Ask your doctor for a specific protocol for what to do if bleeding recurs
-
Track symptoms via app or paper log — this helps you feel seen and them spot patterns
🧑🤝🧑 7. Support Network
Consider joining:
-
Aspergillosis Trust Facebook Group: very active and supportive
-
Try finding PTSD supportive groups that suit your situation (many on Facebook and Reddit)
For more general guidance, try NHS PTSD webpages
HEPA filters & heat to reduce exposure to allergens
Patients with forms of aspergillosis like ABPA can be highly allergic to fungal and many other airborne allergens. For some, relief can be found by ensuring the levels of airborne allergens in the home are as low as possible—this means removing as much dust as possible and removing sources of dust in the home.
Fungal spore fragments can be extremely small so air filters and vacuum cleaners have to have HEPA-grade filtration systems in order to be effective. NB there are some air cleaning systems that do not use filtration as a means to remove particles, instead they use heat (see bottom of page).
For those that use HEPA filters it is important that the correct grade of HEPA filtration is provided:
HEPA (High-Efficiency Particulate Air) filters are classified into different grades based on their filtration efficiency. The most commonly used classification is from ISO 29463 (based on EN 1822-1), which divides HEPA filters into E (Efficiency), H (High Efficiency), and U (Ultra-Low Penetration Air - ULPA) categories.
HEPA Filter Grades and Their Uses
| Filter Class | Efficiency (MPPS - Most Penetrating Particle Size, ~0.1-0.3 μm) | Common Applications |
|---|---|---|
| E10 | ≥ 85% | Pre-filters in air purification systems |
| E11 | ≥ 95% | Air conditioning systems, HVAC filters |
| E12 | ≥ 99.5% | General air filtration, residential HEPA vacuum cleaners |
| H13 | ≥ 99.95% | Medical facilities, clean rooms, operating theaters |
| H14 | ≥ 99.995% | Pharmaceutical industry, laboratories, high-end medical applications |
| U15 | ≥ 99.9995% | Semiconductor manufacturing, critical research labs |
| U16 | ≥ 99.99995% | Nuclear and hazardous material containment |
| U17 | ≥ 99.999995% | Highly sensitive biological or radioactive environments |
Key Uses of Different HEPA Grades
- E10-E12: Used in standard HVAC systems, air purifiers, and vacuum cleaners.
- H13-H14: Common in hospitals, clean rooms, and biosafety labs where high air purity is needed.
- U15-U17 (ULPA): Found in pharmaceutical manufacturing, semiconductor industries, and nuclear facilities.
For medical conditions like ABPA, HEPA H13 or H14 filters are recommended in home air purifiers and hospital settings to reduce airborne Aspergillus spores.
Heat-based filtration
Some domestic air purifiers use heat-based filtration to neutralize airborne contaminants. These typically work by heating air to a high temperature to kill bacteria, viruses, mould spores, and other pathogens before cooling them down and releasing them into the room.
Types of Heat-Based Air Cleaners
-
Thermodynamic Sterilization (TSS) Air Purifiers
- Uses a ceramic core heated to ~200°C (392°F) to destroy airborne microorganisms.
- No filters, so there’s no need for replacements.
- Example: Airfree air purifiers (popular in allergy-sensitive households).
-
Hybrid Heat & Filtration Systems
- Combines heat sterilization with HEPA filters or activated carbon.
- Example: Some high-end medical-grade air purifiers integrate thermal disinfection.
Advantages
✔ Kills mold, bacteria, and viruses rather than just trapping them.
✔ No filter replacements (TSS models).
✔ Silent operation (as some don’t use fans).
Disadvantages
❌ Limited particle filtration—doesn’t remove dust, pet dander, or allergens like a HEPA filter does.
❌ Slower purification compared to fan-driven systems.
Best Use Cases
- Allergy and asthma sufferers (e.g., ABPA) who want a maintenance-free solution.
- People sensitive to mold and bacteria in humid environments.
- Homes with immunocompromised individuals needing sterile air.
How the UK evaluates new drugs for use in the NHS
The UK evaluates expensive drugs for cost-effectiveness primarily through the National Institute for Health and Care Excellence (NICE) and other bodies like the Scottish Medicines Consortium (SMC). The evaluation is based on clinical effectiveness, cost-effectiveness, and impact on NHS resources.
Key Aspects of Evaluation
1. Cost-Effectiveness Analysis (CEA) using QALYs
- NICE uses the Quality-Adjusted Life Year (QALY) as a measure to assess whether a drug provides sufficient health benefits relative to its cost.

- If the ICER is below £20,000–£30,000 per QALY, the drug is typically considered cost-effective.
- For certain severe or rare diseases, NICE may allow a higher cost per QALY threshold (e.g., up to £100,000 for very rare conditions under the Highly Specialised Technologies (HST) program).
2. Budget Impact Test
- If a drug is expected to cost the NHS more than £20 million per year, NICE may negotiate with the manufacturer for a Managed Access Agreement (MAA) or phased introduction to spread costs.
3. Clinical Evidence & Real-World Data
- NICE considers clinical trial data, real-world effectiveness, and patient-reported outcomes.
- The NHS Commercial Medicines Directorate may negotiate confidential pricing agreements (e.g., rebates or discounts).
4. NHS England & Special Cases
- For cancer drugs, the Cancer Drugs Fund (CDF) allows faster access while gathering more real-world data.
- The Innovative Medicines Fund (IMF) supports non-cancer drugs with promising early data but uncertain long-term benefits.
5. Scotland & Wales
- The Scottish Medicines Consortium (SMC) and the All Wales Medicines Strategy Group (AWMSG) perform similar cost-effectiveness evaluations for their health systems.
Example: Cost-Effectiveness Evaluation of Omalizumab in the UK
Omalizumab (Xolair) is a monoclonal antibody used for severe allergic asthma and chronic spontaneous urticaria (CSU). Its cost-effectiveness for NHS use was evaluated by NICE based on clinical benefit, quality of life improvement, and economic impact.
1. How is the benefit of Omalizumab calculated?
A. Clinical Benefits (Health Gains)
- Clinical trials show reduced asthma exacerbations, hospitalizations, and improved symptom control.
- Fewer oral corticosteroid (OCS) bursts, reducing side effects (osteoporosis, diabetes risk).
- Improved quality of life due to fewer symptoms and better lung function.
B. Quality-Adjusted Life Years (QALY) Calculation
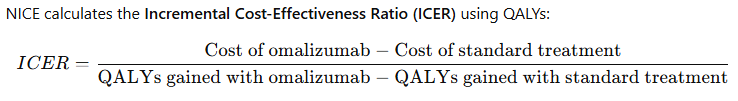
- Without treatment: Patients may experience frequent asthma attacks, reliance on oral corticosteroids, and reduced quality of life (e.g., QALY score = 0.50).
- With Omalizumab: Patients have fewer exacerbations, reduced hospital stays, and improved daily function (e.g., QALY score = 0.72).
- QALYs gained = 0.72 - 0.50 = 0.22**
**NOTE that for Omalizumab initial ICER calculation would have been £8000/26000 (ie. cost of drug) divided by 0.22 (QALY gained) which equals £40-100 000 ie. well above the usual approval threshold of £20-30 000. NHS presumably negotiated a way around that problem to allow approval of Omalizumab.
2. Cost-Effectiveness of Omalizumab
A. NHS Cost Evaluation
- Omalizumab cost: ~£8,000–£26,000 per patient per year (depending on dosage).
- Cost savings: Fewer hospitalizations, ICU admissions, and OCS-related complications.
- NICE’s ICER threshold is £20,000–£30,000 per QALY.
B. NICE Decision on Cost-Effectiveness
- For severe allergic asthma: Approved, as the ICER was ~£28,000 per QALY, within the acceptable NHS threshold.
- For chronic urticaria: Initially not approved due to an ICER > £50,000 per QALY, but later funded under special circumstances.
3. Special NHS Funding Mechanisms
- Managed Access Agreements (MAA): Discounted pricing for eligible patients.
- Real-World Data Collection: Continued monitoring of benefits via the Severe Asthma Registry.
ABPA & CPA: Patient priorities
We have launched a new section that lists the commonest symptoms reported by our patient groups and offers tips on how to manage them.

In Their Words: CPA & ABPA
How the NHS funds medications
In the UK, drug funding depends on where and how the treatment is prescribed—through the NHS, private healthcare, or research programs. Here's how different types of drugs, including biologics for severe asthma, are funded:
1. NHS Funding (Primary & Secondary Care)
a) NICE & SMC Approval (England & Scotland)
-
The National Institute for Health and Care Excellence (NICE) assesses whether a drug is cost-effective for NHS use in England and Wales.
-
In Scotland, the Scottish Medicines Consortium (SMC) performs a similar role.
-
If approved, the drug is added to NHS formularies, meaning it can be prescribed and funded.
b) Individual Funding Requests (IFRs)
-
If a drug is not routinely funded, a clinician can apply for Individual Funding Requests (IFRs) to request NHS coverage in special cases. These funding requests are made to your local NHS Integrated Care Board (ICB) (England - other UK countries have their own systems) who are responsible for managing drug costs
c) High-Cost Drugs & Specialist Prescribing
-
Some biologics (e.g., Benralizumab, Mepolizumab, Tezepelumab) are classified as high-cost drugs and can only be prescribed in specialist NHS clinics, such as severe asthma centres.
-
NHS England funds these under commissioned services, separate from standard GP prescribing.
2. Prescription Charges in England
-
In England, most adults pay £9.65 per prescription item (2024 rate).
-
However, many patients qualify for free prescriptions (e.g., those with long-term conditions, low income, or exemptions).
-
Prepayment Certificates (PPCs) allow unlimited prescriptions for a fixed cost.
 Scotland, Wales, and Northern Ireland offer free prescriptions to all residents.
3. Private Prescriptions & Insurance
-
Private healthcare patients must pay the full cost of their medication unless covered by private insurance.
-
Some private insurers (like Bupa, AXA, or Vitality) partially or fully cover biologics if deemed medically necessary.
4. Clinical Trials & Early Access
-
Some new biologics not yet NHS-approved can be accessed through clinical trials.
-
The Early Access to Medicines Scheme (EAMS) allows patients with severe conditions to access promising new treatments before full approval.
5. Hospital Funding (Secondary Care)
-
Some high-cost drugs are funded directly by NHS England or hospital trusts rather than standard NHS prescription budgets.
-
These include biologics that must be administered in hospital settings (e.g., Reslizumab).
Summary
-
NICE/SMC decides which drugs get NHS funding.
-
Some biologics require specialist clinics.
-
Prescriptions are free in Scotland/Wales/NI but cost £9.65 per item in England.
-
Private prescriptions & insurance are alternatives for non-NHS-funded treatments.
-
Clinical trials or EAMS may offer early access to new drugs.

Getting the Most from Your Aspergillosis Clinic Appointments and Calls

Living with aspergillosis often means regular appointments with respiratory specialists, GPs, nurses, pharmacists and sometimes other healthcare professionals. These may take place in person, by telephone or through a video consultation.
Appointments can be surprisingly difficult. You may have waited months to speak to someone, only to find that the consultation is over before you have explained what is really troubling you.
Some patients describe leaving appointments feeling that their blood tests and scans have been discussed, but the effect of their illness on everyday life has received much less attention.
Preparing a little beforehand can help. But a successful appointment is not simply about having a list of questions. It is about making sure that you and your clinical team understand one another, agree what matters most and know what should happen next.
1. Decide what matters most before your appointment
Before your appointment, consider three questions:
- What has changed since my last appointment? Think about symptoms, energy levels, medication, infections and your ability to manage everyday activities.
- What worries me most? This might be a new symptom, a treatment side effect, uncertainty about your prognosis or fear of your condition getting worse.
- What do I most need help with? Perhaps you want better symptom control, help with fatigue, an explanation of a test result or a clearer treatment plan.
Write down your two or three highest priorities and mention them near the beginning of the consultation.
For example, you might say: "I know we need to discuss my scan, but the biggest problem for me at the moment is that I am too exhausted to manage ordinary activities."
This helps your clinician understand what matters to you, rather than relying entirely on medical measurements.
2. Explain how your illness affects everyday life
Clinical teams routinely assess symptoms, lung function, blood tests and imaging. These are important, but they do not always capture the full impact of aspergillosis.
For example, saying "I am very tired" provides less information than explaining:
- "I need to rest after taking a shower."
- "I can no longer walk to the local shop without stopping."
- "I have stopped seeing friends because I am too exhausted."
- "I am sleeping badly because of coughing."
- "I cannot concentrate well enough to manage my usual work."
These examples help clinicians understand the severity and practical consequences of your symptoms.
It can also help to describe what you could do six months ago compared with what you can manage now.
Remember: Quality of life is an important part of treatment. You do not have to wait until a symptom becomes medically dangerous before explaining how much it affects you.
3. Keep a simple record of symptoms and changes
Some people find it helpful to keep a health diary, particularly when symptoms fluctuate.
You might record:
- Changes in breathlessness, coughing, sputum or fatigue.
- New symptoms or possible treatment side effects.
- Infections, antibiotic courses or hospital admissions.
- Changes in activity, sleep or appetite.
- Medication changes and how you responded.
- Questions that arise between appointments.
You do not need a complicated system. A notebook, calendar or note on your phone may be sufficient.
Try to identify patterns rather than presenting every daily observation. For example: "My breathlessness has gradually worsened over the last six weeks" is often more helpful than a long list of individual readings.
If you use a home oxygen monitor or peak-flow meter, ask your clinical team which measurements are useful to record and what changes should prompt you to seek advice.
4. Bring an accurate medication list
People with aspergillosis may take antifungal medicines, inhalers, corticosteroids, antibiotics and treatments for other conditions.
Bring an up-to-date list showing the name, dose and frequency of each medicine, including supplements and medicines bought without a prescription.
Tell your clinician about:
- Medicines you have stopped or changed.
- Side effects or difficulties taking treatment.
- Missed doses or problems obtaining prescriptions.
- Any new medicines prescribed by another healthcare professional.
- Allergies or previous serious medication reactions.
This is particularly important for patients taking azole antifungals, which can interact with many other medicines.
For practical advice, read Managing Your Aspergillosis Medicines: Practical Tips for Staying Safe.
5. Make the most of telephone and video appointments
Remote consultations can save travel and reduce the physical effort involved in attending hospital. However, they also have limitations.
Before a telephone or video appointment:
- Find a quiet place where you can speak privately.
- Keep your medication list and questions nearby.
- Have a pen and paper ready to record decisions.
- Check your phone signal or internet connection.
- Arrange for a family member or carer to join if you would find this helpful.
Because your clinician cannot always examine you or observe your breathing in the usual way, describe physical changes clearly.
For example, explain whether you are breathless at rest or during activity, whether symptoms have changed recently and how they affect your usual activities.
If you feel that a physical examination is necessary, ask whether an in-person assessment can be arranged.
Do not wait for a routine remote appointment if you develop severe or rapidly worsening symptoms. Seek urgent medical advice through the appropriate NHS service.
6. Ask questions until you understand the answers
Medical consultations often involve unfamiliar terminology, particularly when discussing fungal infections, imaging, immune responses or antifungal treatment.
It is reasonable to ask for explanations in everyday language.
Useful questions include:
- What does this test result mean for me?
- Has my condition improved, worsened or remained stable?
- What are the benefits and risks of the treatment you recommend?
- What alternatives are available?
- What symptoms should prompt me to contact you?
- When will we review whether this treatment is working?
- What should I do if I cannot tolerate the medicine?
If something is unclear, you might say: "Could you explain that another way?" or "Can I check that I have understood correctly?"
Before the appointment ends, try summarising the agreed plan in your own words. This can reveal misunderstandings while there is still time to clarify them.
7. Talk openly about treatment difficulties
Some patients hesitate to mention problems with treatment because they worry about disappointing their clinical team or being seen as uncooperative.
However, treatment difficulties are important medical information.
Tell your team if:
- Side effects make you reluctant to take a medicine.
- You have reduced or missed doses because you feel unwell.
- You are worried about long-term corticosteroid treatment.
- Medication costs, supply problems or complicated schedules are causing difficulties.
- You feel that the treatment burden is becoming overwhelming.
There may be ways to make treatment more manageable, including changes to the regimen, additional monitoring or practical support.
The aim is to develop a treatment plan that is both medically appropriate and realistic for your everyday life.
8. Bring someone with you if it helps
A partner, relative, friend or carer may help you remember questions, take notes or explain changes they have noticed.
They may also provide support when discussing difficult subjects such as prognosis, treatment risks or major changes in health.
You can ask whether someone may join a telephone or video consultation as well as an in-person appointment.
It is still important that your own concerns and preferences remain central to the discussion.
If communication is difficult because of hearing, language, cognitive or other accessibility needs, ask the clinic about appropriate adjustments or professional interpreting support.
9. Before the appointment ends, agree what happens next
One of the most important parts of a consultation is making sure you understand the next steps.
Before leaving, try to establish:
- Are any medicines being started, stopped or changed?
- Do I need blood tests, scans or other investigations?
- Who will arrange those tests?
- Who will review the results and tell me what they mean?
- When should I expect my next appointment?
- Who should I contact if my symptoms change before then?
- What should I do if an expected appointment or result does not arrive?
Ask whether the agreed plan can be provided in writing or included in your clinic letter.
Do not assume that a missing test result or appointment means everything is normal. If you have not received information when expected, contact the responsible team.
10. What if you feel you have not been heard?
Some patients leave consultations feeling that their concerns were not fully understood. This can happen even when the clinical team is working hard and providing appropriate medical care.
Appointments are often short, and patients and clinicians may naturally focus on different aspects of the illness.
If an important concern has not been addressed, it is reasonable to raise it again.
You might say:
- "I understand that my tests are stable, but my quality of life has become much worse."
- "I am struggling to manage at home and need help with that."
- "I do not think I explained how severely this is affecting me."
- "Could we agree a plan for what happens if these symptoms continue?"
If necessary, ask whether another appointment, a specialist nurse discussion or a review by an appropriate member of the multidisciplinary team would help.
Being heard does not always mean receiving the treatment you hoped for. It means your concerns have been understood, considered and discussed, and that you understand the reasons behind the agreed plan.
11. Know how to contact your team between appointments
Aspergillosis symptoms can change between scheduled reviews, and patients may need advice about medication, side effects, test results or worsening respiratory symptoms.
Ask your clinic which service you should contact for routine questions and which symptoms require more urgent assessment.
For patients attending the National Aspergillosis Centre (NAC), contact arrangements and access to clinical information may include NHS services and the myMFT patient portal, where available. Your team can explain which communication routes are appropriate for your care.
Online patient communities can provide valuable emotional and practical support, but they cannot replace clinical assessment or emergency medical advice.
For information about patient support, visit our Community Support section.
A simple checklist for your next appointment
You may find it useful to copy or print this checklist:
- ☐ My three most important concerns are written down.
- ☐ I can explain what has changed since my last appointment.
- ☐ I have examples of how symptoms affect everyday life.
- ☐ My medication list is up to date.
- ☐ I have recorded any important side effects or treatment difficulties.
- ☐ I know which test results or treatment decisions I want explained.
- ☐ I have asked what happens next and who is responsible.
- ☐ I know whom to contact if problems arise before my next appointment.
Key points
- Start with what matters most to you. Do not leave your biggest concern until the end.
- Describe the effect on everyday life. Practical examples often communicate more than general symptom descriptions.
- Keep records simple and useful. Focus on changes and patterns.
- Be open about treatment difficulties. Your team needs to know when medicines are causing problems.
- Ask for explanations you understand. It is reasonable to ask questions or request clarification.
- Agree a clear follow-up plan. Know who is arranging tests, reviewing results and providing further advice.
- Speak up if your concerns have not been addressed. Good care depends on communication in both directions.
Remember: You are an important member of your own healthcare team. Your experience of living with aspergillosis provides information that blood tests, scans and lung function measurements cannot always capture.
A good consultation combines clinical expertise with an understanding of what matters to you.
This article provides general information to help patients prepare for clinical appointments. It does not replace individual medical advice. If you develop severe or rapidly worsening symptoms, seek appropriate urgent medical care rather than waiting for a routine appointment.